Related Experiment Video
Updated: Aug 16, 2026


Rapid Point-of-Care Assay of Enoxaparin Anticoagulant Efficacy in Whole Blood
Published on: October 12, 2012
Pharmacokinetics and pharmacodynamics of ximelagatran
Michael Wolzt1, Troy S Sarich, Ulf G Eriksson
1Clinical Pharmacology, Allgemeines Krankenhaus Wien, Waehringer Guertel 18-20, Medical University of Vienna, Vienna, Austria.

Abstract:
Oral anticoagulant therapy with vitamin K antagonists (VKAs) such as warfarin has proven benefits in the treatment and prevention of thromboembolic disorders but has important limitations that result in substantial underuse. In particular, the VKAs have variable and unpredictable pharmacokinetics and pharmacodynamics and a narrow separation between antithrombotic and hemorrhagic effects that necessitates careful dose adjustment based on frequent coagulation monitoring. In contrast, the oral direct thrombin inhibitor ximelagatran has a predictable and reproducible pharmacokinetic/pharmacodynamic profile that allows treatment using fixed-dose regimens without coagulation monitoring. The bioavailability of melagatran, the active form of ximelagatran, after oral administration of ximelagatran is approximately 20% with low inter- and intra-individual variability. Peak plasma melagatran concentrations are reached approximately 2 hours after oral dosing of ximelagatran to healthy volunteers, and melagatran is eliminated with a half-life of approximately 3 hours with clearance predominantly by renal excretion. Hence, a higher melagatran exposure is seen in patients with renal failure; ximelagatran is currently not recommended for patients with severe renal impairment (creatinine clearance of <30 mL/min) as these patients were not included in the clinical trial program. Exposure to melagatran increases linearly with the ximelagatran dose. The pharmacokinetic/pharmacodynamic profile is consistent across a broad range of different patient populations and is unaffected by gender, age, body weight, ethnic origin, obesity, and mild-to-moderate hepatic impairment. Any differences in melagatran pharmacokinetics associated with these factors are attributable to differences in renal function.
Related Concept Videos
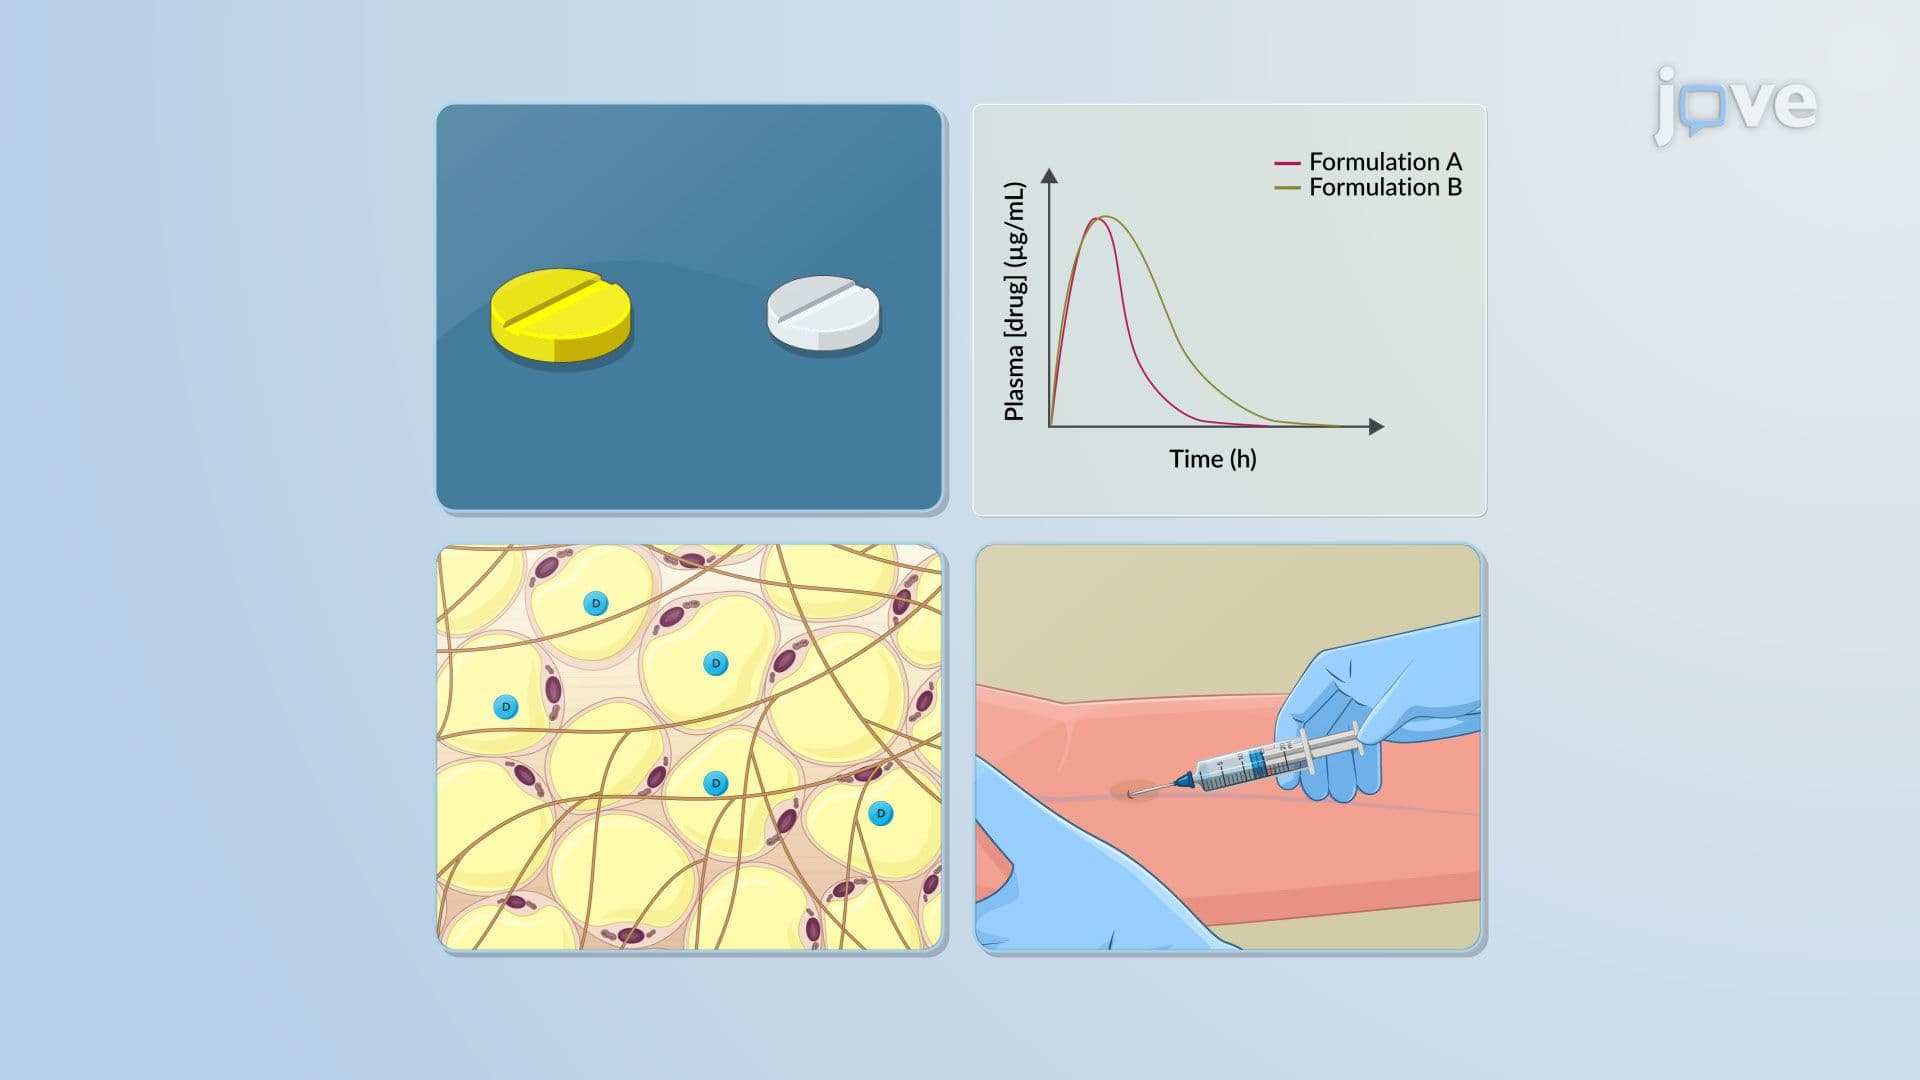 01:14
Pharmacokinetic–Pharmacodynamic Relationship: Duration of Dose-Effect Relationship
 01:29
Pharmacogenetic Phenotypes: Alterations in Pharmacokinetics, Drug Targets and Biologic Milieu
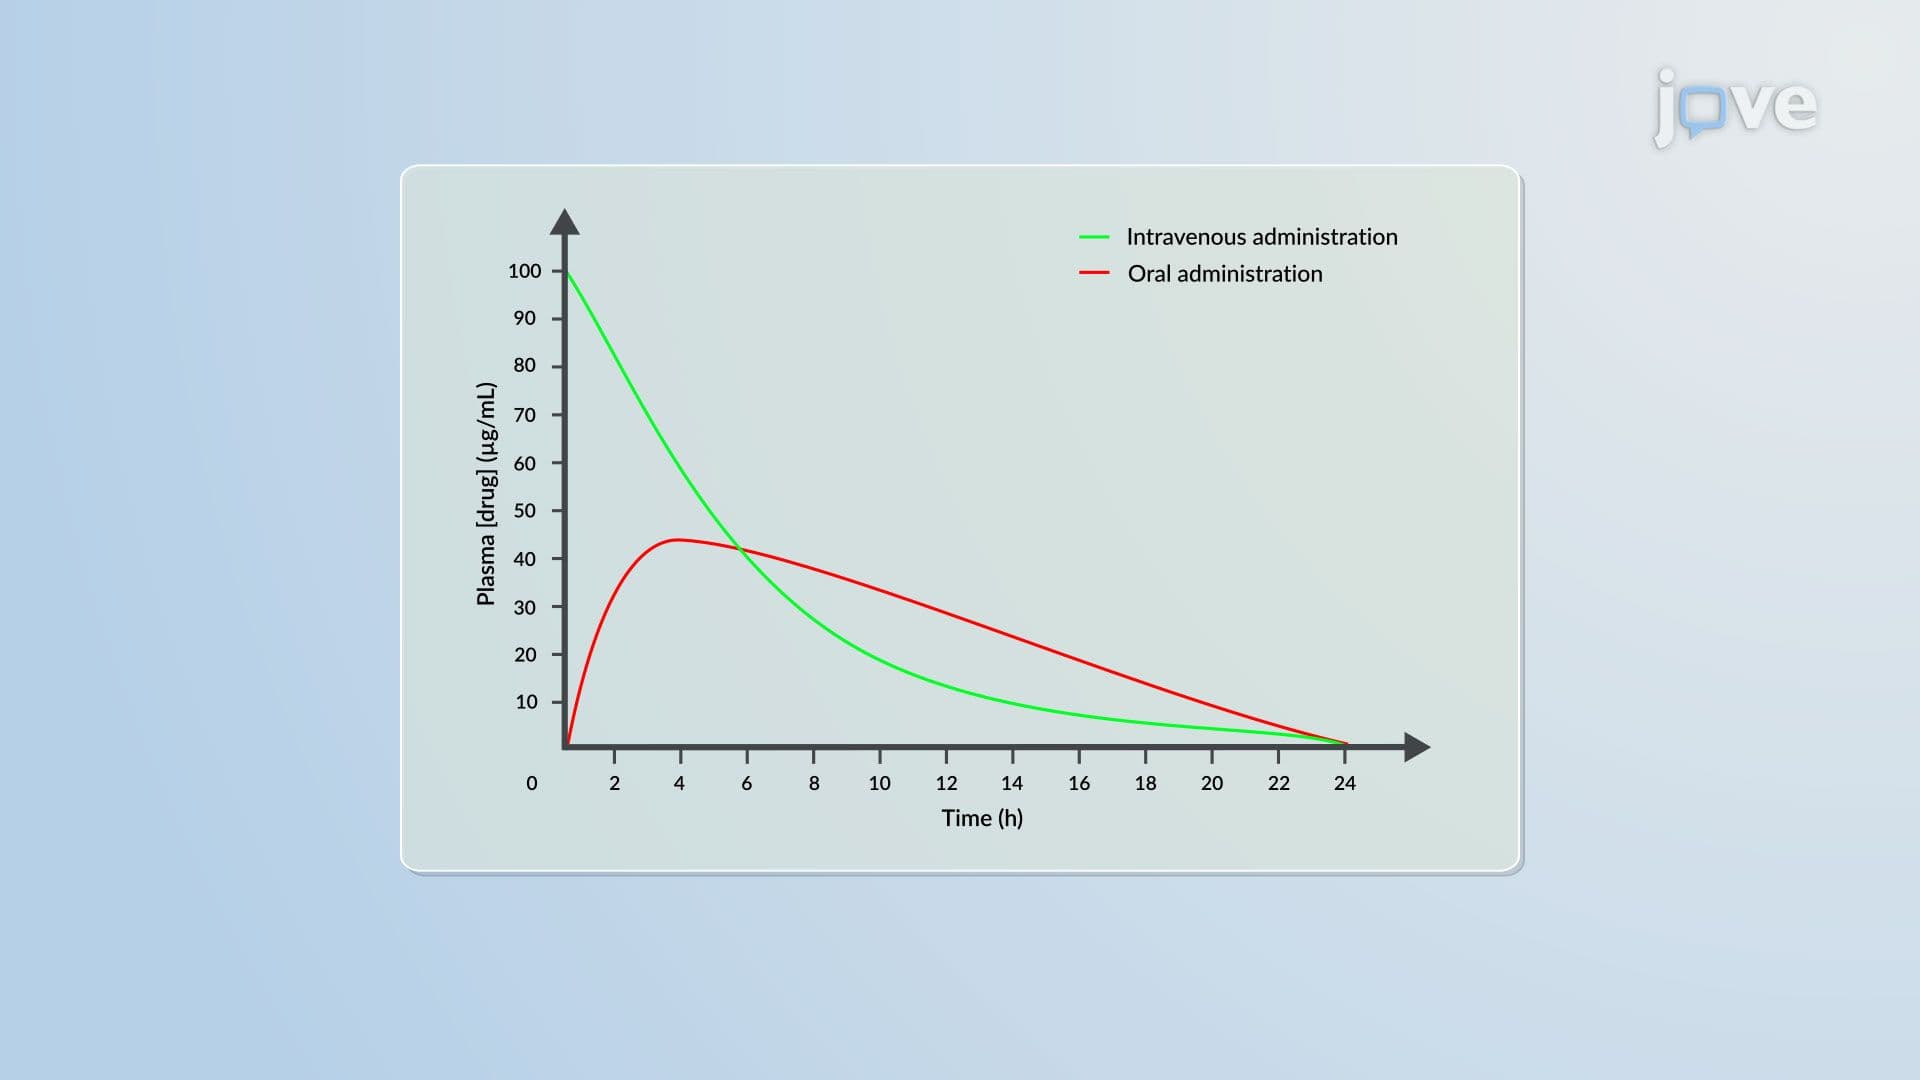 01:14
Pharmacokinetic–Pharmacodynamic Relationship: Model Components
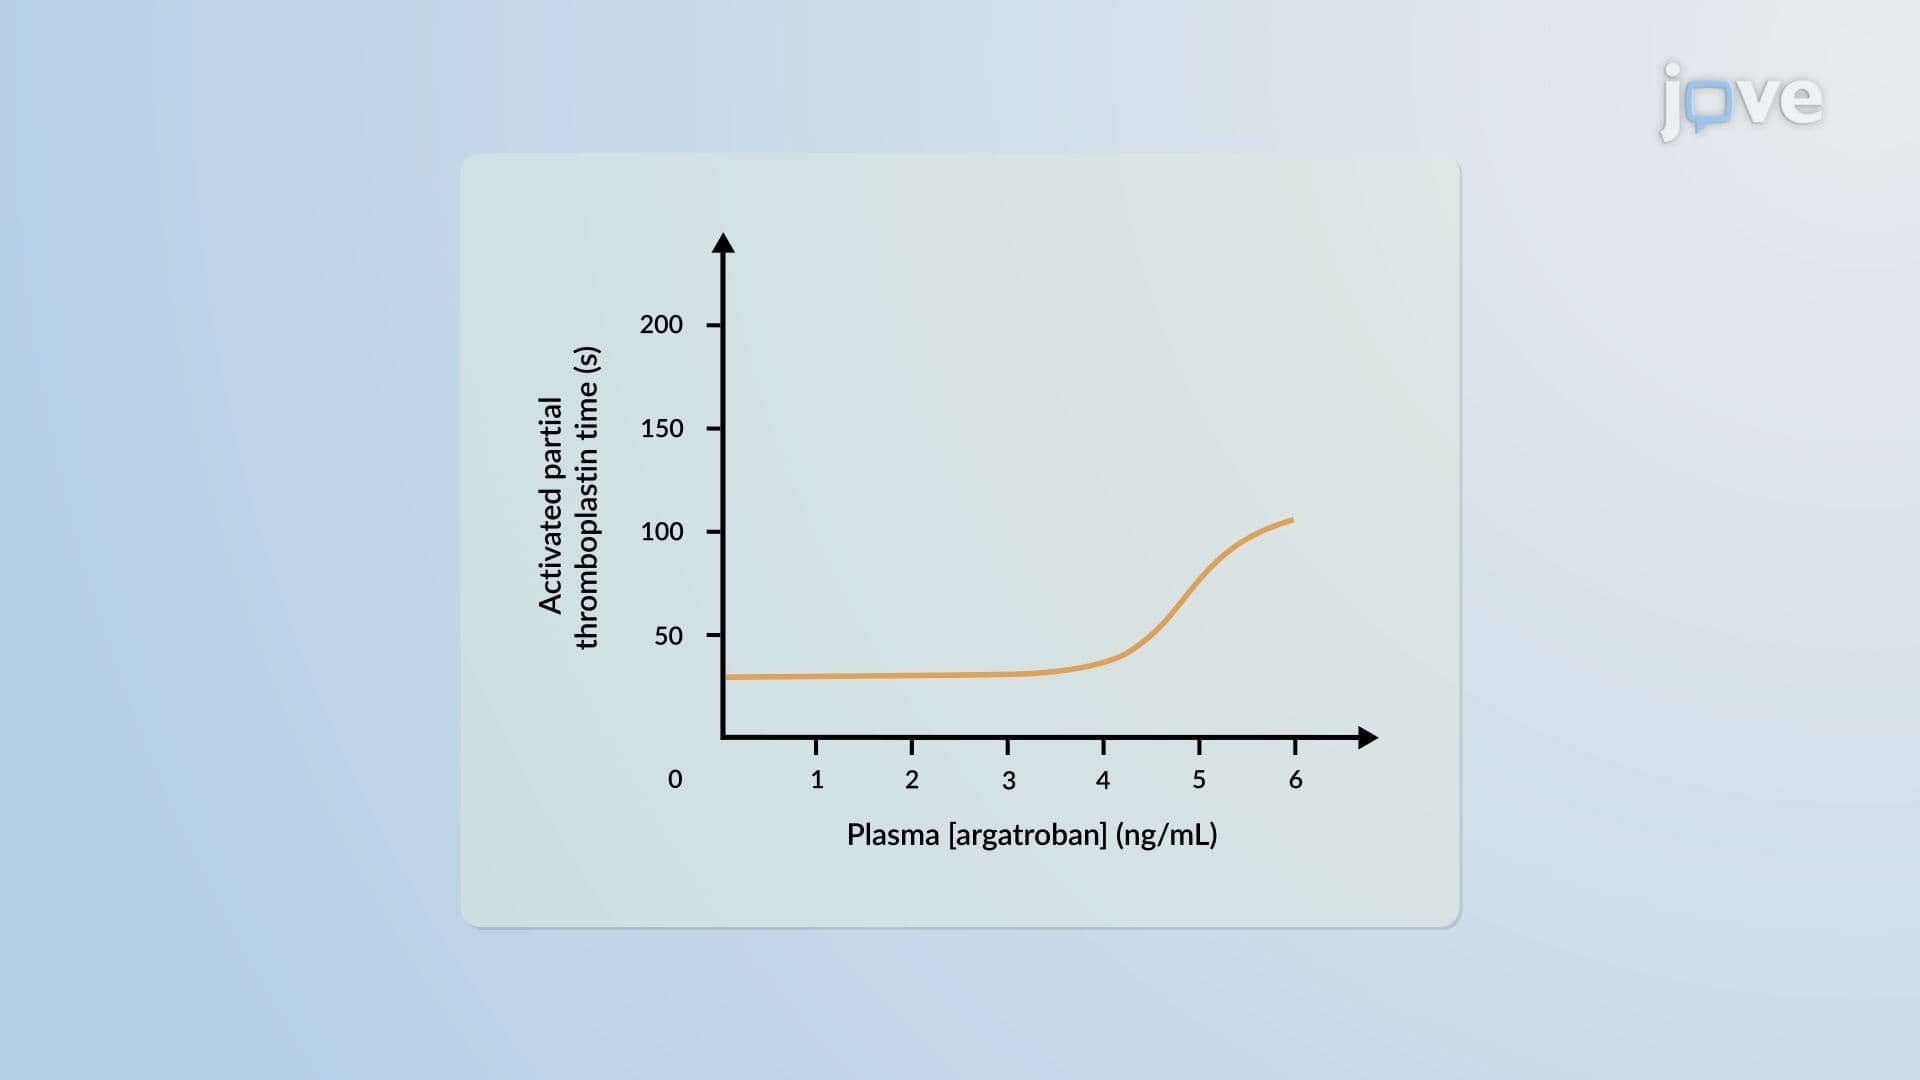 01:29
Pharmacodynamic Models: Direct Effect Model and Indirect Response Model
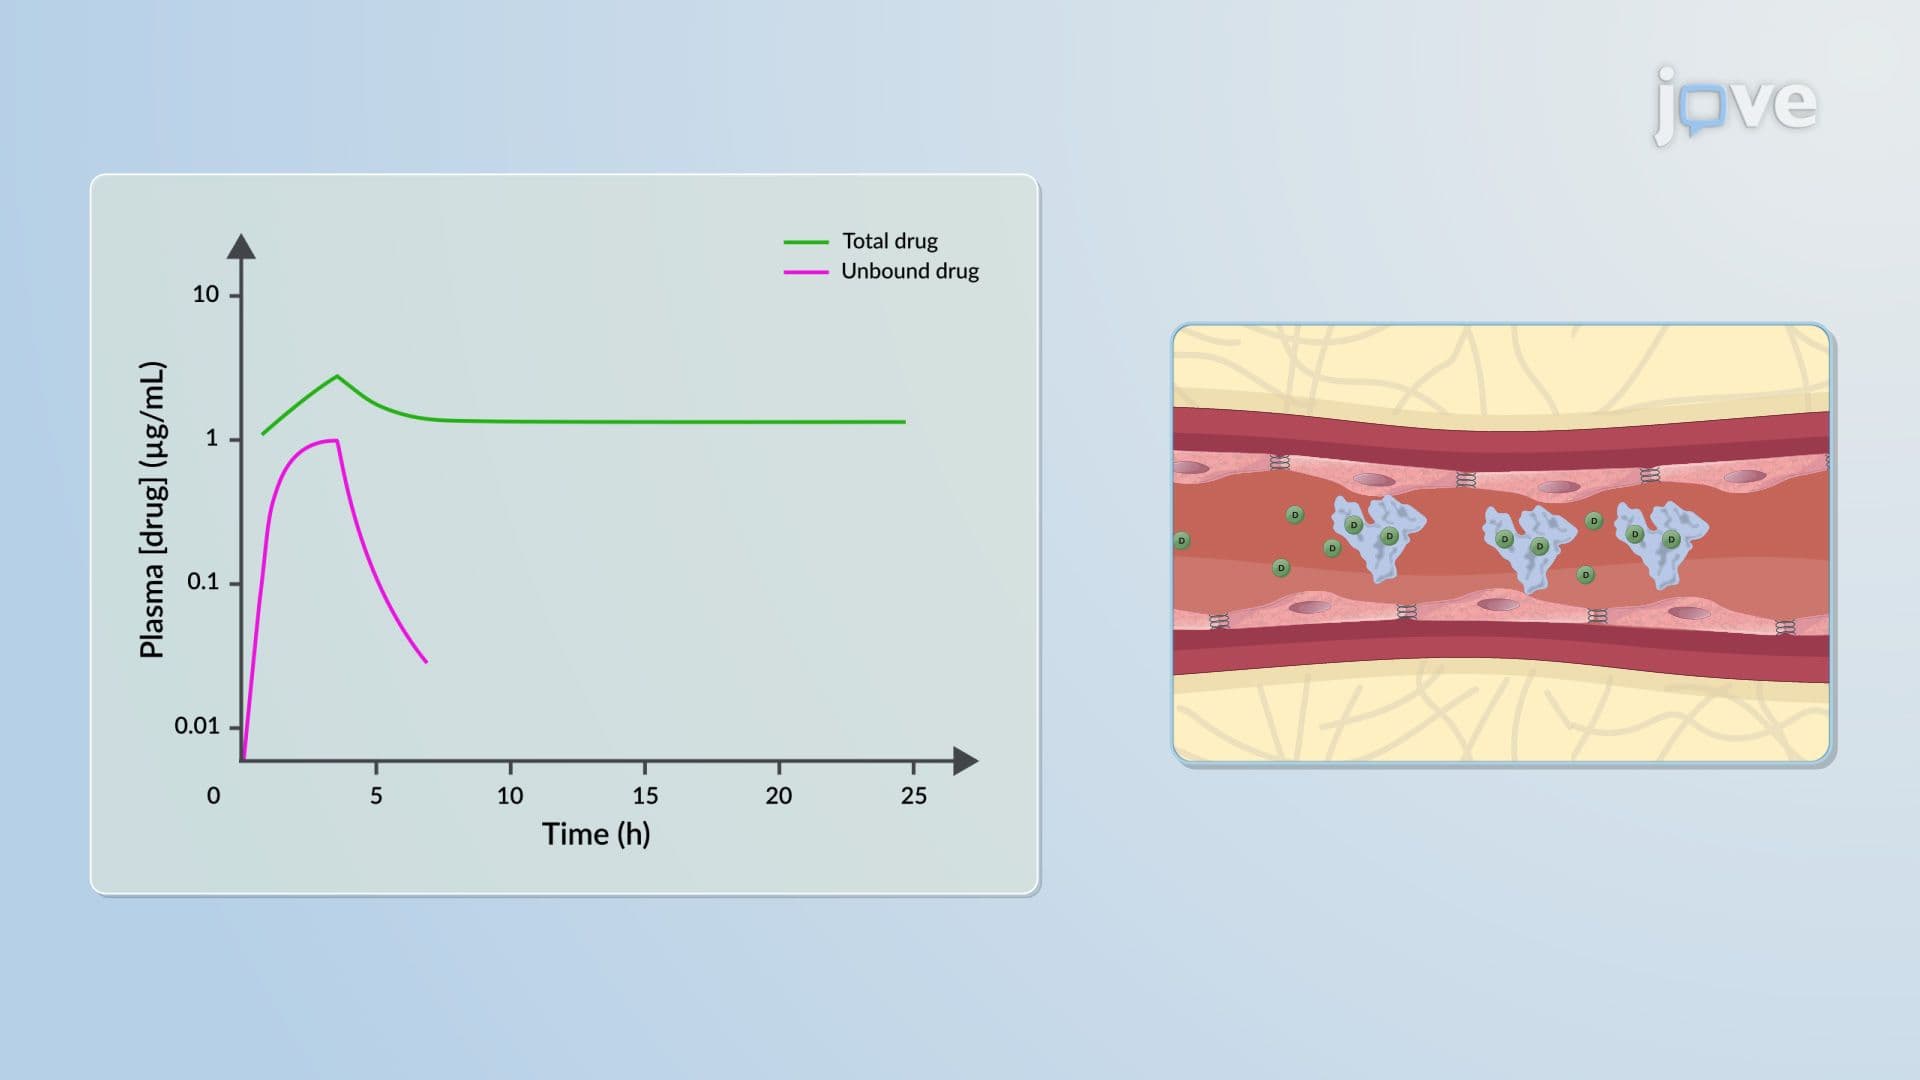 01:24
Pharmacokinetic–Pharmacodynamic Relationship: Problems
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions