Related Experiment Video
Updated: Aug 14, 2026


Accessing the Cytotoxicity and Cell Response to Biomaterials
Published on: July 8, 2021
Relationship of phosphorus and calcium-phosphorus product with mortality in CKD
Vandana Menon1, Tom Greene, Arema A Pereira
1Division of Nephrology, Department of Medicine, Tufts-New England Medical Center, Boston, MA, USA.

Insights
In chronic kidney disease (CKD) stages 3-4, serum phosphorus and calcium-phosphorus product were not linked to mortality after adjusting for GFR. Further research is needed to confirm these findings in current clinical practice.
Area of Science:
- Nephrology
- Cardiovascular Medicine
- Mineral Metabolism
Background:
- Mineral metabolism abnormalities are common in kidney failure, increasing cardiovascular event risk.
- Limited data exist on phosphorus and calcium-phosphorus product associations with outcomes in CKD stages 3-4.
Purpose of the Study:
- To investigate the relationship between serum phosphorus and calcium-phosphorus product with mortality in CKD patients.
- To assess associations with all-cause and cardiovascular disease (CVD) mortality.
Main Methods:
- Serum phosphorus and calcium measured in 840 participants from the Modification of Diet in Renal Disease Study.
- Survival data analyzed using Cox models to assess mortality risk.
- Adjustments made for GFR and other confounders.
Main Results:
- Serum phosphorus was not associated with all-cause mortality.
- An unadjusted association between serum phosphorus and CVD mortality was attenuated after adjustment.
- Calcium-phosphorus product showed no association with all-cause mortality and an attenuated, non-significant association with CVD mortality after adjustment.
Conclusions:
- Serum phosphorus and calcium-phosphorus product were not statistically linked to all-cause or CVD mortality in CKD patients after GFR adjustment.
- Larger studies are needed to evaluate these relationships, considering current clinical practice.
Background:
Abnormalities of mineral metabolism are prevalent in patients with kidney failure and are associated with increased risk for cardiovascular events. There are limited data investigating relationships of phosphorus and calcium-phosphorus product with outcomes in patients with chronic kidney disease (CKD) stages 3 to 4.
Methods:
Serum phosphorus and calcium were measured at baseline in 840 participants from the randomized cohort of the Modification of Diet in Renal Disease Study. Survival status until December 31, 2000, was obtained from the National Death Index. Cox models were performed to assess the relationship of serum phosphorus level and calcium-phosphorus product with all-cause and cardiovascular disease (CVD) mortality.
Results:
Mean serum phosphorus level was 3.8 +/- 0.7 mg/dL (1.23 +/- 0.23 mmol/L), calcium-phosphorus product was 34.7 +/- 6.3 mg2/dL2, and glomerular filtration rate (GFR) was 33 +/- 12 mL/min/1.73 m2 (0.55 +/- 0.20 mL/s/1.73 m2). All-cause and CVD mortality rates were 25% and 15%. Serum phosphorus level was not related to all-cause mortality in multivariable models (P = 0.46). In unadjusted analysis, serum phosphorus level was associated with (hazard ratio [HR] per 1 mg/dL increase, 1.34; 95% confidence interval [CI], 1.05 to 1.71; P = 0.02) increased risk for CVD mortality, but this association was partly attenuated and not statistically significant after adjustment for GFR and other confounders (HR, 1.27; 95% CI, 0.94 to 1.73; P = 0.12). Calcium-phosphorus product was not associated with all-cause mortality in unadjusted (P = 0.23) or multivariate analysis (P = 0.35). Calcium-phosphorus product was related to CVD mortality in unadjusted (HR per 10 mg2/dL2 increase, 1.30; 95% CI, 1.01 to 1.69; P = 0.04) analysis, but this association was not statistically significant after adjustment for GFR and other confounders (HR, 1.22; 95% CI, 0.89 to 1.66; P = 0.23).
Conclusion:
In the Modification of Diet in Renal Disease Study cohort, serum phosphorus level and calcium-phosphorus product were not statistically associated with all-cause or CVD mortality after adjustment for GFR; however larger studies with additional statistical power are needed to evaluate these relationships, especially in the context of current practice patterns in patients with CKD.


Related Concept Videos
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:21
Skeleton and Calcium Homeostasis
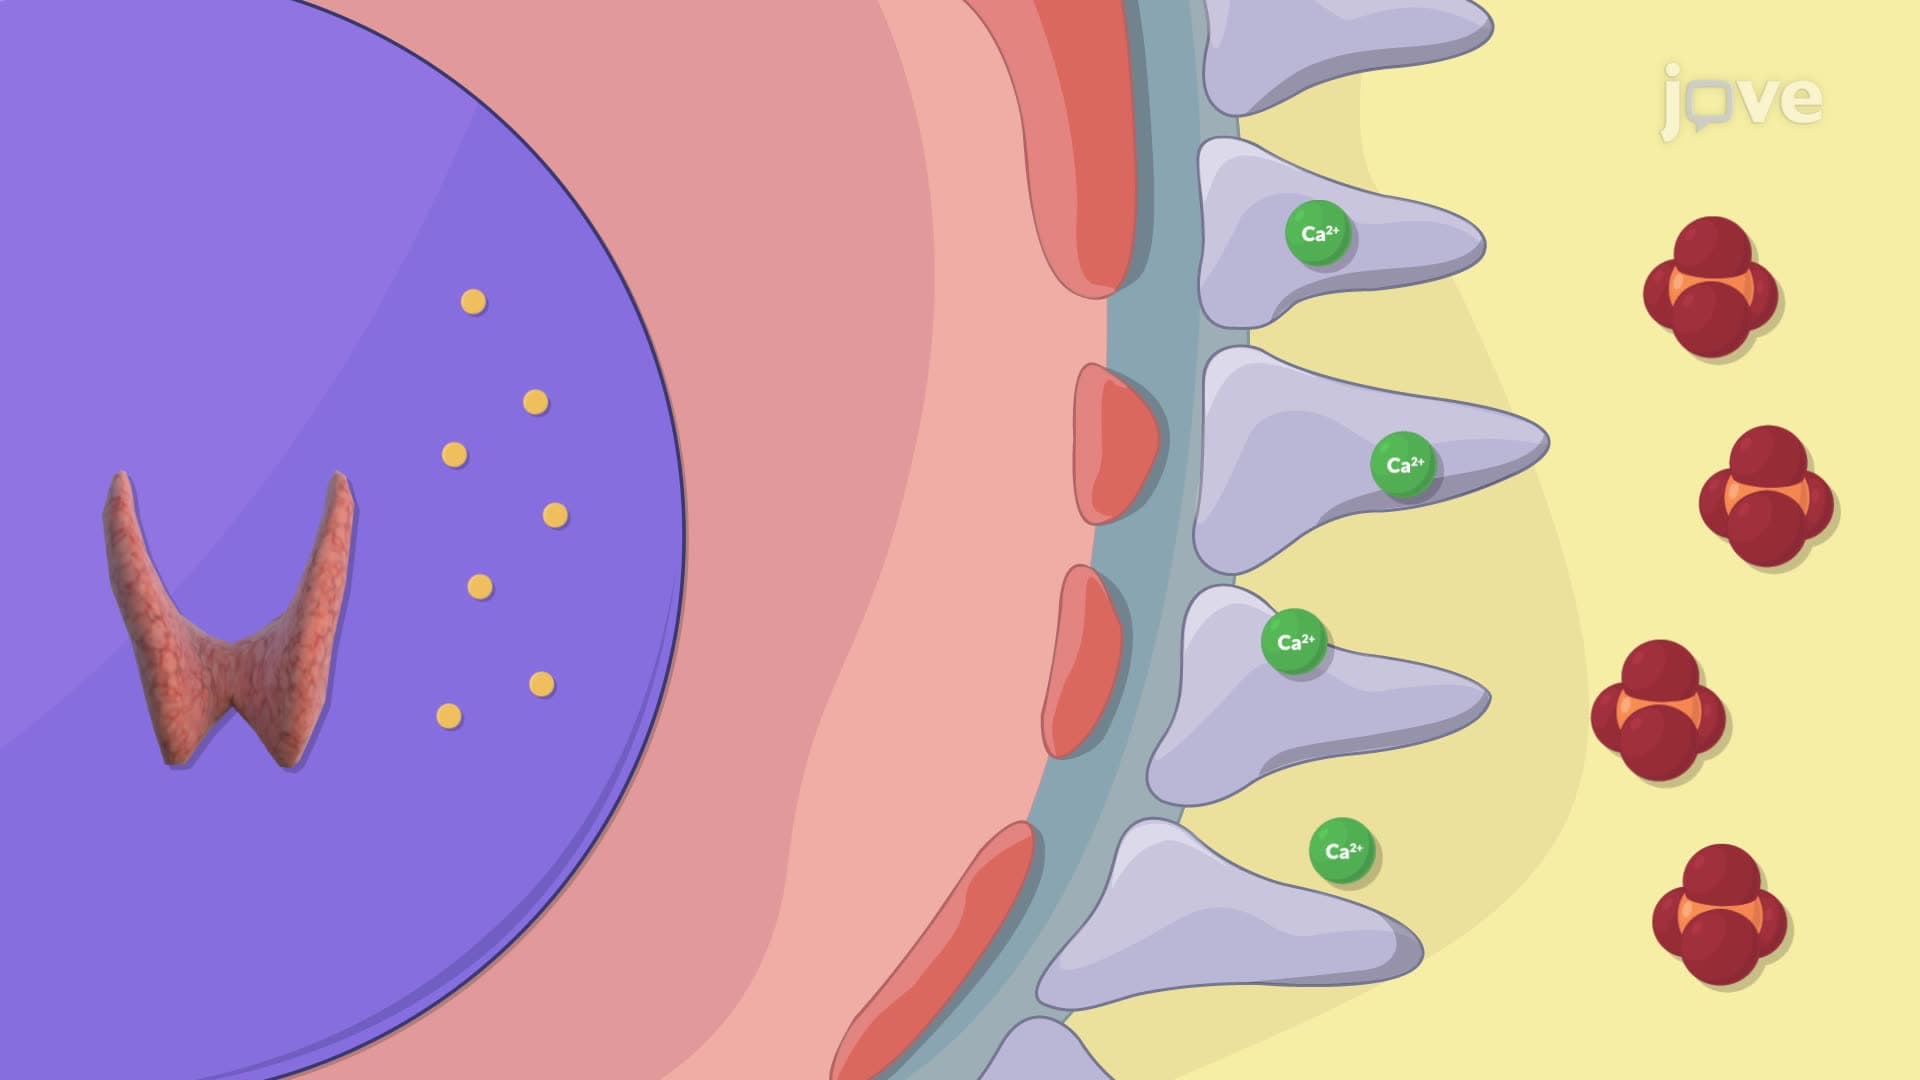 01:27
Roles of Electrolytes: Calcium and Phosphate
The calcium concentration in blood plasma is primarily regulated...
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:28
Chronic Kidney Disease III: Interprofessional Care