Related Experiment Video
Updated: Aug 15, 2026
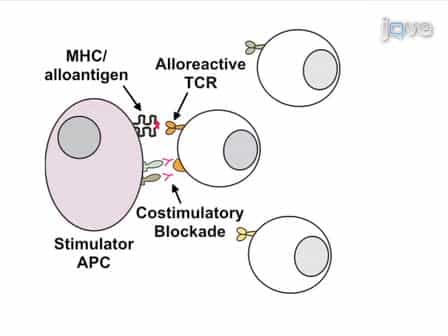

Induction of Alloantigen-specific Anergy in Human Peripheral Blood Mononuclear Cells by Alloantigen Stimulation with Co-stimulatory Signal Blockade
Published on: March 14, 2011
The role of immune ablation and stem cell transplantation in severe SLE
Steven Z Pavletic1, Gabor G Illei
1Graft-Versus-Host and Autoimmunity Unit, Experimental Transplantation and Autoimmunity Branch, National Cancer Institute, Bethesda, MD, USA.

High-dose immunosuppression followed by autologous hematopoietic stem cell therapy (HSCT) has the promise of long-term response after a short, intense period of immunosuppressive therapy but it is associated with an increased risk of serious short-term complications. HSCT induces major clinical responses in about 65% of patients with SLE who failed standard therapies. In some of these patients such responses are durable for at least several years, but the curative potential of this procedure in severe SLE is still unknown. Procedure-related mortality varies among studies between 5 and 12% and seems to be lower in relatively larger single center studies. Until more reliable estimates of the actual risks and long-term outcomes become available, patients with potentially life-threatening or disabling major organ involvement who are in acceptable general medical condition should be considered for autologous HSCT if they have failed a reasonable course of standard immunosuppressive therapy. To accomplish the best therapeutic and scientific results, it is necessary to treat all patients in carefully planned protocols by specialized teams of lupus specialists and transplanters. All immunoablative protocols should incorporate carefully planned studies of immune reconstitution to understand the mechanisms of cure or failure.
High-dose immunosuppression followed by autologous hematopoietic stem cell therapy (HSCT) has the promise of long-term response after a short, intense period of immunosuppressive therapy but it is associated with an increased risk of serious short-term complications. HSCT induces major clinical responses in about 65% of patients with SLE who failed standard therapies. In some of these patients such responses are durable for at least several years, but the curative potential of this procedure in severe SLE is still unknown. Procedure-related mortality varies among studies between 5 and 12% and seems to be lower in relatively larger single center studies. Until more reliable estimates of the actual risks and long-term outcomes become available, patients with potentially life-threatening or disabling major organ involvement who are in acceptable general medical condition should be considered for autologous HSCT if they have failed a reasonable course of standard immunosuppressive therapy. To accomplish the best therapeutic and scientific results, it is necessary to treat all patients in carefully planned protocols by specialized teams of lupus specialists and transplanters. All immunoablative protocols should incorporate carefully planned studies of immune reconstitution to understand the mechanisms of cure or failure.


Related Concept Videos
 01:40
Cell-mediated Immune Responses
 01:21
Stem Cell Therapy for Tissue Regeneration
Types of Stem Cells used in Stem Cell Therapy
The two main cell types that...
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy the...