Related Experiment Video
Updated: Aug 15, 2026

Measurements of Motor Function and Other Clinical Outcome Parameters in Ambulant Children with Duchenne Muscular Dystrophy
Published on: January 12, 2019
Prognostic value of the Duke Treadmill Score in diabetic patients
Dhanunjaya R Lakkireddy1, Jyothi Bhakkad, Hema L Korlakunta
1Creighton University Cardiac Center, Omaha, Nebraska 68131, USA.

Insights
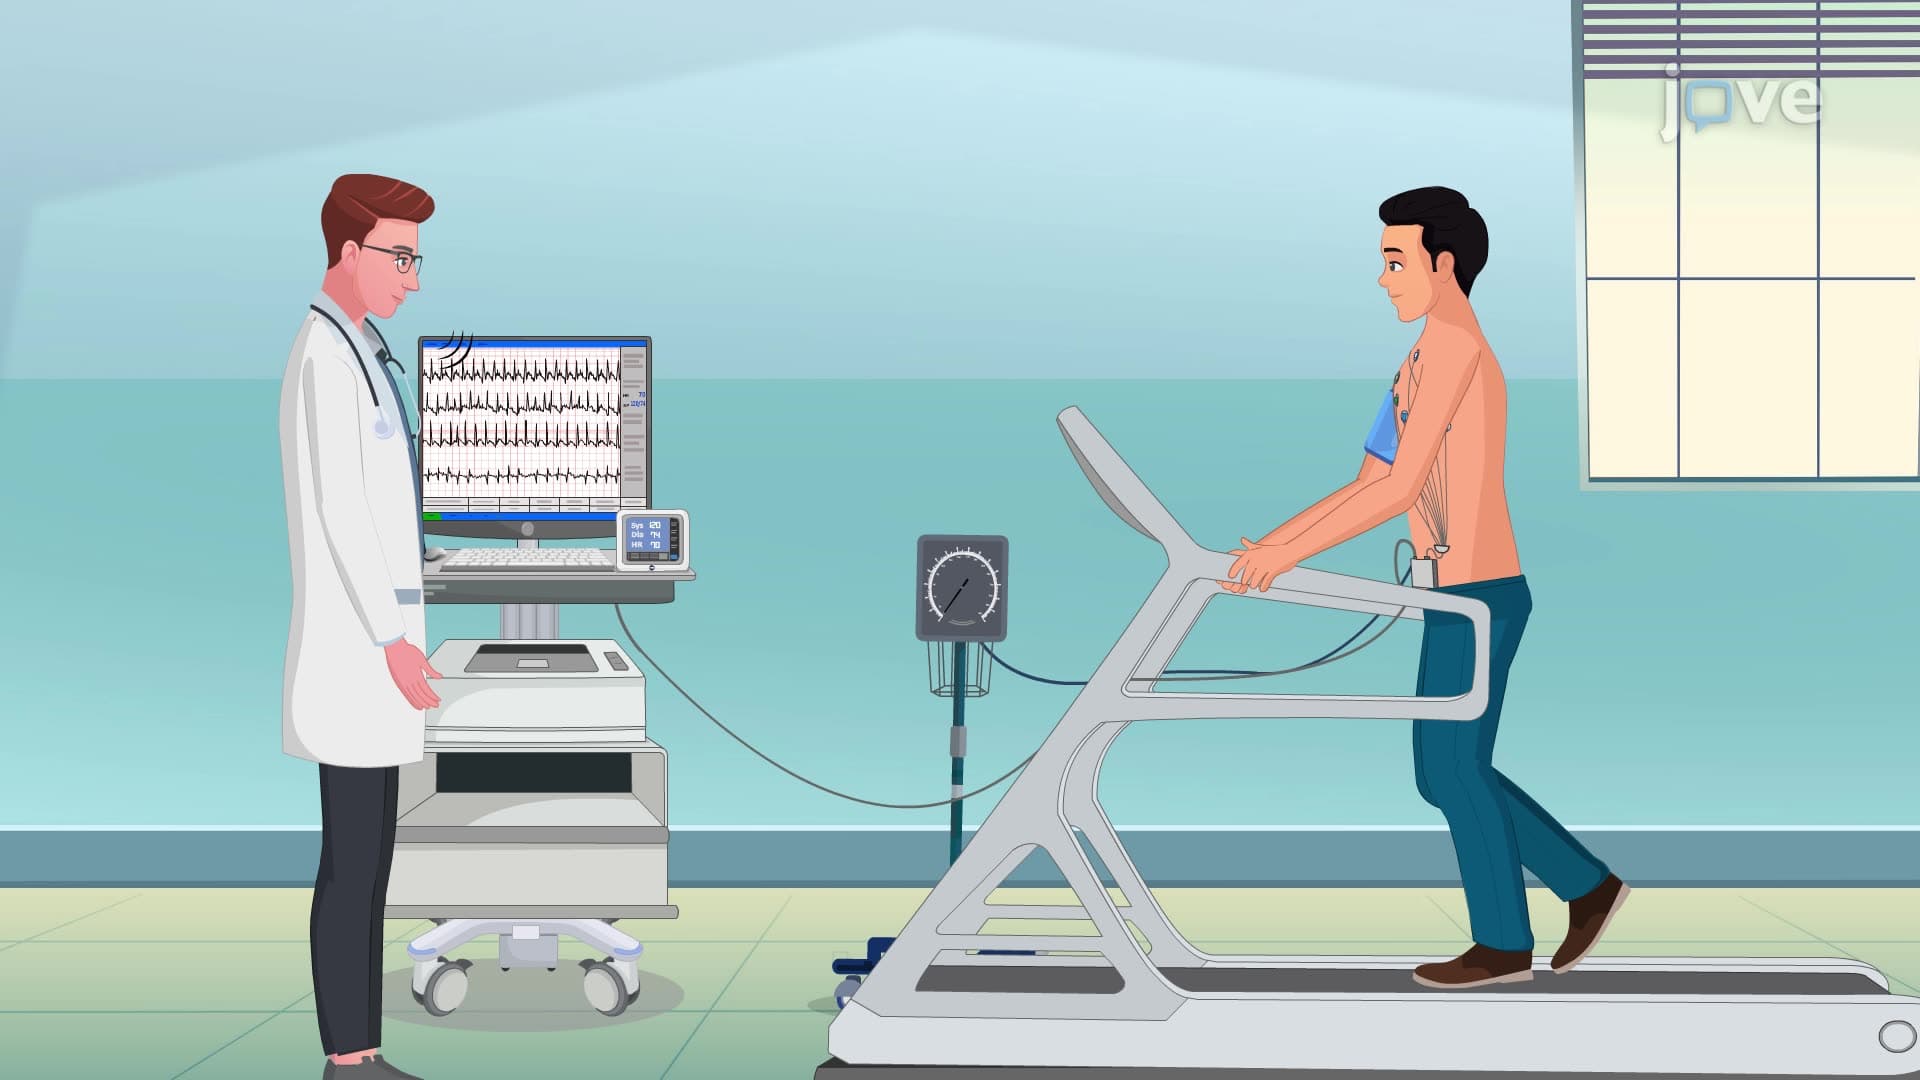
The Duke Treadmill Score (DTS) effectively predicts cardiac events in both diabetic and nondiabetic patients. This tool offers similar prognostic value for coronary artery disease risk stratification across both groups.
Area of Science:
- Cardiology
- Diabetology
- Risk Stratification
Background:
- The Duke Treadmill Score (DTS) is a validated tool for assessing coronary artery disease (CAD) risk.
- Its prognostic utility in diabetic populations compared to nondiabetics requires further investigation.
Purpose of the Study:
- To evaluate and compare the prognostic value of the Duke Treadmill Score (DTS) in patients with diabetes mellitus versus age- and sex-matched nondiabetic controls.
- To determine if DTS risk stratification for coronary artery disease differs between these groups.
Main Methods:
- A cohort study involving 100 diabetic patients and 202 matched nondiabetic controls without known CAD.
- Risk stratification using DTS, followed by a median 6.6-year follow-up for primary and secondary cardiac events, composite outcomes, and coronary angiography rates.
Main Results:
- The DTS demonstrated significant prognostic value for composite events in both diabetic (P < .001) and nondiabetic (P < .001) groups.
- Diabetic patients experienced higher rates of secondary events (P = .011) and coronary angiography (P < .001).
- Survival free from major adverse cardiac events differed significantly across DTS risk groups for diabetics (P = .002) but not controls (P = .07).
Conclusions:
- The Duke Treadmill Score (DTS) is an equally effective predictor of survival free from major adverse cardiac events and composite events in both diabetic and nondiabetic individuals.
- DTS provides consistent prognostic information for CAD risk stratification across diverse patient populations.
Background:
The Duke Treadmill Score (DTS) is an established clinical tool for risk stratification of coronary artery disease. We sought to assess the prognostic value of the DTS in diabetics compared with nondiabetics in this study.
Methods:
We studied 100 diabetics and 202 age- and sex-matched nondiabetic controls without known coronary artery disease risk stratified by DTS and followed for a median duration of 6.6 years. The association between DTS and primary, secondary outcomes, composite events, and rate of coronary angiography was tested.
Results:
Survival free from cardiac death, nonfatal myocardial infarction, congestive heart failure, or early and late revascularization was 89%, 54%, and 13%, respectively, in the low-, intermediate-, and high-risk categories of diabetic group (P < .0001), and 91%, 57%, and 17%, respectively, in the low- to high-risk groups of nondiabetics (P < .0001). During follow-up, diabetics had more secondary events (P = .011) and coronary angiography (P < .001) compared with nondiabetics. The DTS was a strong independent predictor of composite events in both diabetics (P < .001) and nondiabetics (P < .001). A significant number of diabetics were classified as intermediate risk and had a significantly higher incidence of coronary angiography (87.5% vs 70.8%, P = .032) and late revascularizations (35.4% vs 15.3%, P = .011) within this risk group compared with nondiabetics. Survival free from major adverse cardiac events differed significantly across the 3 Duke risk groups for diabetics (P = .002) but not for controls (P = .07). Survival free from composite events differed significantly across the 3 Duke risk groups for both diabetics and nondiabetics (P < .0001). Overall, diabetics had higher rates of major adverse cardiac events, composite events (P = .011), and coronary angiography (P < .001) than nondiabetics. The DTS is a strong predictor of survival free of composite events in both groups by multivariate analysis.
Conclusions:
The DTS predicted survival free from MACE and composite events equally well in patients with and without diabetes.