Related Experiment Video
Updated: Aug 15, 2026


Development of a Polymicrobial Colony Biofilm Model to Test Antimicrobials in Cystic Fibrosis
Published on: September 20, 2024
Evaluating ciprofloxacin dosing for Pseudomonas aeruginosa infection by using clinical outcome-based Monte Carlo
Sheryl Zelenitsky1, Robert Ariano, Godfrey Harding
1Faculty of Pharmacy, University of Manitoba, Winnipeg, Canada. zelenits@ms.umanitoba.ca

Abstract:
Pseudomonas aeruginosa causes serious infections whose outcome is highly dependent on antimicrobial therapy. The goal of this study was to predict the relative efficacies of three ciprofloxacin dosing regimens for P. aeruginosa infection using clinical outcome-based Monte Carlo simulations (MCS) with "real patient" demographics, pharmacokinetics, MICs, and pharmacodynamics (PDs). Each cohort consisted of 1,000 simulated study subjects. Three ciprofloxacin dosing regimens were studied, including (i) the recommended standard dose of 400 mg given intravenously (i.v.) every 12 h (q12h), (ii) the recommended high dose of 400 mg i.v. q8h, and (iii) a novel, PD-targeted regimen to attain a fAUC/MIC value of >86. Probability of target attainment (PTA) and probability of cure (POC) were determined for each regimen. POC with the standard dose was at least 0.90 if pathogen MICs were < or =0.25 microg/ml but only 0.59 or 0.27 if MICs were 0.5 or 1 microg/ml, respectively. Predicted cure rates in these MIC categories were significantly higher at 0.72 and 0.40 with the high dose and 0.91 and 0.72 with the PD-targeted regimen(P < 0.0001). Analyses based on the local susceptibility profile produced PTA and POC estimates of 0.44 and 0.74 with the standard ciprofloxacin dose, 0.58 and 0.81 with the high dose, and 0.84 and 0.93 with the PD-targeted regimen, respectively. In conclusion, as demonstrated by clinical outcome-based MCSs, the highest recommended ciprofloxacin dose of 400 mg i.v. q8h should be used in the treatment of P. aeruginosa infection to improve PD target attainment and clinical cure. However, even this appears ineffective if pathogen MICs are 1 mug/ml, warranting the consideration of a lower MIC breakpoint, < or =0.5 microg/ml.
More Related Videos


Related Concept Videos
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:27
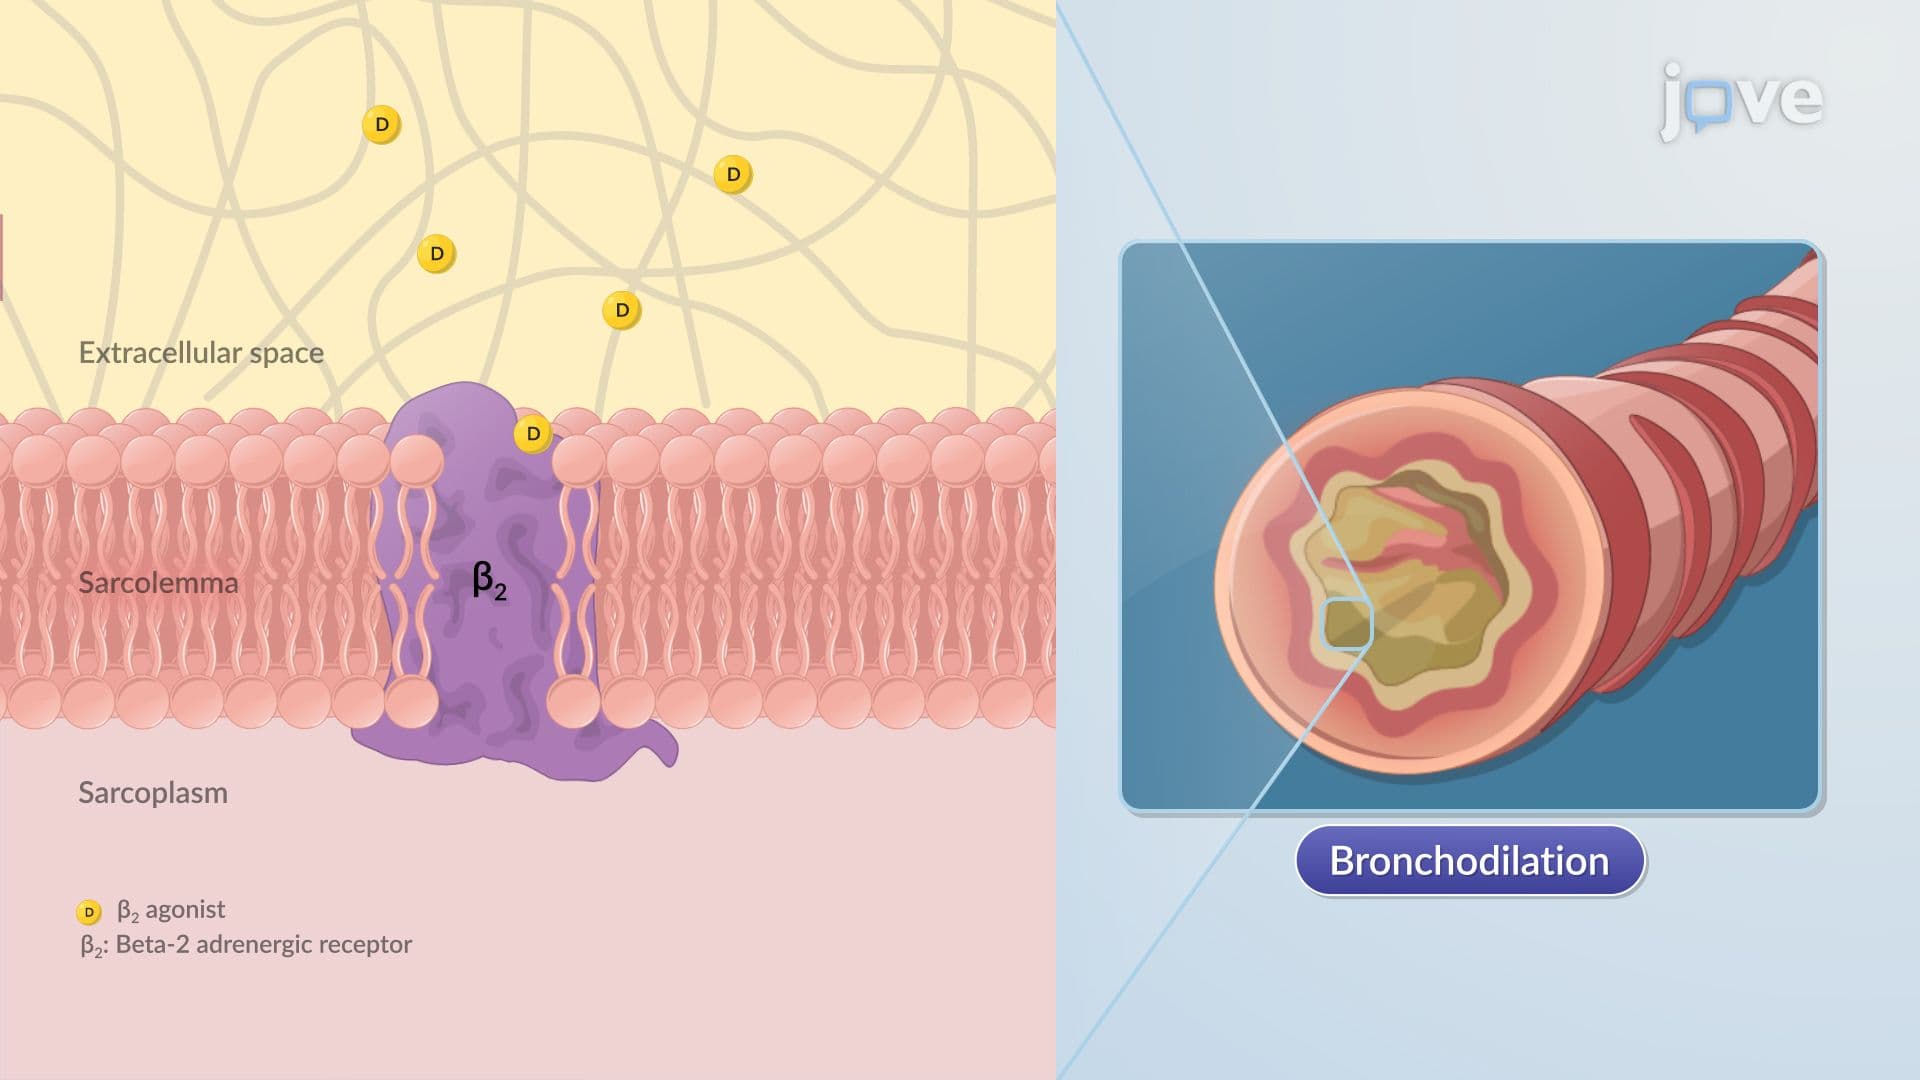
Pharmacodynamic Models: Overview