Related Experiment Video
Updated: Jul 6, 2026


Fixed Volume or Fixed Pressure: A Murine Model of Hemorrhagic Shock
Published on: June 6, 2011
Hemodynamic and pulmonary fluid status in the trauma patient: are we slipping?
William N Veale1, J H Morgan, J S Beatty
1Department of Surgery, Mercer University School of Medicine, Medical Center of Central Georgia, Macon, Georgia 31201, USA.

Abstract:
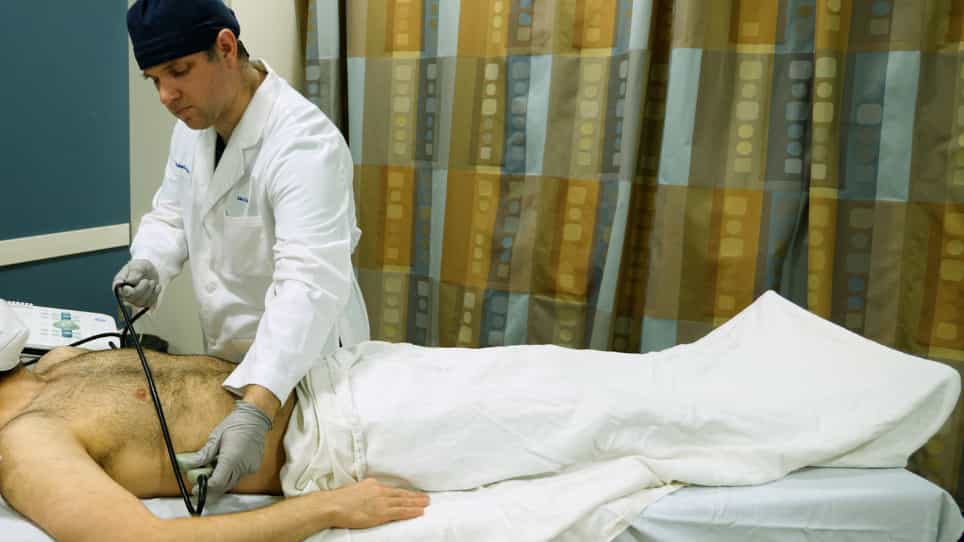
Recent reports point to problems in the clinical assessment of the cardiopulmonary system in hemodynamically unstable patients, especially with the decreasing usage of pulmonary artery catheters. Our purpose was to evaluate the hypothesis that clinical judgment alone is inadequate for a reliable estimate of cardiopulmonary status in critically ill patients. Physician assessments (high, normal, or low) of cardiac index (CI) and thoracic fluid content (TFC) were made in 68 acute trauma cases and compared to the results obtained with impedance cardiography (ICG). Physician assessment using clinical judgment alone was correct only 42 per cent and 57 per cent, respectively, for CI and TFC. There was very little difference in heart rate (HR), blood pressure (BP), Glasgow Coma Score (GCS), and the number of injured systems between the incorrect and correct assessments of CI. However, the mean Injury Severity Score (ISS) was markedly higher for the incorrect than the correct CI values (18.8 +/- 9.3 vs 14.2 +/- 9.8, P = 0.0589). Thus, there is a need for an objective measurement of CI and TFC especially in the more severely injured patient. The inaccuracy of the clinical exam strongly suggests the need for a supplemental measurement, which the new and improved ICG monitor could provide.

Related Concept Videos
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:23
Acute Respiratory Failure-IV
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:29
Pulmonary Embolism I: Introduction
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:18
Pulmonary Edema II: Pathophysiology