Interventions for primary (intrinsic) tracheomalacia in children
Related Experiment Video
Updated: Jul 26, 2026
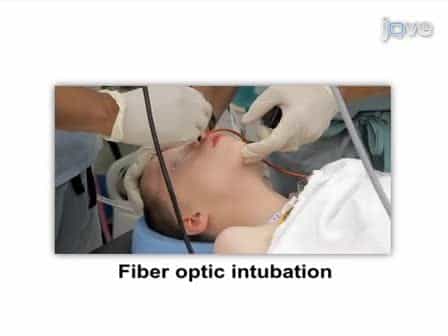
Guidelines for Elective Pediatric Fiberoptic Intubation
Published on: January 18, 2011
1Royal Children's Hospital, Respiratory Medicine, Herston Rd, Herston, Brisbane, Queensland, Australia 4029. brent_masters@health.qld.gov.au

Insights
This review found no randomized controlled trials for intrinsic tracheomalacia treatments. While some non-randomized studies suggest surgical benefits, evidence is limited, highlighting the need for rigorous trials in pediatric airway disorders.
Area of Science:
- Pediatric Pulmonology
- Respiratory Medicine
- Clinical Trials
Background:
- Tracheomalacia, a common pediatric airway disorder, presents with diverse respiratory symptoms.
- Current management includes medical, ventilatory (CPAP, BiPAP), and surgical interventions (stenting, aortopexy, tracheopexy).
Purpose of the Study:
- To evaluate the efficacy of medical and surgical therapies for intrinsic (primary) tracheomalacia in children.
Main Methods:
- Comprehensive search of multiple databases (CENTRAL, Cochrane Airways Group Register, MEDLINE, EMBASE) up to February 2005.
- Inclusion criteria focused on randomized controlled trials (RCTs) for therapies in primary tracheomalacia.
- No eligible RCTs were identified for data analysis.
Main Results:
- No RCTs were found evaluating therapies for intrinsic tracheomalacia.
- Eight non-randomized studies reported potential benefits from surgical interventions, but outcomes were not universally successful, and adverse events occurred.
Conclusions:
- A significant lack of evidence supports current therapies for intrinsic tracheomalacia.
- RCTs are crucial for less severe pediatric cases, necessitating inclusion of tracheal and physiological measures alongside clinical outcomes.
- Ethical considerations may limit RCTs for severe, life-threatening tracheomalacia cases.
Background:
Tracheomalacia, a disorder of the large airways where the trachea is deformed or malformed during respiration is commonly seen in tertiary paediatric practice. It is associated with a wide spectrum of respiratory symptoms from life threatening recurrent apnea to common respiratory symptoms such as chronic cough and wheeze. Current practice following diagnosis of tracheomalacia include medical approaches aimed at reducing associated symptoms of tracheomalacia, ventilation modalities of continuous positive airway pressure (CPAP) and bi-level positive airway pressure (BiPAP) and, surgical approaches aimed at improving the caliber of the airway (airway stenting, aortopexy, tracheopexy).
Objectives:
To evaluate the efficacy of medical and surgical therapies for children with intrinsic (primary) tracheomalacia.
Search Strategy:
The Cochrane Central Register of Controlled Trials (CENTRAL), the Cochrane Airways Group Specialised Register, MEDLINE and EMBASE databases were searched by the Cochrane Airways Group. The latest searches were performed in Feb 2005.
Selection Criteria:
All randomised controlled trials of therapies related to symptoms associated with primary or intrinsic tracheomalacia.
Data Collection And Analysis:
Results of searches were reviewed against pre-determined criteria for inclusion. No eligible trials were identified and thus no data were available for analysis.
Main Results:
No randomised controlled trials (RCTs) that examined therapies for intrinsic tracheomalacia were found. Eight of the more recent (last 11 years) non randomised controlled trials reported a benefit from the various surgical interventions. The success was however not universal and in some studies severe adverse events occurred.
Authors' Conclusions:
There is currently an absence of evidence to support any of the therapies currently utilised for management of intrinsic tracheomalacia. It is unlikely that any RCT on surgically based management will ever be available for children with severe life threatening illness associated with tracheomalacia. For those with less severe disease, RCTs are clearly needed. Outcomes of these RCTs should include measurements of the trachea and physiological outcomes in addition to clinical outcomes.
More Related Videos

Related Concept Videos
 01:22
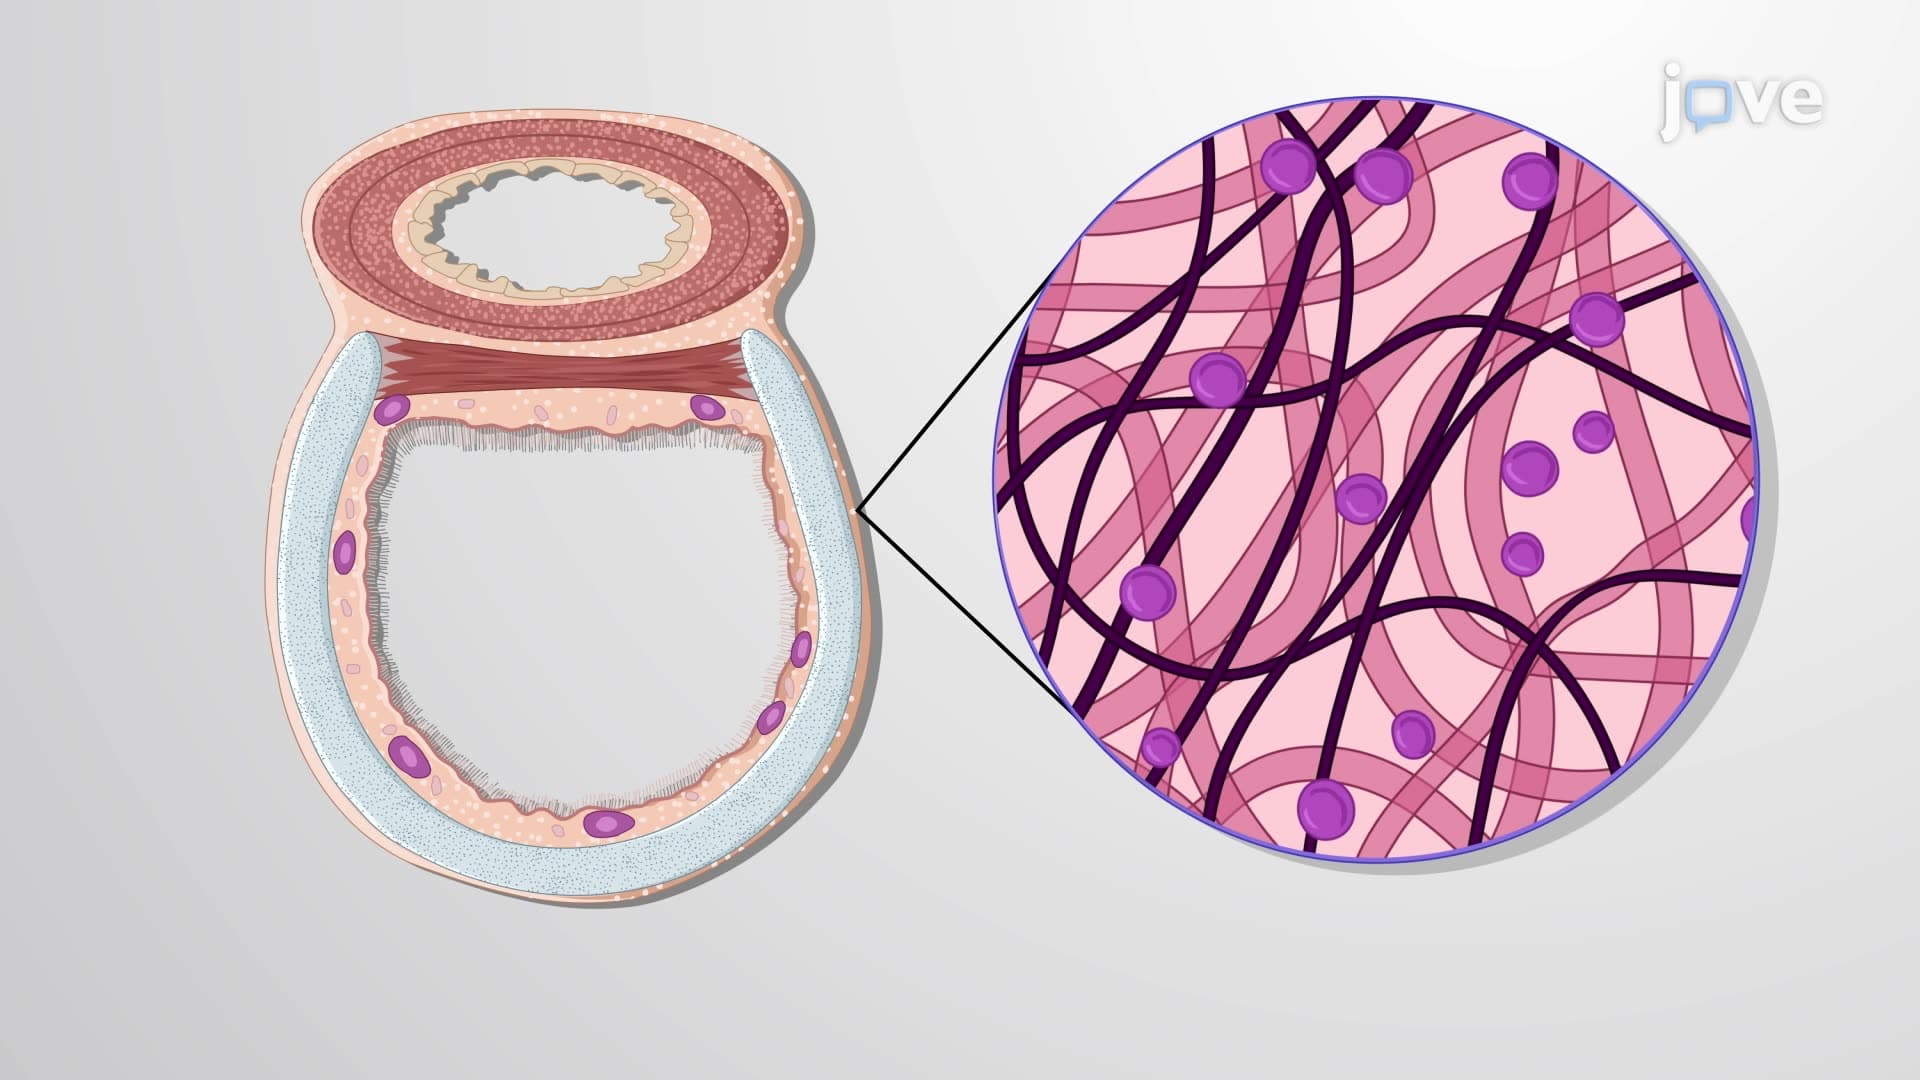
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:15
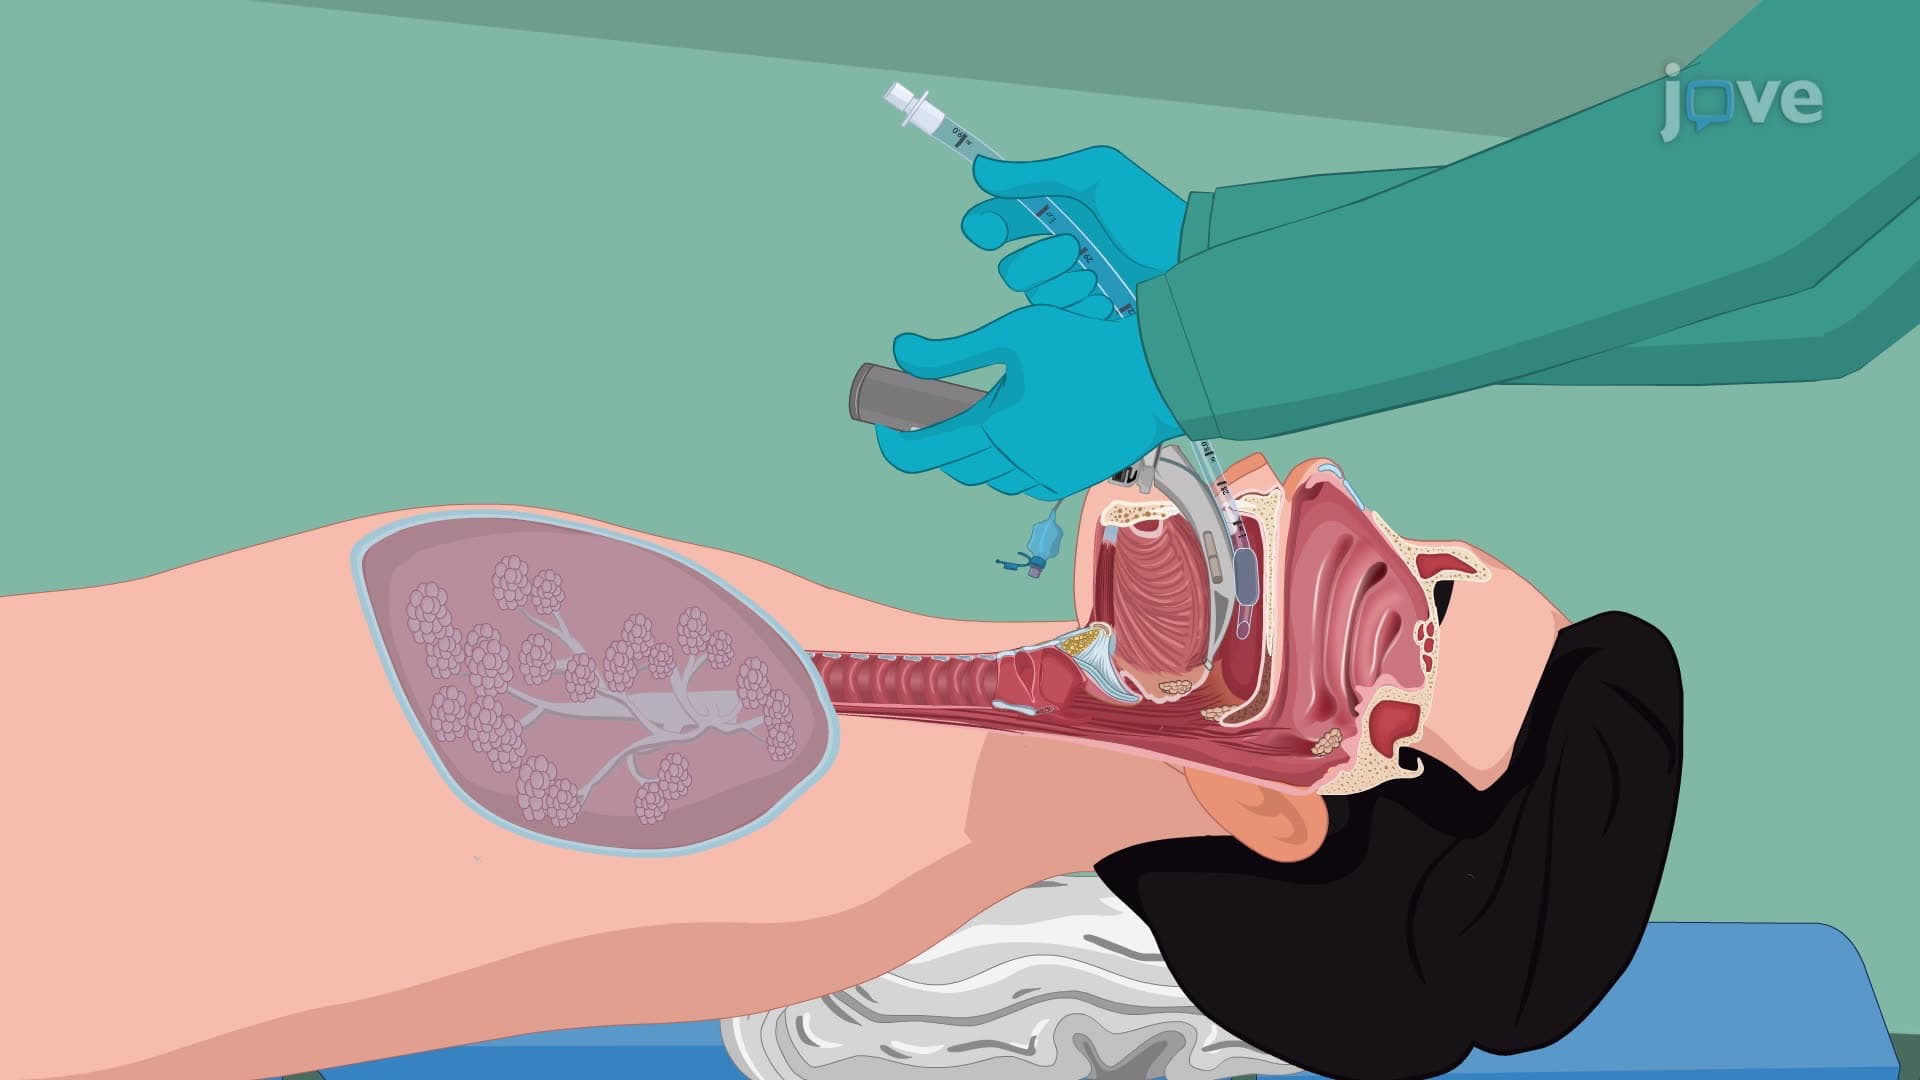
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques