Related Experiment Video
Updated: Aug 15, 2026
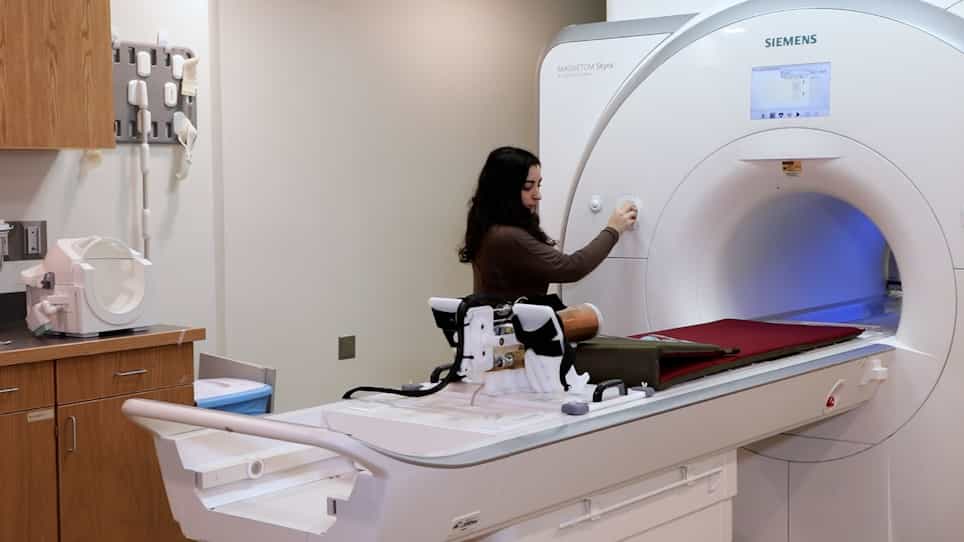
Use of a Foot-Induced Digitally Controlled Resistance Device for Functional Magnetic Resonance Imaging Evaluation in Patients with Foot Paresis
Published on: July 7, 2023
Differential diagnosis of pedal osteomyelitis and diabetic neuroarthropathy: MR Imaging
Hans Peter Ledermann1, William B Morrison
1Universitätsspital Basel, Dep. diagn. Radiologie, Basel, Switzerland.

Abstract:
Almost all diabetic foot infections originate from a foot ulcer. Decreased pain perception and structural deformities such as previous partial foot amputation, Charcot joints, and toe deformity in combination with chronic ischemia lead to a propensity for skin breakdown and subsequent infection. Magnetic resonance (MR) imaging is increasingly performed to evaluate for potential bone infection, but diagnosis of osteomyelitis can be complicated because signal changes from acute Charcot arthropathy, fractures, and postoperative residues may be mistaken for infection. Signal alterations of bone infection may be atypical in sclerosing osteomyelitis and gangrene. Differentiation between osteomyelitis and acute or subacute neuroarthropathy requires careful analysis of the location of bone signal alterations, their distribution, and pattern because qualitative changes are often identical. Presence of secondary signs such as adjacent ulcer, cellulitis, and sinus tract is indicative of osteomyelitis. Differentiation of noninfected neuroarthropathy from infected neuroarthropathy based on MR examinations is difficult. Presence of a sinus tract, disappearance of subchondral cysts, diffuse bone marrow abnormality, and bone erosions are in favor of infection.