Related Experiment Video
Updated: Aug 15, 2026

Model of Ischemia and Reperfusion Injury in Rabbits
Published on: November 3, 2023
Anatomic distribution of myocardial ischemia as a determinant of exercise-induced ST-segment depression
Jonathan W Weinsaft1, Franklin J Wong, Jeff Walden
1Department of Medicine, Greenberg Division of Cardiology, New York Presbyterian Hospital-Weill Cornell Medical Center, New York, NY, USA.

Insights
The anatomical distribution of cardiac ischemia influences the relationship between ST depression and perfusion defects. This finding suggests that ST depression magnitude alone may inaccurately assess coronary artery disease.
Area of Science:
- Cardiology
- Nuclear Cardiology
- Diagnostic Imaging
Background:
- ST depression on electrocardiography (ECG) is a common indicator of myocardial ischemia.
- Single-photon emission computed tomography (SPECT) is used to assess myocardial perfusion and quantify ischemia.
- The relationship between ECG findings and SPECT data is crucial for diagnosing coronary artery disease (CAD).
Purpose of the Study:
- To investigate the correlation between ST depression and SPECT-derived perfusion defects.
- To determine if the anatomical distribution of ischemia affects this correlation.
- To evaluate the impact of ischemia distribution on the accuracy of assessing CAD using ST depression.
Main Methods:
- Retrospective analysis of 129 patients with inducible ST depression (>0.1 mV) and reversible perfusion defects on SPECT.
- Patients categorized into groups with anatomically contiguous (n=68) or opposed (n=61) ischemic regions.
- Correlation and multivariate regression analyses performed to assess relationships between ST depression magnitude, defect size, and severity.
Main Results:
- In the contiguous ischemia group, ST depression correlated significantly with defect size (r=0.40) and severity (r=0.38).
- In the opposed ischemia group, ST depression did not significantly correlate with defect extent or severity.
- ST depression was paradoxically greater in the contiguous ischemia group compared to the opposed group, even after adjusting for perfusion indexes (p<0.001).
Conclusions:
- The anatomical distribution of myocardial ischemia significantly alters the relationship between ST depression and functional indicators of ischemia.
- Relying solely on ST depression magnitude may lead to inaccurate assessments of coronary artery disease.
- Considering the spatial pattern of ischemia is essential for improving the diagnostic accuracy of ECG in patients with suspected CAD.
Abstract:
Cardiac single-photon emission computed tomographic correlates of ST depression were examined in 129 subjects who had inducible ST depression of > or =0.1 mV and reversible perfusion defects. Patients were separated on the basis of single-photon emission computed tomographic defect distribution into a group with anatomically contiguous ischemia (anterior or posterior/inferior defects, n = 68) and a group with anatomically opposed ischemia (anterior and posterior/inferior defects, n = 61). ST depression in the contiguous ischemia group correlated with defect size (r = 0.40, p = 0.001) and severity (r = 0.38, p = 0.002); multivariate regression demonstrated each to be independent determinants of ST-depression magnitude (r = 0.51, p <0.001). In the opposed ischemia group, ST depression did not significantly correlate with defect extent or severity. After adjusting for differences in perfusion indexes, ST depression was paradoxically greater in the contiguous than in the opposed group (2.82 +/- 1.15 vs 2.44 +/- 1.15 mm, p <0.001). In conclusion, these findings demonstrate that the anatomic distribution of ischemia can alter the relation between ST depression and functional indexes of ischemia and may confound the accuracy of assessments of coronary artery disease based on ST-depression magnitude alone.
More Related Videos
 08:13
In Vivo Quantitative Assessment of Myocardial Structure, Function, Perfusion and Viability Using Cardiac Micro-computed Tomography
Published on: February 16, 2016
 11:17
A Microscopic 2,3,5-Triphenyltetrazolium Chloride Assay for Accurate and Reliable Analysis of Myocardial Injury
Published on: November 28, 2025
Related Concept Videos
 01:21
Myocarditis I: Introduction
 01:26
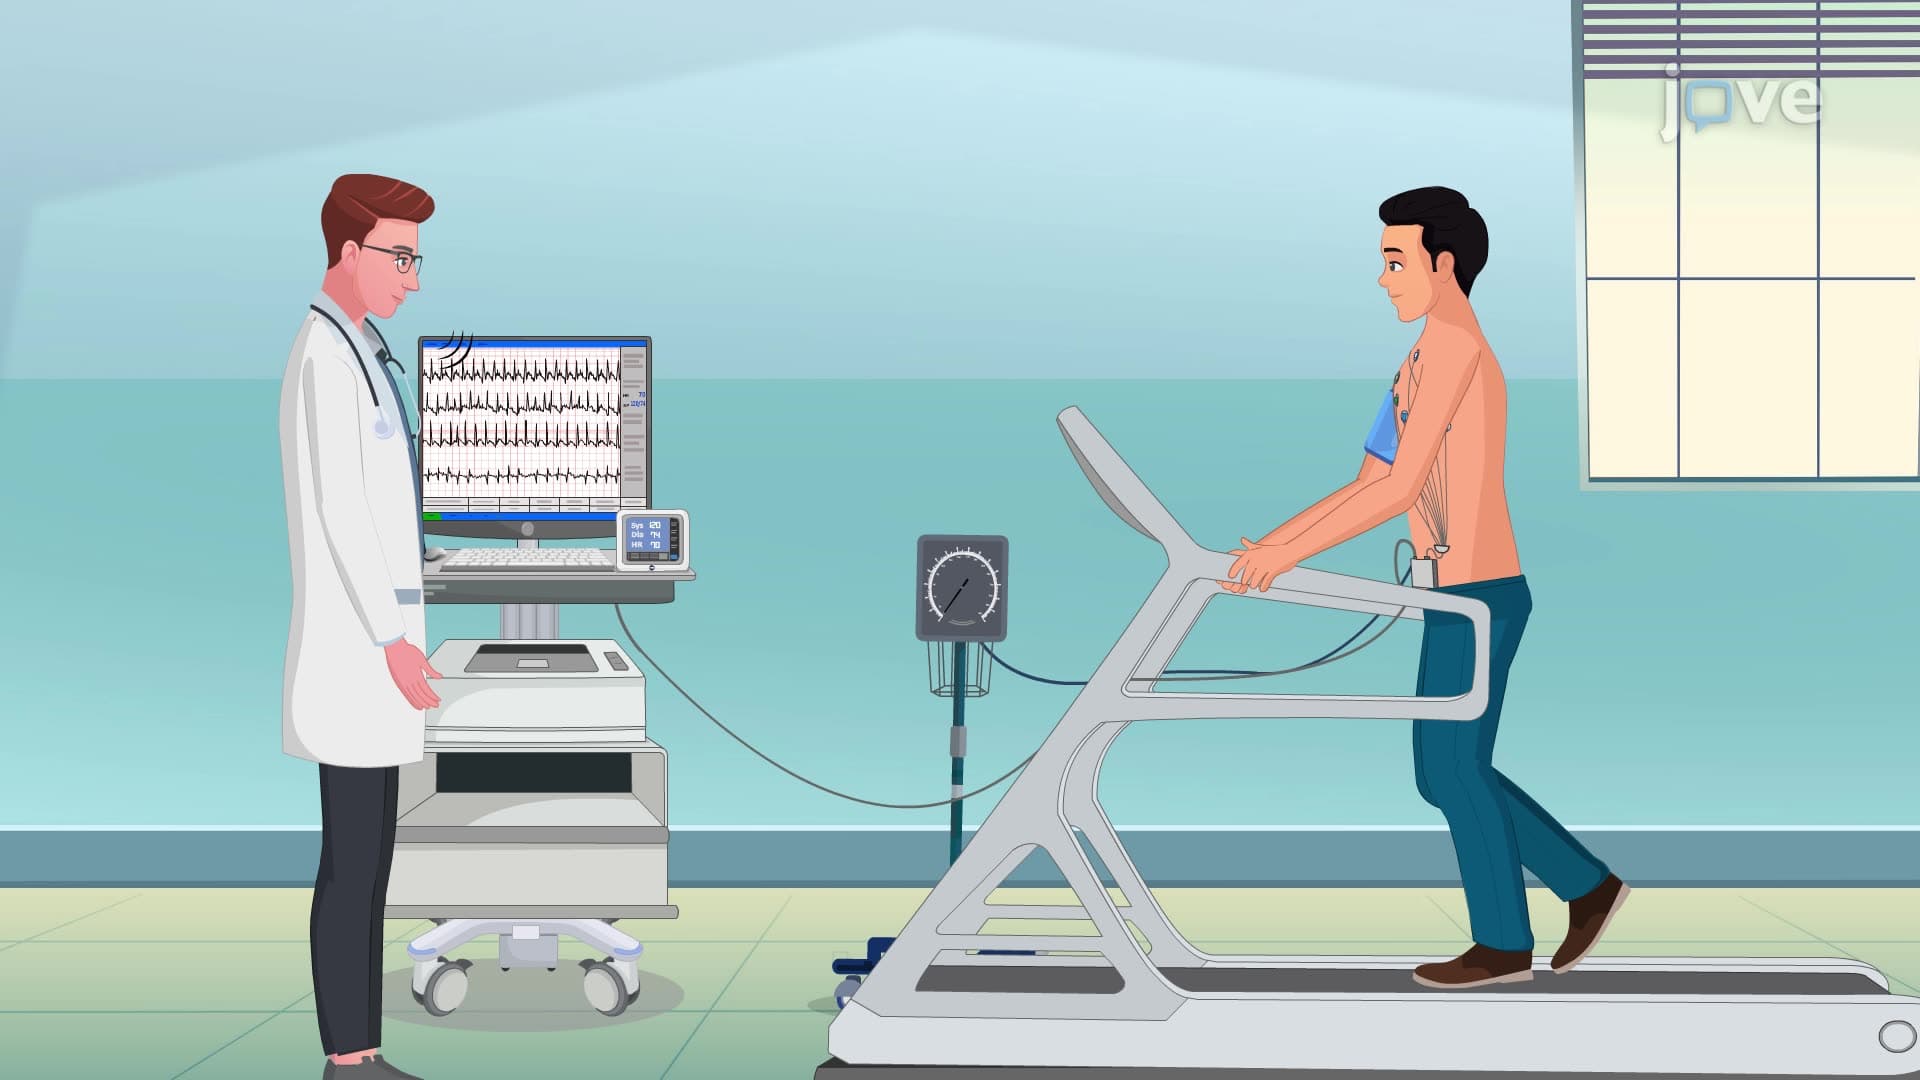
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:30
Acute Coronary Syndrome I: Introduction
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and narrowing...
 01:18
Physiology of the Heart: The Cardiac Cycle
Diastole: The Relaxation Phase
During diastole, all four heart chambers relax. The atrioventricular (AV) valves open, and the semilunar valves close. This phase sees the lowest chamber pressures, promoting ventricular filling. Venous blood enters the heart through the...