Related Experiment Video
Updated: Aug 14, 2026
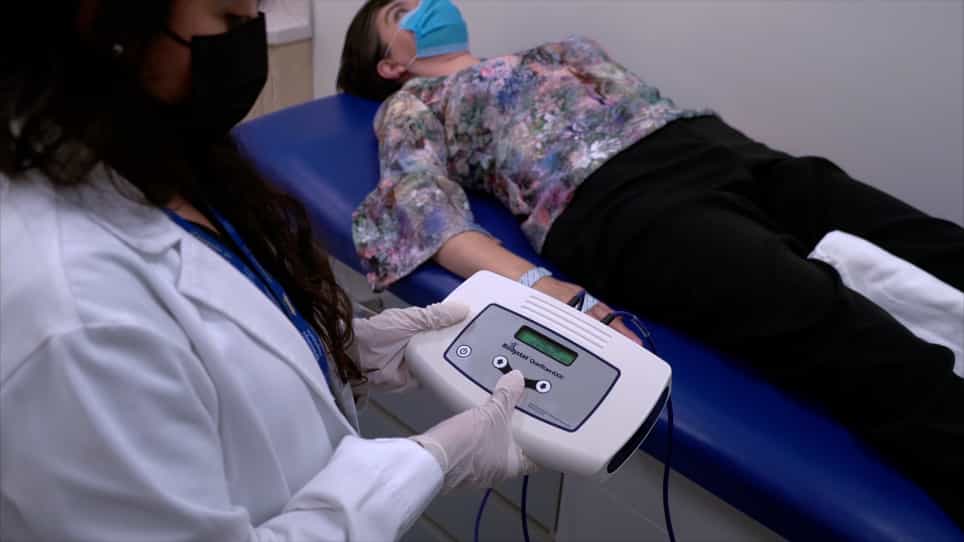

Evaluation of Fluid Overload by Bioelectrical Impedance Vectorial Analysis
Published on: August 17, 2022
Body water and plasma volume in severe community-acquired pneumonia: implications for fluid therapy
Sunit Singhi1, Arvind Sharma, S Majumdar
1Department of Pediatrics, Postgraduate Institute of Medical Education and Research, Chandigarh, India. drsinghi@glide.net.in

Insights
Children with severe pneumonia experience increased extracellular water and plasma volume, which correlates with improved oxygenation. Fluid retention may aid circulation, suggesting fluid restriction should be reconsidered after oxygen levels normalize.
Area of Science:
- Pediatric critical care medicine
- Respiratory medicine
- Clinical physiology
Background:
- Severe pneumonia in children is associated with significant physiological changes.
- Understanding fluid balance is crucial for managing hypoxemia in pediatric pneumonia.
Purpose of the Study:
- To quantify changes in body water and plasma volume in children with severe pneumonia.
- To investigate the relationship between these fluid shifts and oxygenation levels.
- To assess the impact of these changes on mortality.
Main Methods:
- Prospective observational study of 50 children (2-59 months) with severe pneumonia.
- Measurements included total body water, extracellular water, plasma volume, serum sodium, and plasma osmolality during acute illness and recovery.
- Correlations with oxygen saturation (SpO2) and mortality were analyzed.
Main Results:
- Survivors showed increased extracellular water and plasma volume during acute illness compared to recovery.
- Lower serum sodium correlated with increased extracellular water and plasma volume.
- Oxygen saturation demonstrated significant linear relationships with total body water, extracellular water, plasma volume, and serum sodium.
- Extracellular water, blood urea, and plasma volume were significant predictors of SpO2.
Conclusions:
- Moderate increases in extracellular water and plasma volume occur in severe pneumonia, positively correlating with oxygenation.
- Fluid retention appears to support circulating volume in response to hypoxemia.
- Fluid restriction in hypoxemic pneumonia patients may be counterproductive until oxygenation improves.
Objectives:
To determine changes in total and extracellular body water, plasma volume and sodium in children with severe and very severe pneumonia, and examine the association between these changes and oxygenation.
Design:
Prospective, observational.
Subjects:
Fifty children aged 2-59 mths with severe and very severe pneumonia.
Methods:
Serum sodium (SNa), plasma osmolality (Posm), urinary sodium (UNa) and osmolality, total body water (TBW), extracellular water (ECW) and plasma volume (PV) were estimated during the acute phase of pneumonia (within 3-6 hrs of presentation) and after recovery. These were correlated with oxygen saturation (SpO(2)) recorded on presentation.
Results:
All children had cough, fever, tachypnoea and chest-wall indrawing; 70% had inability to feed and 90% were hypoxaemic (SpO(2) < or = 90%). During the acute phase of illness, among the survivors (n=46), mean (SD) ECW and PV were significantly higher than that after recovery [ECW 318 (45) vs 308 (49) ml/kg, PV 53.2 (2.3) vs 52.1 (2.3) ml/kg, p<0.05]. SNa < or = 135 mmol/L was significantly correlated with ECW and PV excess. SpO(2) showed a significant linear relationship with TBW, ECW and PV (r=0.43, 0.46 and 0.42, respectively, p<0.005) and SNa (r= or <0.33, p=0.02). On multiple regression analysis, ECW, blood urea and PV were significant predictors of SpO(2) (combined r=0.63). The four patients who died had significantly higher Posm and blood urea and lower SpO(2) but in a logistic regression model SpO(2) was the only significant predictor of death (odds ratio 0.54, 95% CI 0.32-0.9, p=0.02).
Conclusion:
ECW and PV were moderately increased in severe and very severe pneumonia and the increase correlated with better oxygenation. These findings suggest that fluid retention in response to hypoxaemia is directed towards improving circulating volume. The current practice of fluid restriction in hypoxaemic patients with severe pneumonia might be logical only after correction of hypoxaemia.

Related Concept Videos
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:22
Acute Kidney Injury VI: Nursing Management
 01:18
Pulmonary Edema II: Pathophysiology
 01:29
Disorder of Water Balance
Dehydration
Dehydration occurs when the body loses fluids (particularly water).
Causes:
The major causes of dehydration include excessive sweating, fever, vomiting, diarrhea, and diuresis.
Signs and Symptoms:
Symptoms primarily include intense...
 01:30
Pneumonia III: Complications and Assessment