Related Experiment Video
Updated: Aug 14, 2026


Transuterine Fetal Tracheal Occlusion Model in Mice
Published on: February 5, 2021
Congenital bronchial atresia in infants and children
Nobuyuki Morikawa1, Tatsuo Kuroda, Toshiro Honna
1Division of General Surgery, National Center for Child Health and Development, Tokyo 157-8535, Japan. morikawa-n@ncchd.go.jp

Insights
Congenital bronchial atresia (CBA) in children often causes symptoms like productive cough and recurrent pneumonia, unlike in adults. Early diagnosis with imaging and pathology is crucial for effective surgical treatment.
Area of Science:
- Pediatric Pulmonology
- Thoracic Surgery
- Medical Imaging
Background:
- Congenital bronchial atresia (CBA) is typically found incidentally in asymptomatic young adults.
- Diagnosis in children is rare, with limited understanding of its pediatric presentation.
Purpose of the Study:
- To clarify the clinical characteristics of congenital bronchial atresia in childhood.
- To describe the spectrum of congenital bronchial atresia in pediatric patients.
Main Methods:
- Retrospective review of 29 pediatric patients (1 day to 13 years) with confirmed CBA.
- Pathological confirmation of a blind-ending bronchus with distal mucous-filled bronchocele and hyperinflated lung parenchyma.
Main Results:
- Most pediatric patients (28/29) were symptomatic, primarily with productive cough and recurrent pneumonia (26 children).
- Imaging modalities like CT, bronchography, and bronchoscopy aided diagnosis, revealing bronchocele and hyperinflation.
- The right lower lobe was the most frequently affected site (12 cases).
Conclusions:
- Congenital bronchial atresia presents distinctively in children, often with symptoms, unlike adults.
- Accurate diagnosis requires advanced imaging and pathology, differentiating it from intralobar sequestration or bronchial cysts.
- CBA is a distinct pediatric condition causing recurrent pneumonia or respiratory distress, necessitating surgical intervention.
Background/Purpose:
Congenital bronchial atresia (CBA) usually presents incidentally in asymptomatic young male adults but is rarely diagnosed in children. The aim of this study was to clarify the clinical characteristics of CBA in childhood and to describe the spectrum of this condition.
Methods:
The clinical features in 29 patients with CBA, aged from 1 day to 13 years (median, 4 years), were reviewed retrospectively. Diagnosis was confirmed by pathological findings of a blind-ending bronchus associated with distal mucous-filled bronchocele surrounded by hyperinflated lung parenchyma.
Results:
All but 1 patient were symptomatic. The most frequent symptom was productive cough and fever owing to recurrent pneumonia found in 26 children. Two infants suffered from respiratory distress. Chest x-ray showed various findings of infiltrative pneumonia, emphysema, and a large cyst. Computed tomography, bronchography, and bronchoscopy were useful modalities for demonstrating bronchocele associated with hyperinflated lung or proximal blind-ending bronchus even in infected cases. The right lower lobe was predominantly affected in 12 cases, followed by left or right upper lobe in 7 cases. Lobectomy or segmentectomy resulted in remarkable clinical improvement.
Conclusions:
Congenital bronchial atresia presents differently in children than in young adults. Modern imaging techniques and careful pathological analyses lead to an accurate diagnosis of bronchial atresia, which may be misdiagnosed as intralobar sequestration or pulmonary bronchial cysts. Bronchial atresia is a distinct pathological entity that accounts for recurrent pneumonia or respiratory distress in childhood, requiring surgical treatment.
Related Concept Videos
 01:17
Pulmonary Cycle: Exhalation
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:05
Breathing
 01:22
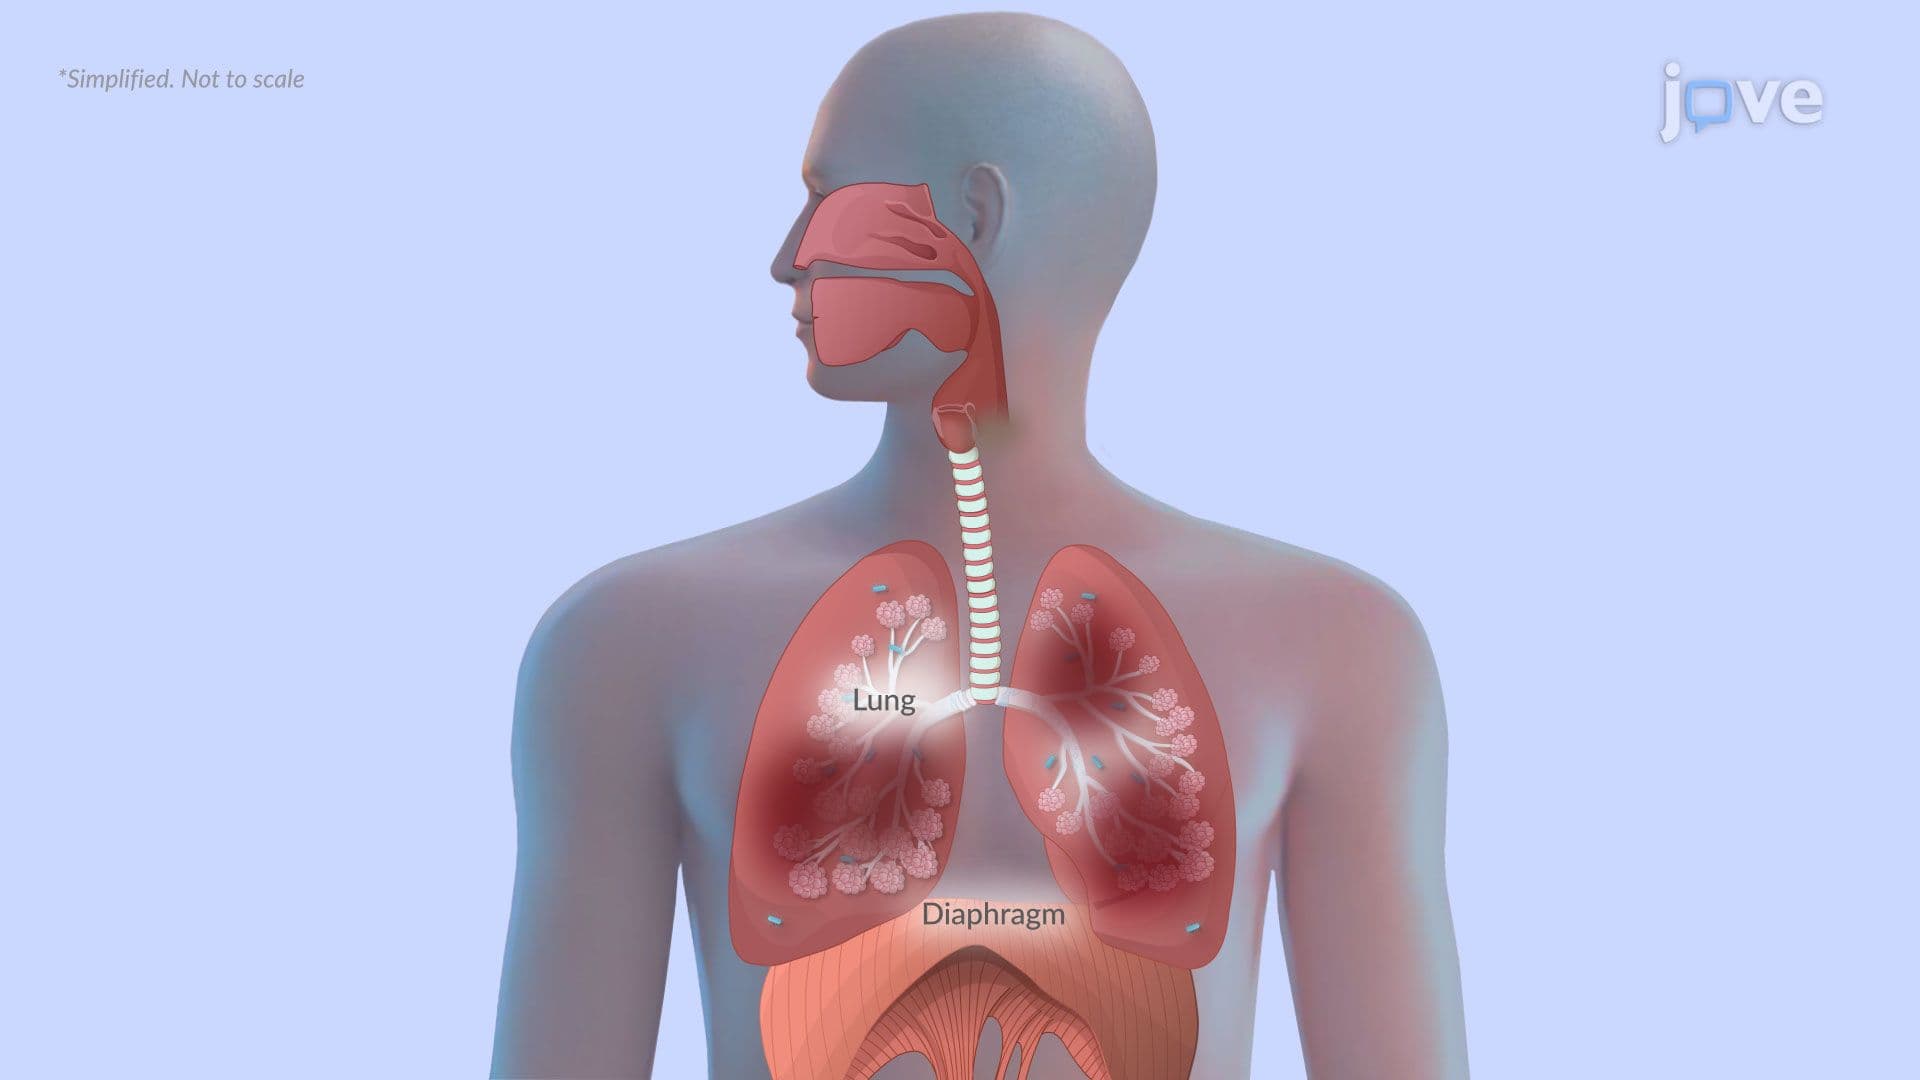
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:31
Anatomy of Respiratory System II: Lower Respiratory Tract
The Larynx
It is located between the pharynx and the trachea, acts as a passageway for air, and hosts several critical structures, such as the epiglottis, vocal cords, and glottis. The epiglottis acts as a gateway, guiding food to the...