Related Experiment Video
Updated: Aug 14, 2026
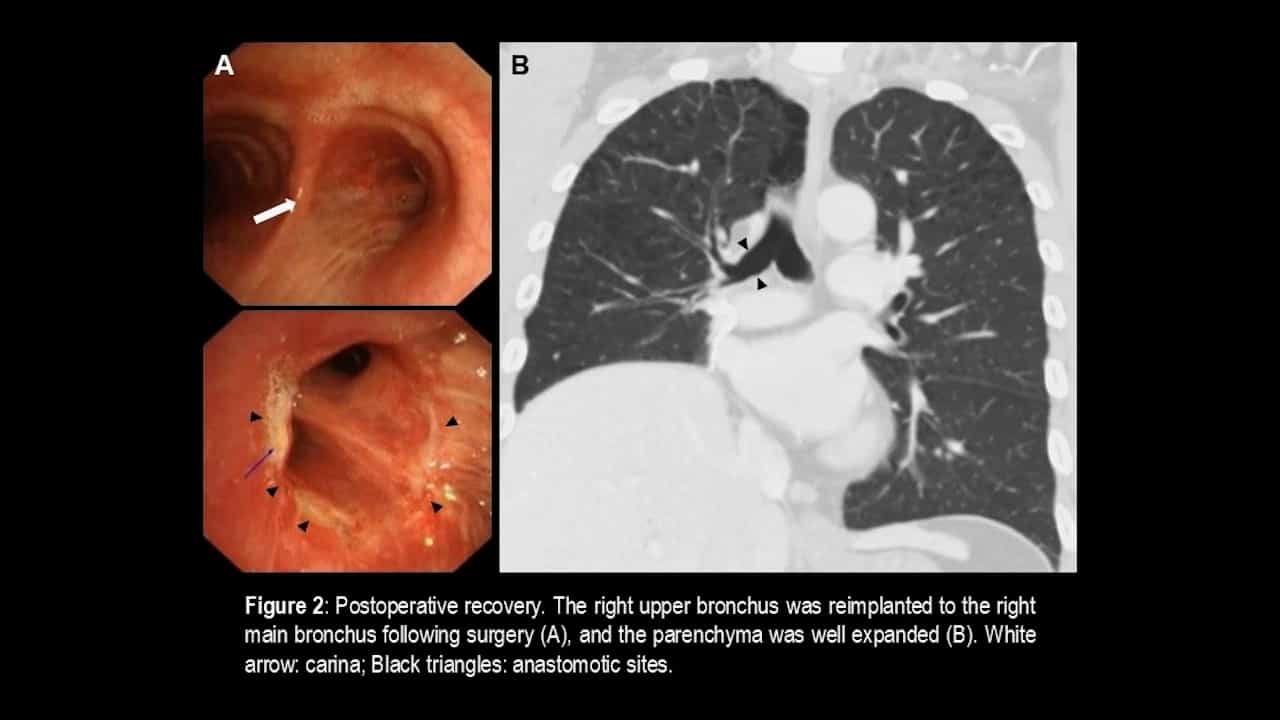
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
Intraoperative (125)I Vicryl mesh brachytherapy after sublobar resection for high-risk stage I non-small cell lung
George Voynov1, Dwight E Heron, Chyongchiou J Lin
1Department of Radiation Oncology, University of Pittsburgh Cancer Institute, Pittsburgh, PA, USA.

Purpose:
To assess the feasibility and outcomes of (125)I Vicryl mesh brachytherapy after sublobar resection in stage I non small cell lung cancer (NSCLC) patients with poor pulmonary function.
Methods And Materials:
Between January 1997 and July 2004, patients with poor cardiopulmonary reserve who had stage IA and IB (T1-2 N0 M0) NSCLC and a forced expiratory volume in 1s (FEV(1)) of > micro=0.6L were considered for limited surgical resection either by an open or video-assisted thoracoscopic procedure and for a subsequent (125)I Vicryl mesh brachytherapy implant. Mediastinal and hilar lymph node staging was performed routinely in all patients. After clear margins were obtained grossly and on frozen section, a single-plane (125)I implant was designed to encompass a plane consisting of the staple line and a 2-cm margin of surrounding visceral pleura. The implant was introduced through the surgical incision and sutured to the visceral pleura. A prescribed dose of 100-120 y was delivered to a volume within 0.5 cm rom the plane of the implant. Follow-up orthogonal films or CTs were obtained for dosimetric analysis. Kaplan-Meier analyses were used to estimate the local control, locoregional control, and overall survival rates.
Results:
Of the 110 patients, 65 had stage IA and 45 had stage IB NSCLC. The mean preoperative FEV(1) was 47% of the predicted volume. With a median follow-up of 11 months (range 1-68 months), there were four recurrences within the radiation volume. The estimated 5-year local (in-field) control, locoregional control, and overall survival rates were 90%, 61%, and 18%, respectively.
Conclusion:
Vicryl mesh brachytherapy after sublobar resection for high-risk stage I NSCLC patients is a feasible procedure, which results in an excellent local (in-field) control rate.
More Related Videos
 04:04
Endobronchial Ultrasound-guided Intratumoral Injection of Cisplatin for the Treatment of Isolated Mediastinal Recurrence of Lung Cancer
Published on: February 12, 2017
 05:22
Intraoperative Strategy under Complex Vascular Adhesion for Laparoscopic Radical Resection of Bismuth-Corlette Type IIIb Perihilar Cholangiocarcinoma
Published on: February 13, 2026