Related Experiment Video
Updated: Aug 14, 2026
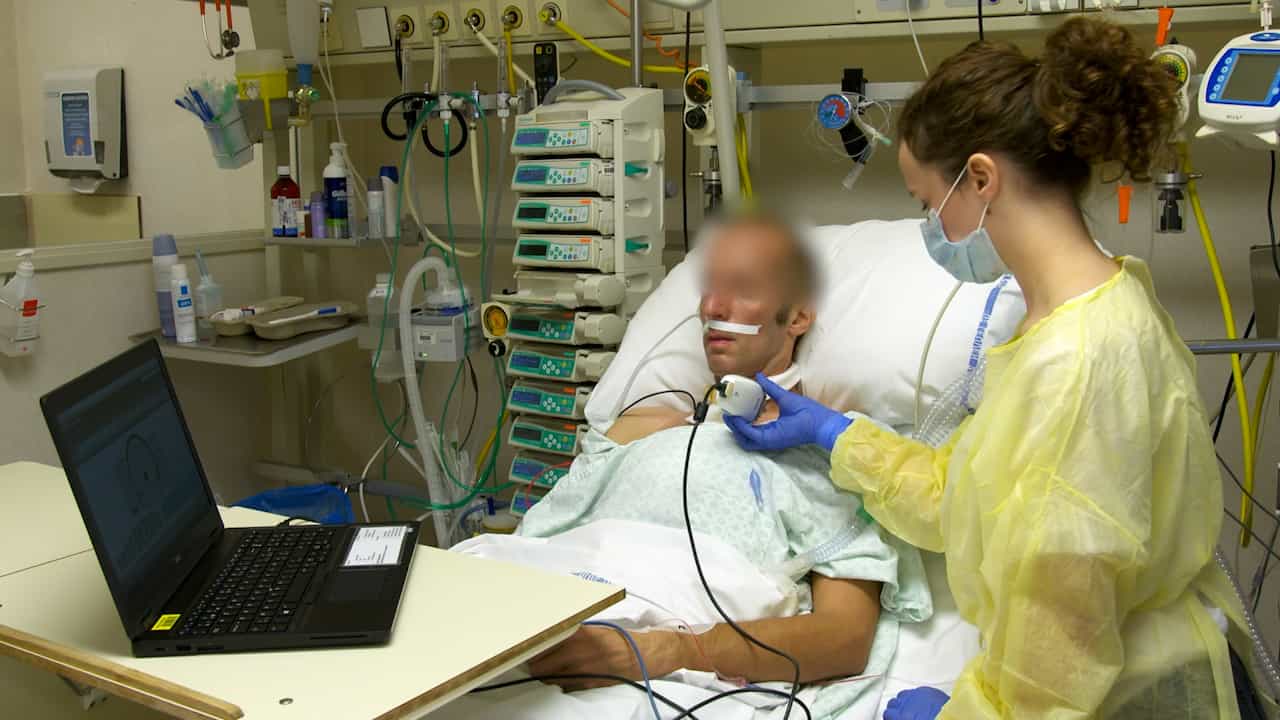

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Bench-to-bedside review: weaning failure--should we rest the respiratory muscles with controlled mechanical
Theodoros Vassilakopoulos1, Spyros Zakynthinos, Charis Roussos
1Department of Critical Care and Pulmonary Services, University of Athens Medical School, Evangelismos Hospital, Athens, Greece. tvassil@med.uoa.gr

Abstract:
The use of controlled mechanical ventilation (CMV) in patients who experience weaning failure after a spontaneous breathing trial or after extubation is a strategy based on the premise that respiratory muscle fatigue (requiring rest to recover) is the cause of weaning failure. Recent evidence, however, does not support the existence of low frequency fatigue (the type of fatigue that is long-lasting) in patients who fail to wean despite the excessive respiratory muscle load. This is because physicians have adopted criteria for the definition of spontaneous breathing trial failure and thus termination of unassisted breathing, which lead them to put patients back on the ventilator before the development of low frequency respiratory muscle fatigue. Thus, no reason exists to completely unload the respiratory muscles with CMV for low frequency fatigue reversal if weaning is terminated based on widely accepted predefined criteria. This is important, since experimental evidence suggests that CMV can induce dysfunction of the diaphragm, resulting in decreased diaphragmatic force generating capacity, which has been called ventilator-induced diaphragmatic dysfunction (VIDD). The mechanisms of VIDD are not fully elucidated, but include muscle atrophy, oxidative stress and structural injury. Partial modes of ventilatory support should be used whenever possible, since these modes attenuate the deleterious effects of mechanical ventilation on respiratory muscles. When CMV is used, concurrent administration of antioxidants (which decrease oxidative stress and thus attenuate VIDD) seems justified, since antioxidants may be beneficial (and are certainly not harmful) in critical care patients.

Related Concept Videos
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...