Related Experiment Video
Updated: Aug 14, 2026
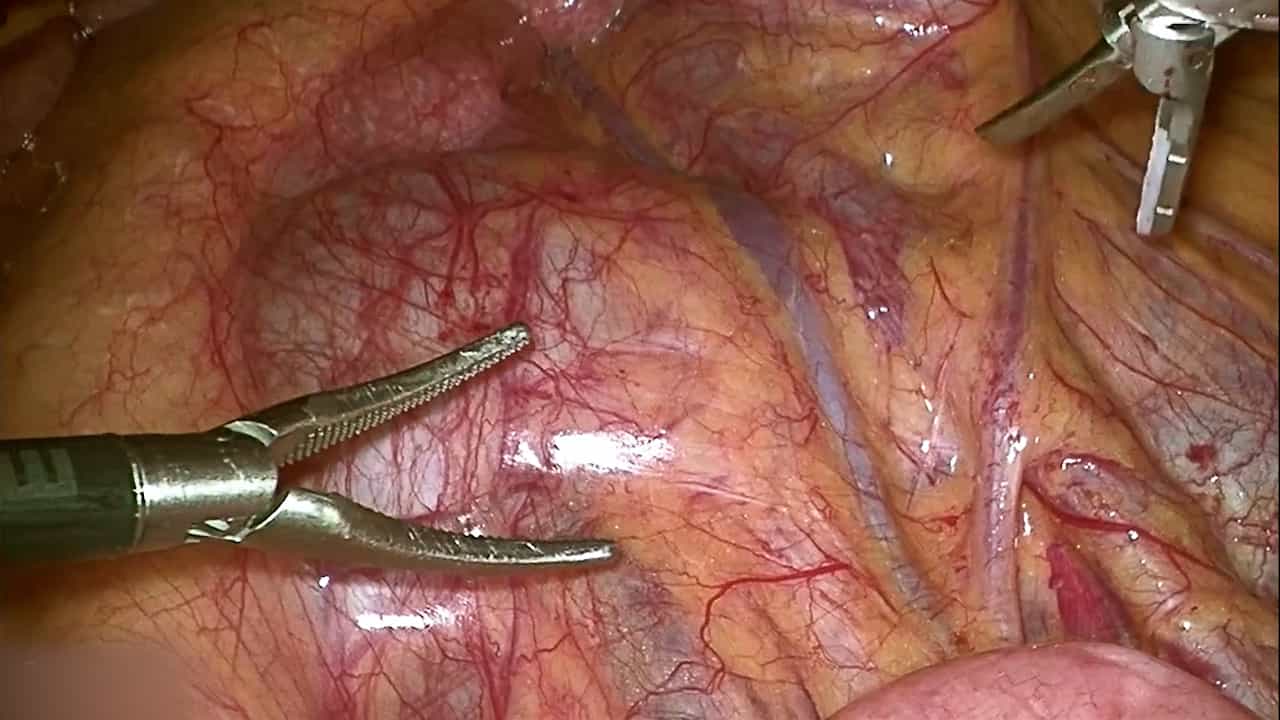
Transmesenteric Laparoscopic Pyeloplasty in Trendelenburg Position for Horseshoe Kidney with Hydronephrosis
Published on: July 8, 2025
Is retrograde stenting more reliable than antegrade stenting for pyeloplasty in infants and children?
1Department of Pediatric Surgery and Pediatric Urology, Rainbow Children's Hospital, Hyderabad, Andhra Pradesh, India. vvsssekharam@yahoo.co.in

Insights
Retrograde double-J stenting is more effective than antegrade stenting for pediatric pyeloplasty drainage, offering higher success rates and fewer complications. This comparison aids in choosing the optimal stenting method for children undergoing pyeloplasty.
Area of Science:
- Pediatric Urology
- Surgical Techniques
- Medical Device Placement
Background:
- Pyeloplasty is a common surgical procedure for pediatric ureteropelvic junction obstruction.
- Internal double-J stenting is frequently used to ensure adequate drainage post-pyeloplasty.
- Both antegrade and retrograde approaches exist for double-J stent placement.
Purpose of the Study:
- To compare the efficacy and safety of antegrade versus retrograde double-J stenting in pediatric pyeloplasty.
- To evaluate success rates of stent placement and associated complications between the two techniques.
Main Methods:
- A cohort of 42 children with unilateral pelviureteral junction obstruction underwent pyeloplasty.
- Antegrade stenting was attempted in 17 children, and retrograde stenting in 25 children.
- Stent placement success and complications were recorded; stents were removed after 4 weeks.
Main Results:
- Successful stent placement was achieved in 82% of the antegrade group and 96% of the retrograde group.
- Retrograde stenting demonstrated a higher success rate (96%) and no malpositioning complications.
- Children with successful stenting were discharged within 72 hours, while unsuccessful cases required longer hospital stays.
Conclusions:
- Retrograde double-J stenting appears more reliable for pediatric pyeloplasty compared to the antegrade approach.
- The retrograde technique offers superior success rates and a lower incidence of complications.
- This suggests retrograde stenting as a preferred method for drainage in pediatric pyeloplasty.
Objectives:
To compare antegrade and retrograde internal double-J stenting for pyeloplasty drainage in children. The success of placing the stent in position and the complications were compared in both groups.
Methods:
Between October 2001 and December 2004, 42 children with unilateral pelviureteral junction obstruction underwent pyeloplasty by a single surgeon. Antegrade and retrograde double-J stenting was attempted in 17 children (mean age 1.3 years) and 25 children (mean age 1.5 years), respectively. Antegrade stenting was attempted during the pelviureteral anastomosis, and the retrograde stent was placed just before the operation by cystoscopy. Fluoroscopy was not routinely used to confirm stent placement in either group. The stents were removed 4 weeks later at cystoscopy.
Results:
Successful stent placement without malpositioning was achieved in 14 (82%) of 17 and 24 (96%) of 25 children, respectively, in the antegrade and retrograde groups. The cause of unsuccessful stenting in both groups was the inability to cross the ureterovesical junction. The mean time taken for retrograde stenting was 9 minutes (range 6 to 15). All children with successful stent placement by either technique were discharged within 72 hours after the operation. The hospital stay for children with unsuccessful double-J stent placement varied from 7 to 10 days. No stent malpositioning occurred with retrograde stenting; 1 child in the antegrade stent group had a malpositioned stent in the distal ureter, which was retrieved at ureteroscopy.
Conclusions:
In our experience, retrograde double-J stenting seems more reliable than antegrade stenting for pediatric pyeloplasty, with greater success and lower complication rates.

Related Concept Videos
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography
 01:26
Kidney Transplant II: Surgical Procedure