Related Experiment Video
Updated: Oct 11, 2026
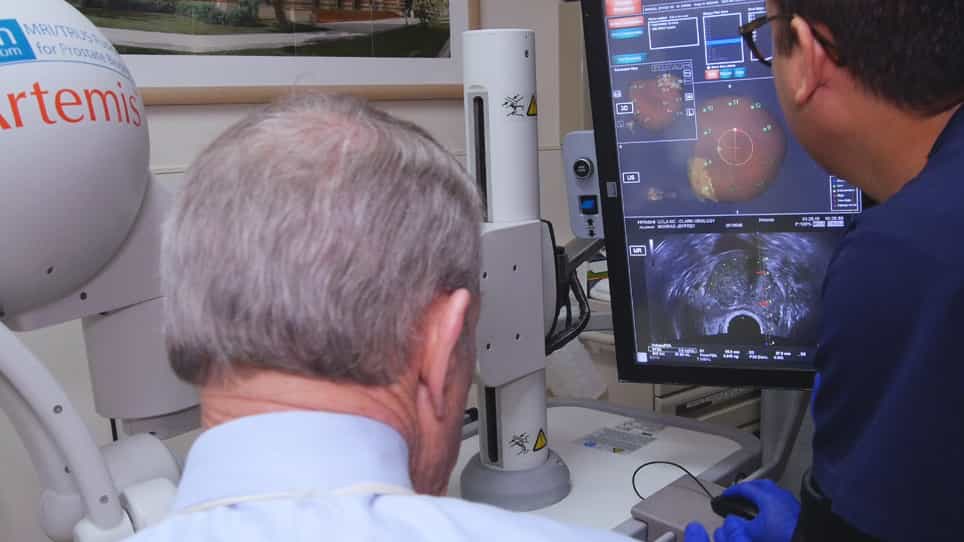
Use of MRI-ultrasound Fusion to Achieve Targeted Prostate Biopsy
Published on: April 9, 2019
Perilesional Biopsy in-Systematic Out? Comparative Analysis of Targeted, Perilesional, and Systematic Core Yield by
Viktor Alargkof1, Manuel Walter2, Christian Engesser1
1University Hospital Basel, Department of Urology, Basel, Switzerland; University of Basel, Basel, Switzerland.

Objective:
To characterize prostate cancer (Pca) detection rates by Gleason Grade Group (GG) in targeted, perilesional, and systematic cores sampling the remaining prostate using robotic-assisted transperineal magnetic resonance imaging (MRI) /ultrasound fusion biopsy (RA-TP-FBx), enabling precise spatial documentation of every core relative to MRI-lesions and the prostate.
Methods:
We analyzed prospectively collected RA-TP-FBx cases between 2020 and 2024. Biopsies were performed with the iSR'obot Mona Lisa (Biobot). Sampling included a traditional targeted + systematic strategy and a Trizonal approach: targeted + perilesional + systematic. Perilesional cores were defined at biopsy as samples within 10 mm of the MRI-lesion margin and systematic cores as samples outside the targeted-perilesional areas. Individualized 3D prostate maps were correlated with per-core histopathology. Clinically significant PCa (csPCa) was defined as GG ≥ 2.
Results:
The full cohort included 566 RA-TP-FBx cases. Diagnosis of csPCa (n=131 in the Trizonal cohort) was exclusively due to perilesional sampling in 6.1% (8/131). Systematic biopsy detected csPCa not captured by targeted or perilesional cores in 3.8% (5/131), but only 1.5% (2/131) originated from MRI-negative lobes. Overdetection of GG 1 (n = 58 in the Trizonal cohort) would be reduced by 24.1% (14/58) by omitting systematic cores when targeted and perilesional cores were negative.
Conclusion:
Robotic-assisted mapping demonstrated that perilesional sampling effectively complemented targeted biopsy, while systematic cores yielded minimal additional csPCa detection but increased GG 1 overdetection. These data support adopting targeted + perilesional sampling and omitting or deintensifying the routine addition of systematic cores in the remaining prostate.
