Related Experiment Video
Updated: Aug 13, 2026
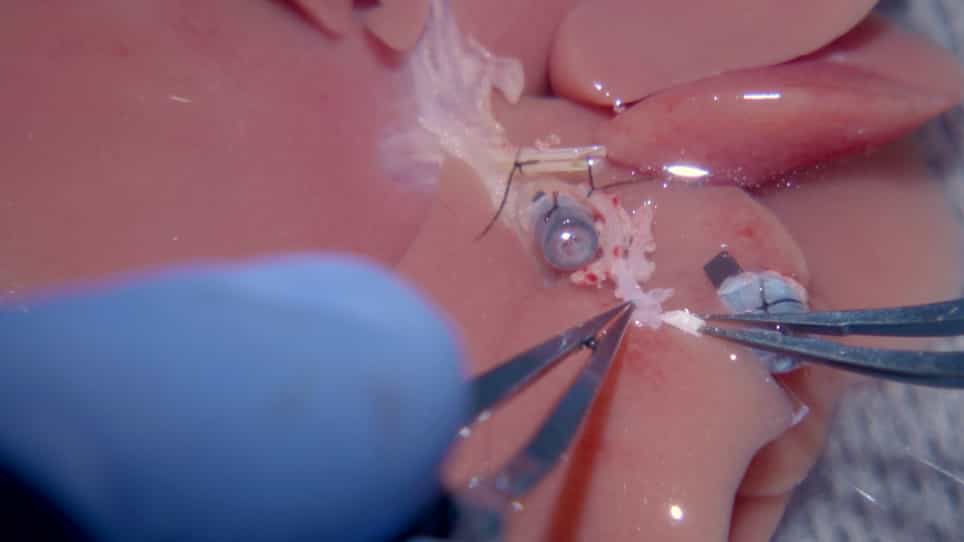
Reduced Complications after Arterial Reconnection in a Rat Model of Orthotopic Liver Transplantation
Published on: November 7, 2020
Long-term effect of hepatitis C virus chronic infection on patient and renal graft survival
O Bestard1, J M Cruzado, J Torras
1From the Servei de Nefrologia, Hospital Universitari de Bellvitge, University of Barcelona, Spain.

Background:
Hepatitis C virus (HCV) infection increases morbimortality in renal transplantation. The immune response against the HVC is not predictable in a great proportion of patients developing into chronic liver disease, glomerulonephritis, or both.
Patients:
We analyzed the impact of posttransplant chronic hepatitis development on patient and graft survival in 200 HCV-positive/HBsAg-negative renal allograft recipients transplanted between 1981 and 2003.
Results:
Ninety-eight patients developed chronic ALT elevation (ALT+), while 102 did not (ALT-). There was no difference in acute rejection episodes (ARE), acute tubular necrosis, donor and recipient age, gender, HLA mismatches, and number of previous renal transplants. Development of ALT+ was associated with a worse patient survival (90% vs 65% at 15 years of follow-up, P = .007; RR = 3.8, CI = 1.4-10.1), an effect that was independent of other variables as time on dialysis and age. The main causes of death among ALT+ were chronic liver disease (52%), cardiovascular (26%), and infection (13%), whereas in ALT- they were cardiovascular (33%), cancer (33%), and chronic liver disease (16%). Conversely, graft survival (censoring for patient death with a functioning graft) was higher among ALT+ (50% vs 35% at 15 years of follow-up, P = .04; RR = 1.5, CI = 1.19-2.22). Causes of graft loss in ALT- patients were chronic allograft nephropathy (CAN, 53%), glomerulonephritis (GN, 18%), acute rejection episode (AR, 22%), and death (5%), whereas among ALT+ they were CAN (36%), GN (31%), ARE (10%), and death (21%; P = .01). By multivariate analysis, ALT- (RR = 1.6, CI = 1.07-2.55, P = .02) and de novo GN (RR = 2, CI = 1.29-3.09, P = .002) were associated with worse renal allograft survival.
Conclusion:
Our results suggested that a better immune response against the HCV lead to greater patient survival but poorer graft survival.
Related Concept Videos
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:28
Kidney Transplant I: Introduction
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:25
Hepatitis
 01:14
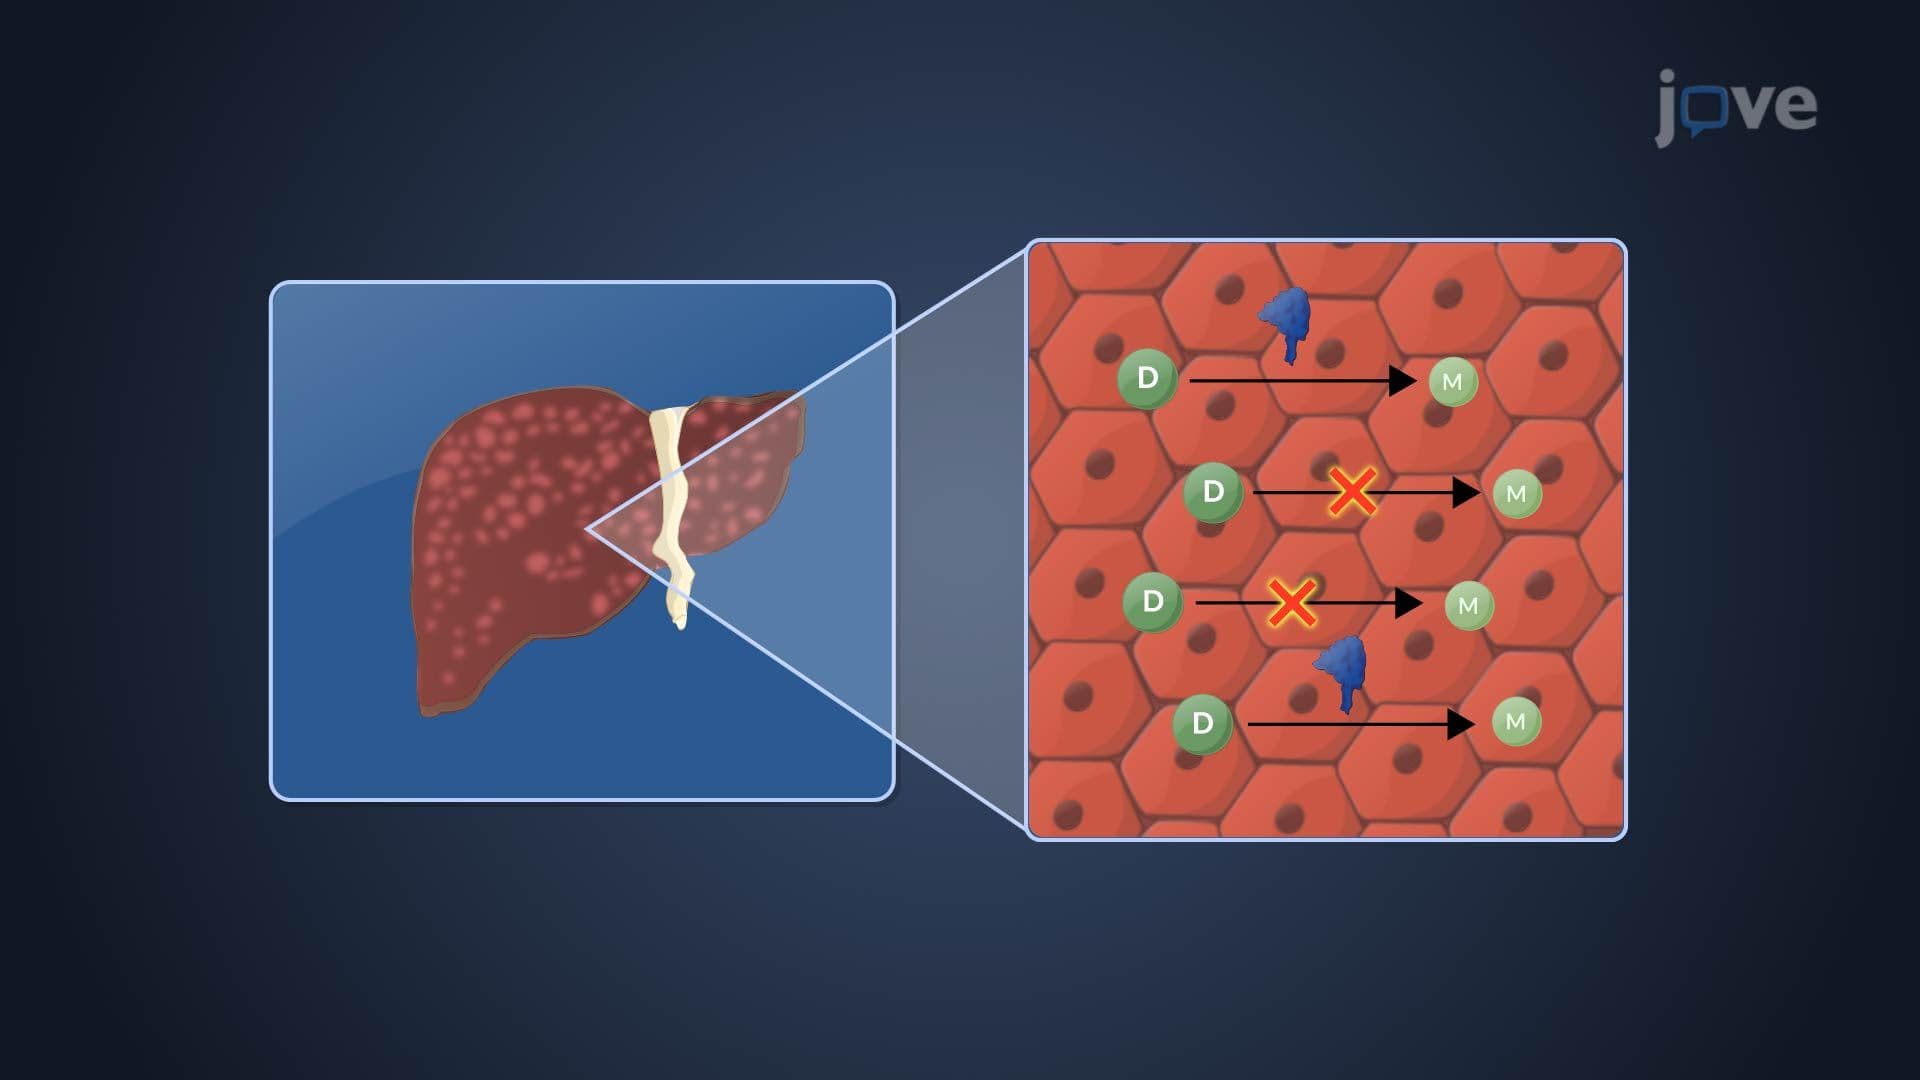
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug