Related Experiment Video
Updated: Aug 13, 2026


Evaluation of Coronary Flow Reserve After Myocardial Ischemia Reperfusion in Rats
Published on: June 28, 2019
Coronary flow reserve is preserved in white-coat hypertension
D Erdogan1, H Gullu, M Caliskan
1Cardiology Department, Konya Teaching and Medical Research Center, Baskent University, Konya, Turkey. aydoganer@yahoo.com

Insights
White-coat hypertension (WCH) does not impact coronary flow reserve (CFR). This study found preserved CFR in WCH patients, similar to healthy individuals, suggesting WCH is not associated with impaired cardiac microvascular function.
Area of Science:
- Cardiology
- Hypertension Research
- Echocardiography
Background:
- White-coat hypertension (WCH) is characterized by elevated blood pressure in clinical settings but normal readings outside.
- The impact of WCH on cardiovascular health, particularly coronary microvascular function, remains incompletely understood.
- Coronary flow reserve (CFR) is a key indicator of myocardial perfusion and microvascular health.
Purpose of the Study:
- To investigate the potential influence of white-coat hypertension (WCH) on coronary flow reserve (CFR).
- To compare CFR in patients with WCH, sustained hypertension, and healthy controls.
Main Methods:
- Coronary flow reserve (CFR) was assessed using transthoracic second harmonic Doppler echocardiography.
- The study included three groups: 29 patients with WCH, 32 with sustained hypertension, and 35 healthy volunteers.
- Data analysis compared CFR values across the three participant groups.
Main Results:
- Coronary flow reserve (CFR) was significantly lower in patients with sustained hypertension compared to both WCH and control groups.
- No significant difference in CFR was observed between patients with WCH and healthy control subjects.
- Mean CFR values were 2.40 (SD 0.54) for sustained hypertension, 2.77 (0.41) for WCH, and 2.83 (0.60) for controls.
Conclusions:
- Coronary flow reserve (CFR) is preserved in individuals diagnosed with white-coat hypertension (WCH).
- WCH does not appear to be associated with impaired coronary microvascular function.
- These findings suggest that WCH may represent a distinct pathophysiological entity compared to sustained hypertension regarding cardiac hemodynamics.
Objectives:
To assess the possible influence of white-coat hypertension (WCH) on coronary flow reserve (CFR).
Methods:
CFR was measured by means of transthoracic second harmonic Doppler echocardiography in 29 patients with WCH, 32 patients with sustained hypertension and 35 healthy volunteers.
Results:
CFR was significantly lower in the sustained hypertension group than in the WCH and the control groups, but it was not different between the WCH and the control groups (2.40 (SD 0.54), 2.77 (0.41) and 2.83 (0.60), respectively).
Conclusion:
CFR is preserved in patients with WCH.

Related Concept Videos
 01:17
Measurement of Blood Pressure
 01:29
Hypertension II: Pathophysiology
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:29
Heart Failure II: Pathophysiology
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
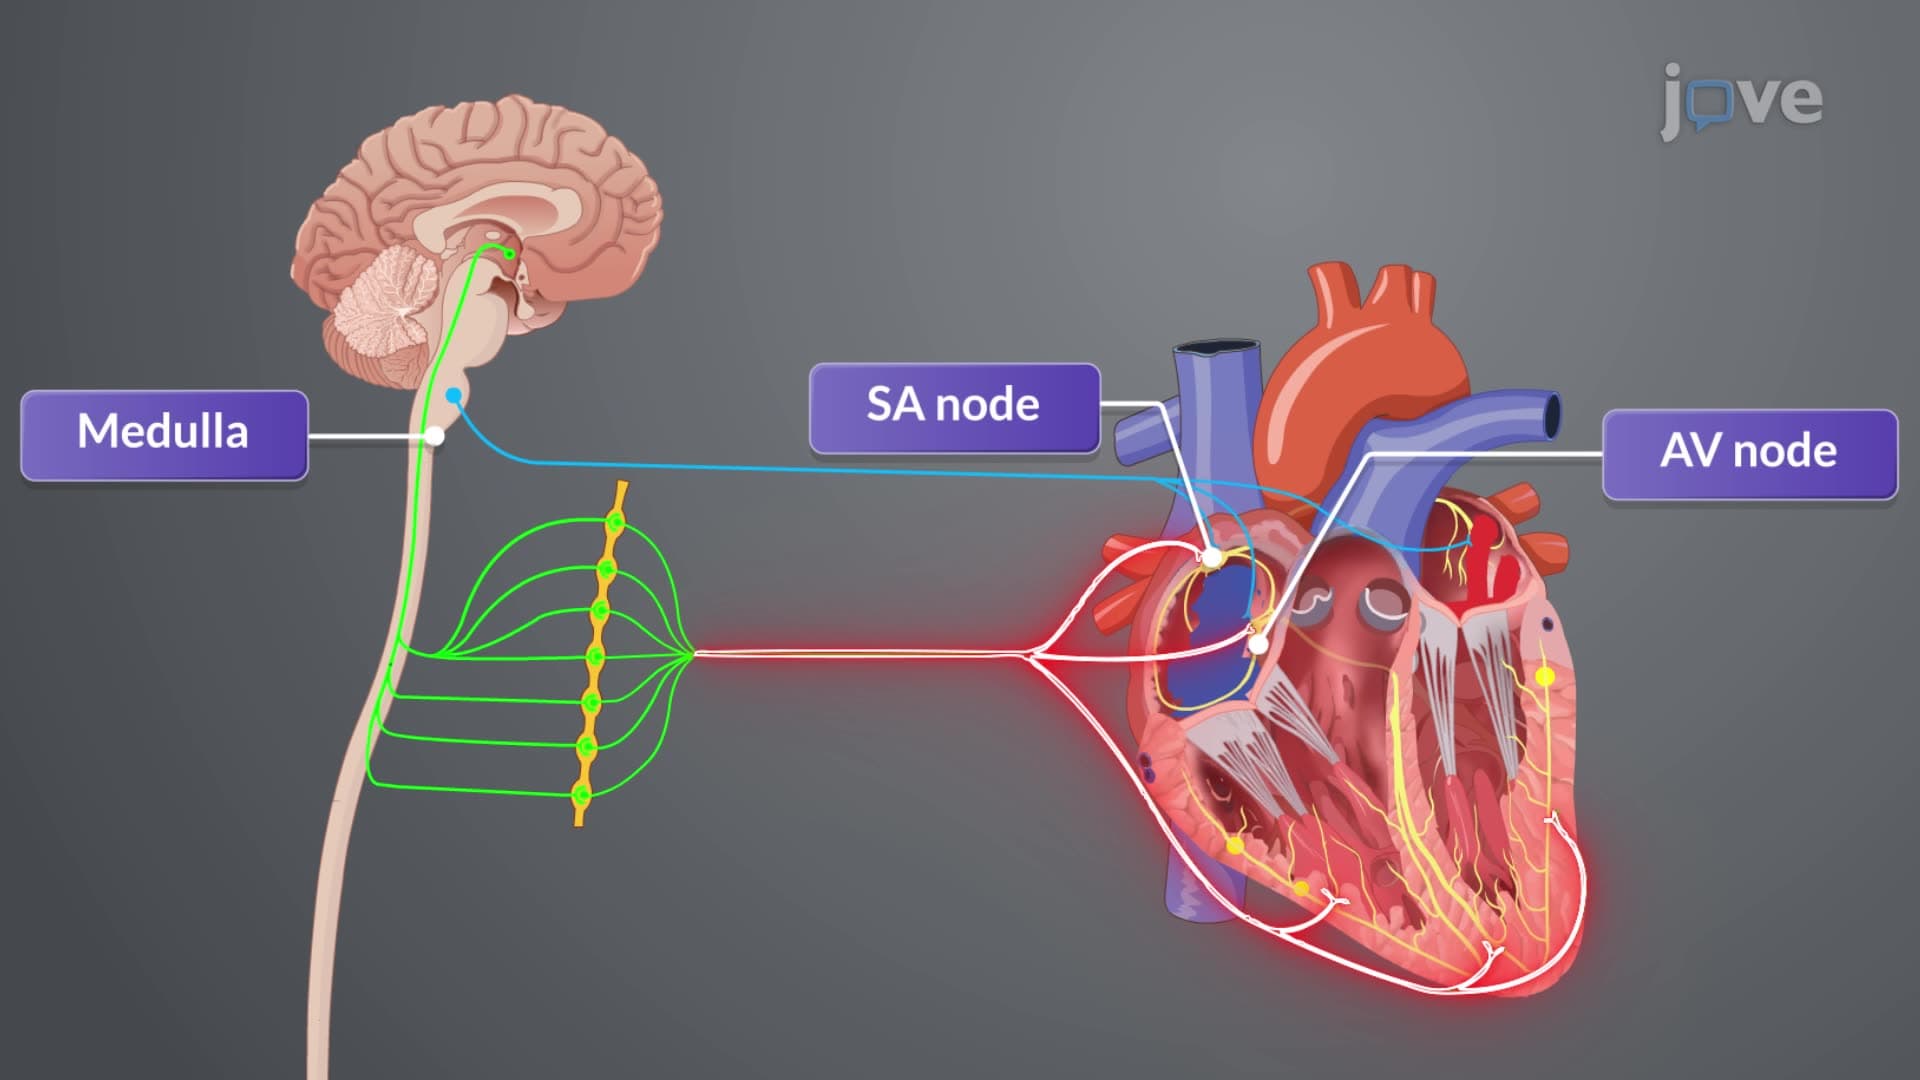
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:18
Hypertension and Regulation of Blood Pressure