Related Experiment Video
Updated: Aug 13, 2026
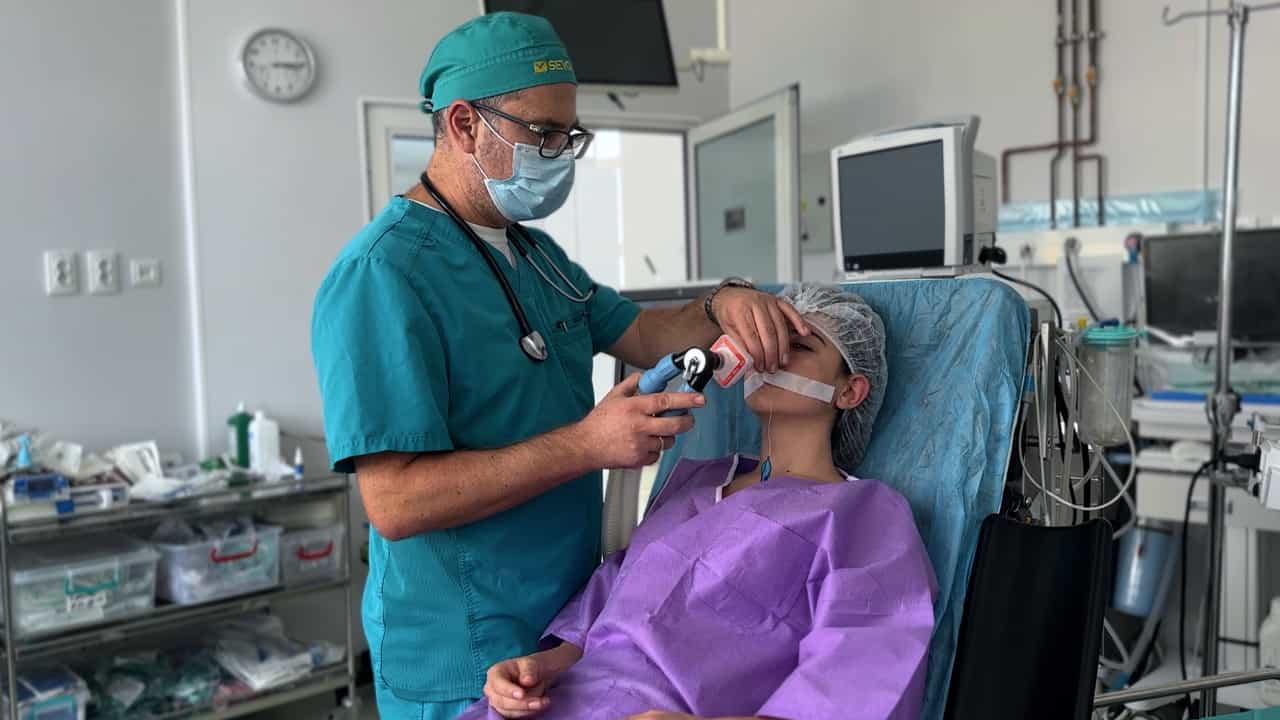

The Flexible Rhino-Laryngoscope for Awake Nasotracheal Intubation
Published on: August 2, 2024
Management of airway in patients with laryngeal tumors
Sreenivasa S Moorthy1, Sanjay Gupta, Brynte Laurent
1Department of Anesthesiology, Indiana University School of Medicine, Indianapolis, IN 46202, USA.

Study Objective:
To describe our systematic approach to securing the airway in patients with laryngeal tumors, developed over a 10-year period.
Design:
Retrospective analysis.
Setting:
University-affiliated veterans administration medical center.
Patients:
Eight hundred one patients presenting for laryngeal tumor surgery in a 10-year period, 285 of whom underwent tracheostomy (25 with local anesthesia and 260 with general anesthesia).
Interventions:
Preoperative examination, including history, physical examination, computed axial tomography and/or magnetic resonance imaging, and ear, nose, and throat surgeons' evaluation via indirect laryngoscopy or fiberoptic bronchoscopy were performed before the anesthesiologist's interventions. Local (topical) anesthesia and mild sedation were used for laryngeal evaluation with fiberoptic bronchoscopy. Tumor grade was then established, which determined how the airway would be secured: general anesthesia induction, receive topical anesthesia for awake, direct laryngoscopy, and tracheal intubation, or undergo tracheostomy with local anesthesia.
Measurements And Main Results:
When the airway was secured, surgeons performed the biopsy, (any) tumor debulking, laser excision, or tracheostomy to establish both the airway and the diagnosis. Pulmonary function, including flow-volume loops and blood gas analysis were also useful in evaluating the degree of obstruction and gas exchange. In the event of respiratory distress, tracheostomy was performed after tracheal intubation or with local anesthesia, followed by direct laryngoscopy and biopsy. Depending on the diagnosis, further surgery and radiation treatment were planned next.
Conclusions:
With these guidelines, we have reduced the frequency of emergencies because of a lost airway, bleeding, or dislodging of tumor.
Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:21
Larynx
Anatomy of the Larynx
The larynx consists of various components, including cartilage, muscles, and vocal cords. Its structure includes three large unpaired cartilages—the thyroid, cricoid, and epiglottis—and three smaller paired cartilages—the arytenoids, corniculates, and...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...