Related Experiment Video
Updated: Aug 13, 2026
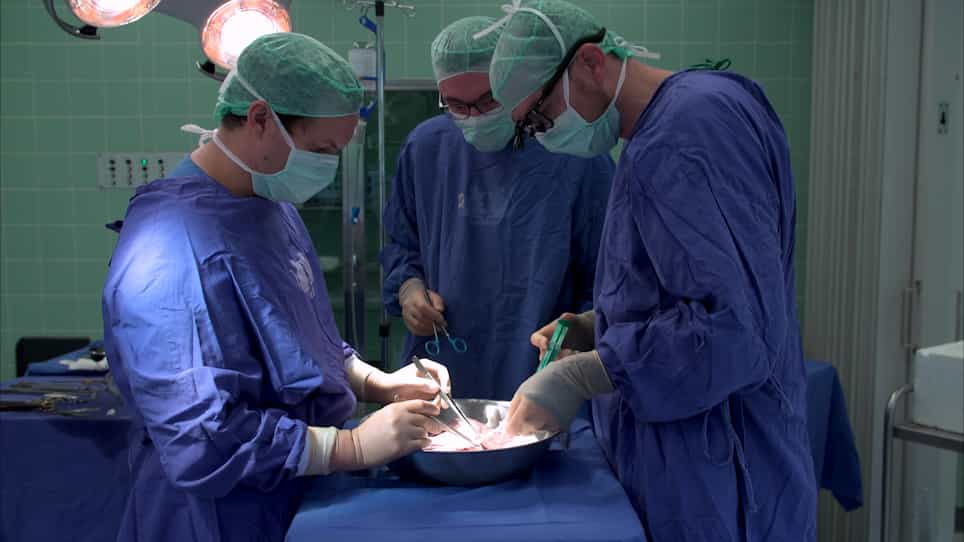

Porcine Liver Transplantation Without Veno-Venous Bypass As an Extended Criteria Donor Model
Published on: August 17, 2022
Ischemic preconditioning for major liver resection under vascular exclusion of the liver preserving the caval flow: a
Daniel Azoulay1, Valério Lucidi, Paola Andreani
1Centre Hépato-Biliare, Hôpital Paul Brousse, Villejuif, Université Paris-Sud, and IFR 89.9, Paris, France.

Background:
Two randomized prospective studies suggested that ischemic preconditioning (IP) protects the human liver against ischemia-reperfusion injury after hepatectomy performed under continuous clamping of the portal triad. The primary goal of this study was to determine whether IP protects the human liver against ischemia-reperfusion injury after hepatectomy under continuous vascular exclusion with preservation of the caval flow.
Study Design:
Sixty patients were randomly divided into two groups: with (n=30; preconditioning group) and without (n=30; control group) IP (10 minutes of portal triad clamping and 10 minutes of reperfusion) before major hepatectomy under vascular exclusion of the liver preserving the caval flow. Serum concentrations of aspartate transferase, alanine transferase, glutathione-S-transferase, and bilirubin and prothrombin time were regularly determined until discharge and at 1 month. Morbidity and mortality were determined in both groups.
Results:
Peak postoperative concentrations of aspartate transferase were similar in the groups with and without IP (851 +/- 1,733 IU/L and 427 +/- 166 IU/L respectively, p=0.2). A similar trend toward a higher peak concentration of alanine transferase and glutathione-S-transferase was indeed observed in the preconditioning group compared with the control group. Morbidity and mortality rates and lengths of ICU and hospitalization stays were similar in both groups.
Conclusions:
IP does not improve liver tolerance to ischemia-reperfusion after hepatectomy under vascular exclusion of the liver with preservation of the caval flow. This maneuver does not improve postoperative liver function and does not affect morbidity or mortality rates. The clinical use of IP through 10 minutes of warm ischemia in this technique of hepatectomy is not currently recommended.
