Related Experiment Video
Updated: Aug 13, 2026


Amikacin Protection Assay for Quantification and Visualization of Escherichia coli Cell Invasion
Published on: July 3, 2026
Dopamine is not an independent risk factor for reduced amikacin clearance in extremely low-birth-weight infants
Karel Allegaert1, Anne Debeer, Veerle Cossey
1Neonatal Intensive Care Unit, University Hospital, Gasthuisberg Leuven, Belgium.

Insights
Dopamine levels do not independently affect amikacin clearance in preterm infants. Gestational age and nonselective cyclo-oxygenase (COX) inhibitor use are key factors influencing amikacin clearance, not dopamine itself.
Area of Science:
- Neonatal pharmacology
- Pediatric pharmacokinetics
- Antibiotic dosing optimization
Background:
- Significant variability exists in amikacin clearance among preterm infants.
- Factors like gestational age, birth weight, and COX inhibitor use partially explain this variability.
- The independent effect of dopamine on amikacin clearance required further investigation.
Purpose of the Study:
- To evaluate the effect of dopamine on amikacin clearance in preterm infants.
- To determine if dopamine is an independent predictor of altered amikacin clearance.
- To inform amikacin dosing strategies in neonates.
Main Methods:
- Retrospective analysis of clinical data and amikacin pharmacokinetics in preterm infants (<31 weeks GA).
- Pharmacokinetics calculated using a one-compartment model with paired samples for therapeutic drug monitoring.
- Monovariate and logistic regression analyses used to assess the impact of clinical factors on amikacin clearance.
Main Results:
- Gestational age, birth weight, COX inhibitor, and dopamine significantly affected amikacin clearance in univariate analysis.
- In logistic regression, dopamine was not an independent predictor when gestational age, birth weight, or COX inhibitor use were included.
- Amikacin clearance was 0.46 mL/kg/min (range, 0.09-2.33) and distribution volume was 0.54 L/kg (range, 0.17-2.31) in 240 neonates.
Conclusions:
- Dopamine is an indicator, not an independent marker, of reduced amikacin clearance in extremely low-birth-weight infants.
- Amikacin dosage or interval adjustments are not necessary when dopamine is prescribed if gestational age and COX inhibitor use are considered.
- Gestational age and nonselective COX inhibitor coadministration are the primary determinants of amikacin clearance in this population.
Introduction:
Important inter-individual variability in amikacin clearance was observed in preterm infants, only in part explained by gestational age (GA), birth weight, or coadministration of nonselective cyclo-oxygenase (COX) inhibitor. We therefore evaluated whether dopamine had an additional effect on amikacin clearance.
Methods:
Clinical characteristics (GA, weight, COX inhibitor, dopamine, prenatal betamethasone) and amikacin pharmacokinetics were retrospectively collected in a cohort of preterm infants (GA of <31 wks, early neonatal life on respiratory support, between January 1, 1999 and January 6, 2005). Pharmacokinetics were calculated by assuming a one-compartment model with instantaneous input and first-order output based on paired samples collected for therapeutic drug monitoring before and following second administration. Monovariate analysis (Spearman, Mann-Whitney U test) was used to study the impact of clinical characteristics on amikacin clearance, and logistic regression was used to assess their potential independent effect.
Results:
Paired amikacin samples were available for 240 neonates (mean GA, 28 wks; birth weight, 1042 g). Amikacin clearance was 0.46 (range, 0.09-2.33) mL/kg/min and distribution volume was 0.54 (range, 0.17-2.31) L/kg. GA, birth weight, COX inhibitor, and dopamine had a significant effect on amikacin clearance. In a logistic regression model, dopamine was no longer a significant variable when GA, birth weight, or cotreatment of a nonselective COX inhibitor was entered as second variable.
Conclusions:
Dopamine is an indicator but not an independent marker of reduced amikacin clearance in early neonatal life in extremely low-birth-weight infants. Therefore, neither dose nor interval should be adapted when dopamine is prescribed, if GA and coadministration of nonselective COX inhibitors already have been taken into account.

Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:21
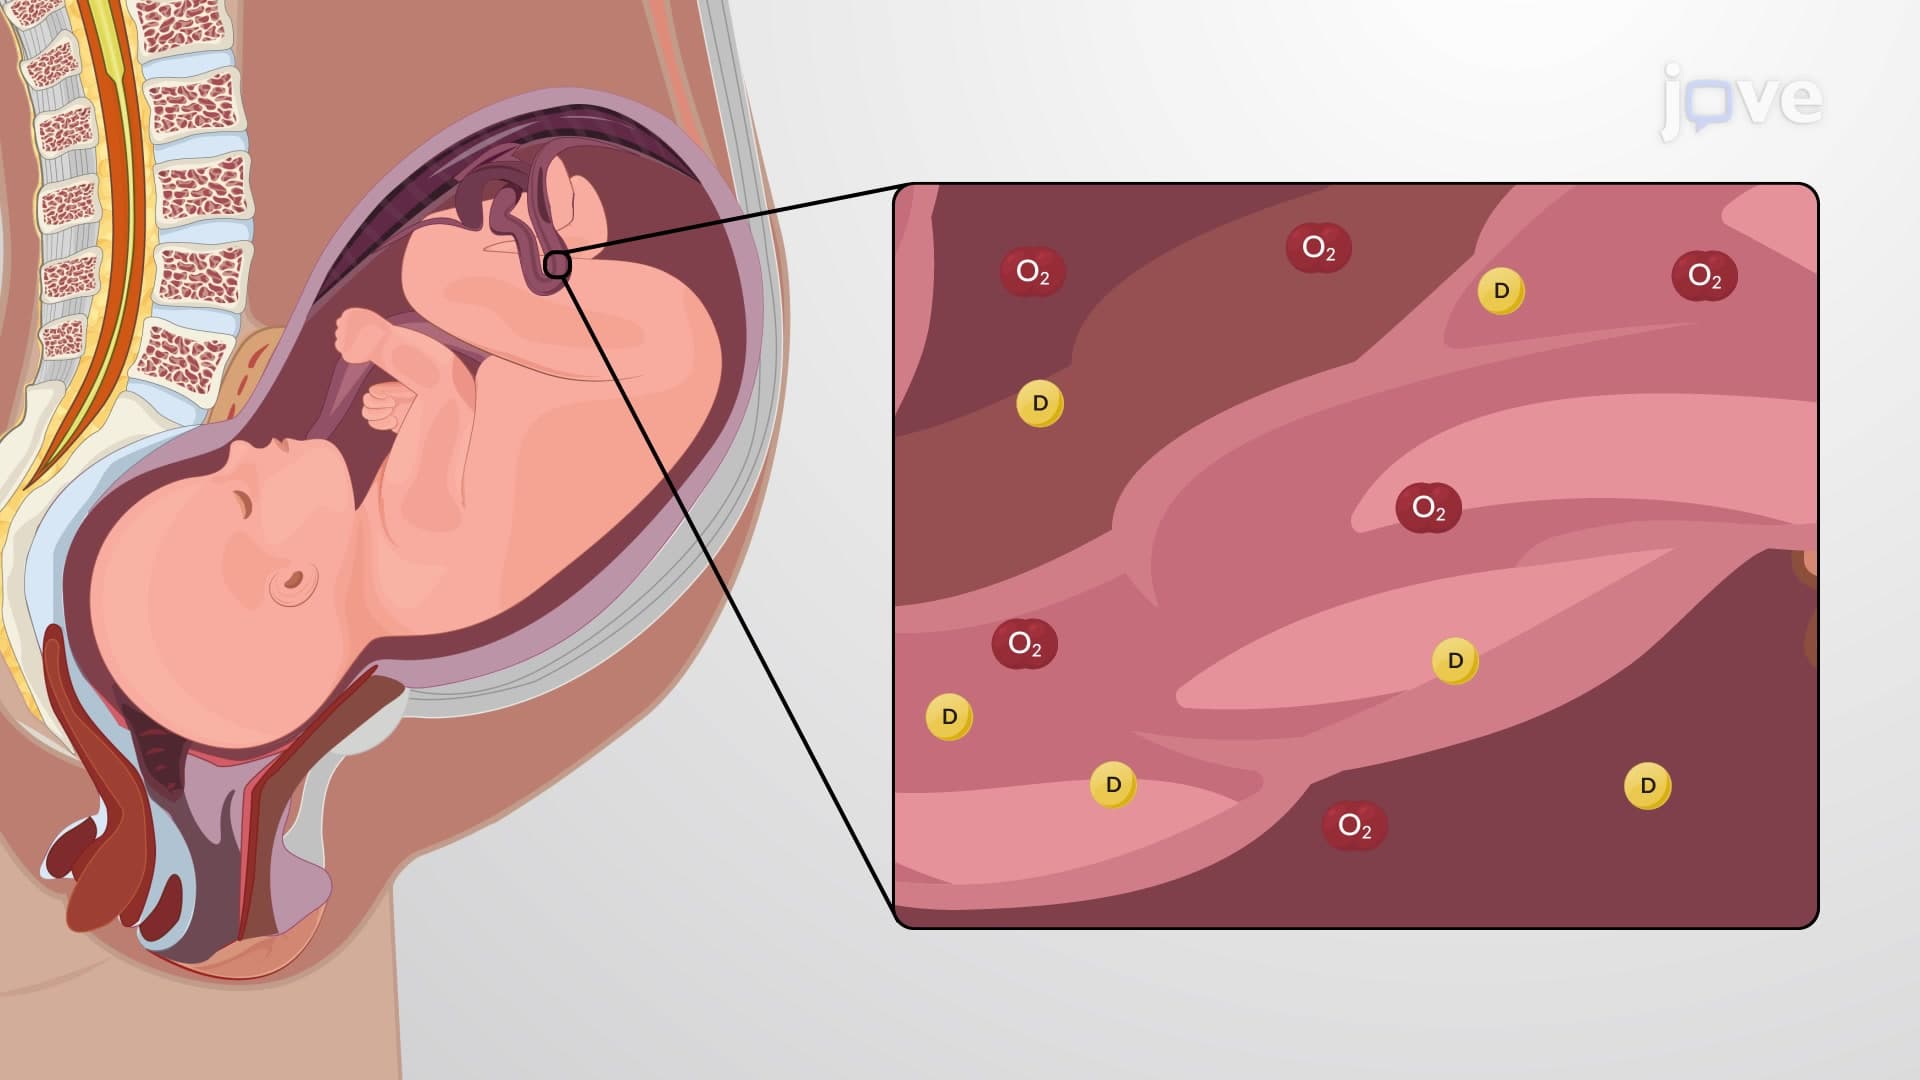
Factors Affecting Drug Response: Overview
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:29
Drug Dosing: Infants and Children