Related Experiment Video
Updated: Aug 11, 2026
Lentiviral-mediated Knockdown During Ex Vivo Erythropoiesis of Human Hematopoietic Stem Cells
Published on: July 16, 2011
Erythropoietin dose requirements when converting from subcutaneous to intravenous administration among patients on
Louise M Moist1, Norm Muirhead, Lori D Wazny
1University of Western Ontario, London Health Sciences Centre--Victoria Hospital, London, Ontario, Canada. louise.moist@lhsc.on.ca

Background:
The optimal route for administration of exogenous erythropoietin remains controversial, particularly after the increased incidence in pure red cell aplasia. In Canada, the majority of hemodialysis units have converted to the intravenous route for administration of erythropoietin to potentially decrease the risk of pure red cell aplasia.
Objective:
To compare the difference in the weight-adjusted, weekly erythropoietin dose (units/kg/wk) administered by the subcutaneous compared with the intravenous route in a chronic hemodialysis population followed for 12 months.
Methods:
This prospective cohort study recruited patients receiving subcutaneous erythropoietin for at least 3 months while undergoing dialysis in a tertiary care hemodialysis program. Participants were switched to intravenous erythropoietin, and the average weekly dose was recorded at 1, 2, 3, 6, and 12 months. Anemia management and hemoglobin, iron, and delivered dialysis dose targets remained constant throughout the study.
Results:
The erythropoietin dose increased by 24.5 units/kg/wk (95% CI 12.7 to 36.3; p < 0.001), representing a 20.2% increase (95% CI 10.5% to 29.9%; p < 0.001) 12 months after conversion from the subcutaneous to intravenous route of administration. Both patients with and without residual renal function at baseline required a significant increase in the intravenous dose.
Conclusions:
A 20.2% increase in erythropoietin dose was required to maintain hemoglobin targets between 11 and 12 g/dL after conversion from a subcutaneous to intravenous formulation. Healthcare funding agencies need to reexamine the cost benefit of using intravenous erythropoietin in the hemodialysis population with a low incidence of pure red cell aplasia.
More Related Videos

Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:28
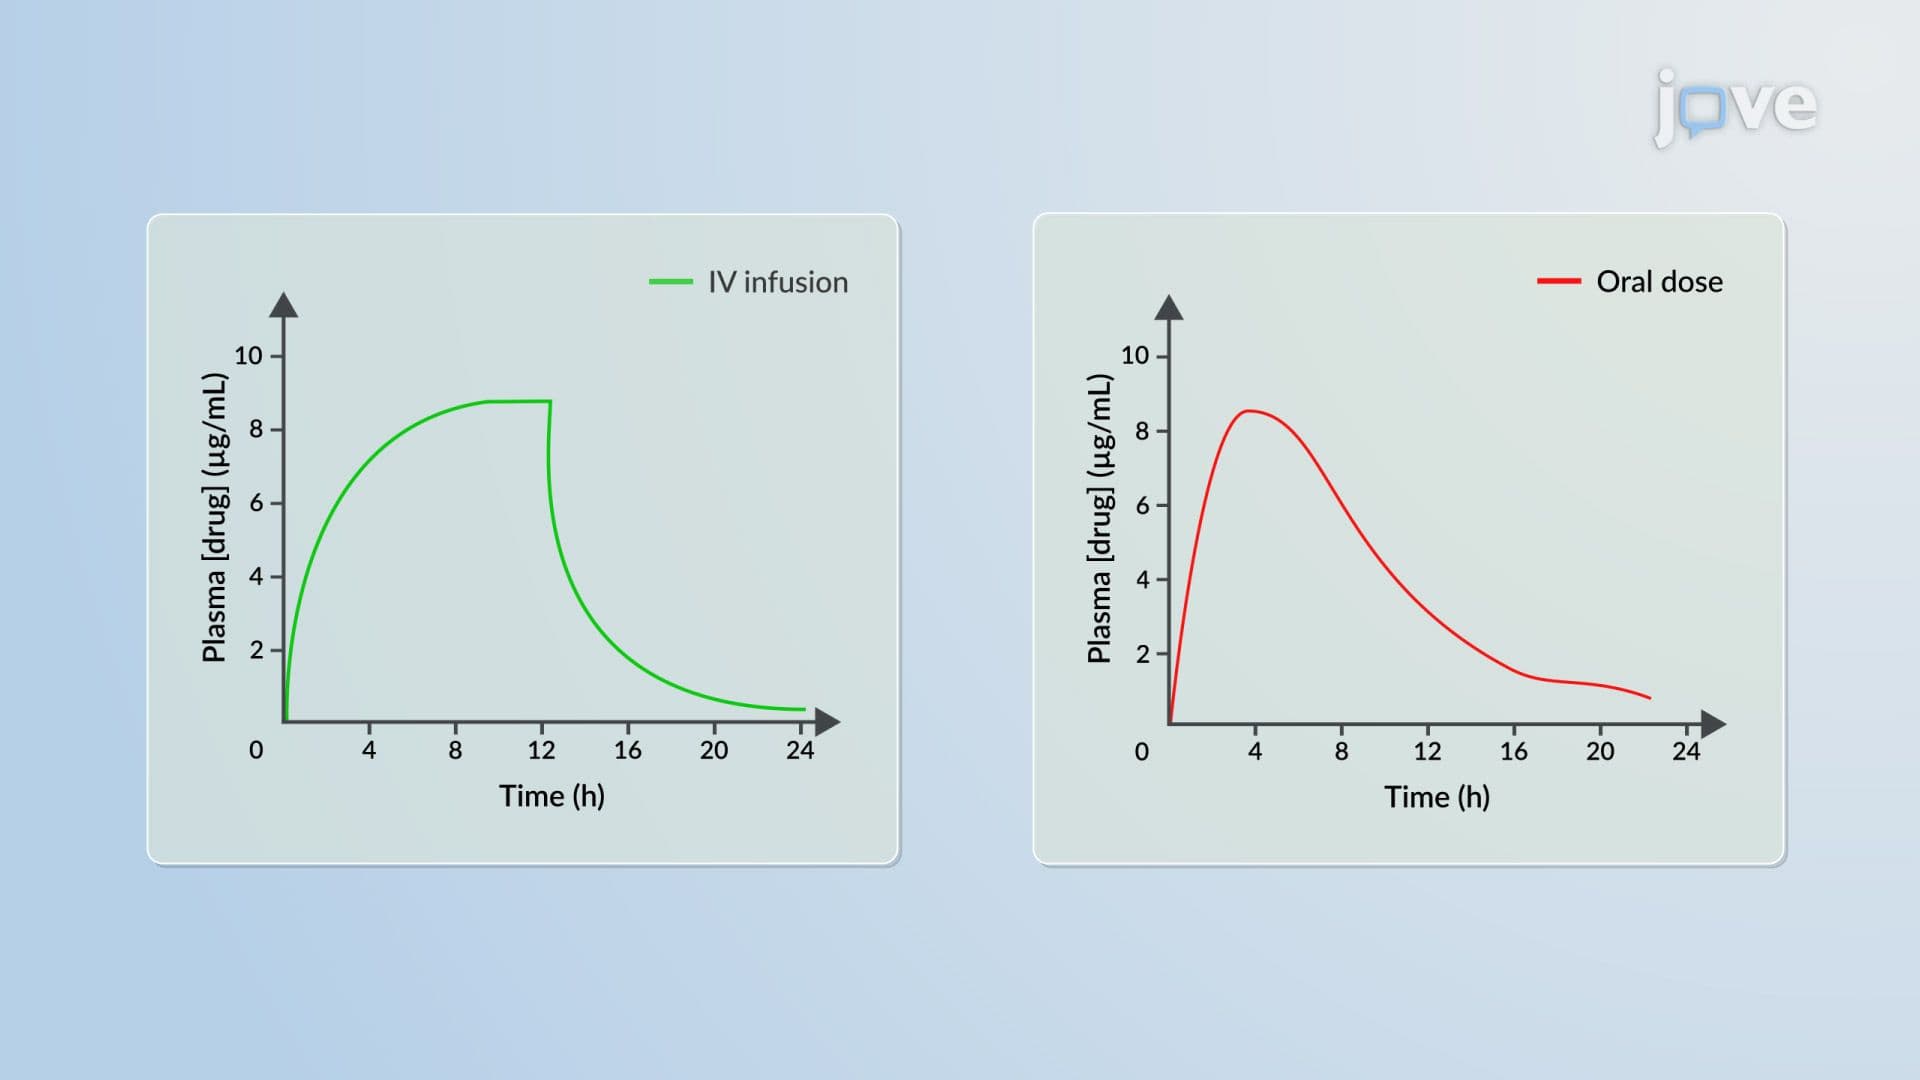
IV Infusion to Oral Dosing: Conversion Methods
 01:25
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:25
Hemodialysis III: Nursing Management