Related Experiment Video
Updated: Aug 11, 2026

A Semi-Automated and Reproducible Biological-Based Method to Quantify Calcium Deposition In Vitro
Published on: June 2, 2022
Association between phosphate removal and markers of bone turnover in haemodialysis patients
Marta Albalate1, Concepción de la Piedra, Cristina Fernández
1Fundación Renal Iñigo Alvarez de Toledo, Instituto Reina Sofía de Investigación Nefrológica, Universidad Autónoma, Madrid, Spain.

Background:
As the main mineral reservoir, bone acts as a calcium (Ca) and phosphate buffering system. Accordingly, phosphate removal by haemodialysis (HD) might be theoretically influenced by bone turnover, as well as by the interaction of regulatory molecules, such as PTH and osteoprotegerin (OPG). The present study investigated the relationship between these variables and phosphate removal by HD.
Methods:
Blood samples for serum Ca, phosphate, bicarbonate, intact PTH, PTH (1-84), bone alkaline phosphatase, tartrate-resistant acid phosphatase 5b, OPG and receptor activator of nuclear factor-kappaB ligand (RANKL) were obtained in 28 HD patients. Phosphate removal was measured by a continuous collection of the dialysate.
Results:
Pre-dialysis serum phosphate concentration is the critical factor in determining dialytic phosphate removal. However, multiple regression analysis reveals that phosphate removal is better explained by a combination of factors than by phosphate concentration alone. In this model, the PTH/OPG ratio is an additional positive factor, whereas age and vitamin D treatment are negative factors. Patients with pre-HD bicarbonate higher than 20 mEq/l had higher serum phosphate and, accordingly, higher phosphate removal; of interest, these individuals also have significant differences in RANKL/OPG. Mean (SD) OPG levels were significantly higher than that in the healthy population (16.2 (12.5) pmol/l; these values correlated with age (r = 0.4, P<0.04). Mean serum RANKL (1.03 (1.02) pmol/l) was within the range of normal individuals.
Conclusions:
Dialytic phosphate removal has a crucial, direct relationship with pre-HD plasma phosphate levels. However, the phenomenon of phosphate removal is more precisely explained using a more complex relationship, defined by the interaction between serum phosphate, PTH/OPG, age and vitamin D administration. Serum RANKL levels are first reported in HD patients, and are not different from the normal population.
More Related Videos
Related Concept Videos
 01:31
Osteoclasts in Bone Remodeling
 01:40
Bone Remodeling
 01:27
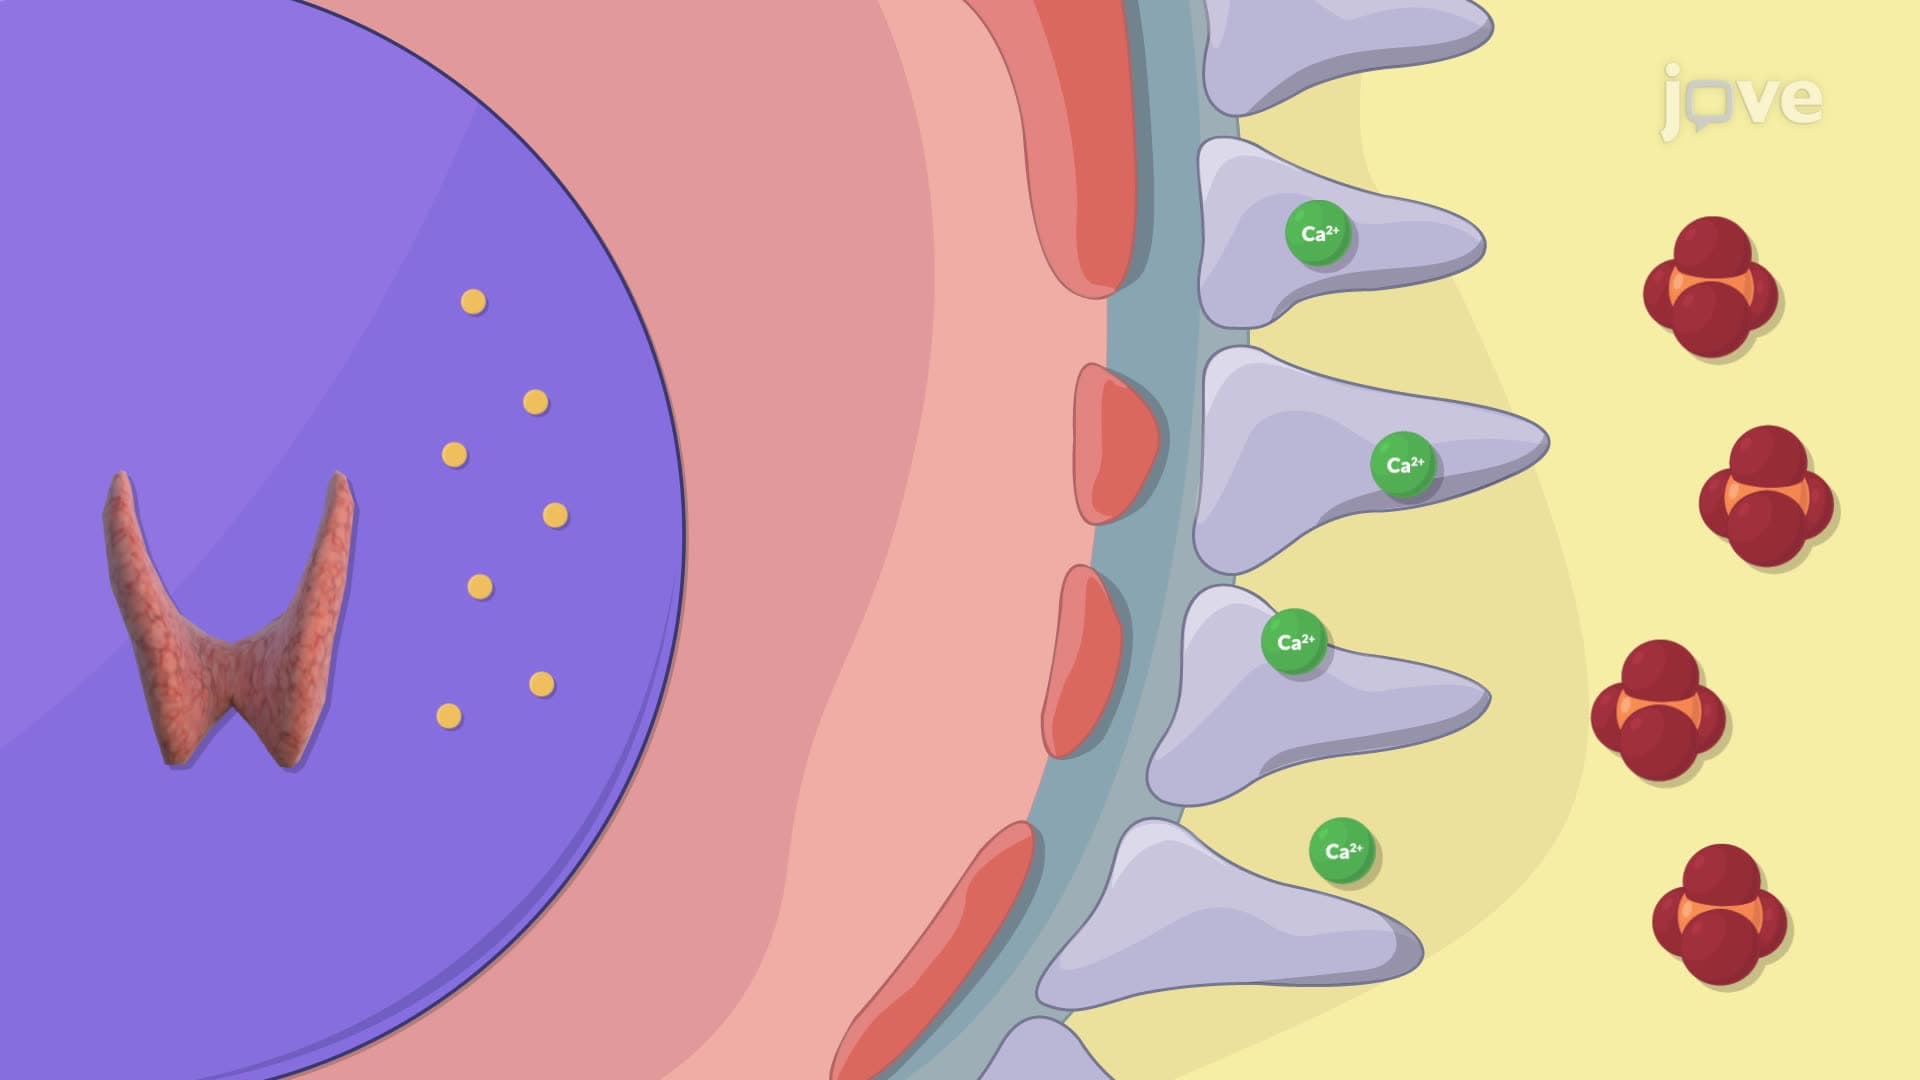
Roles of Electrolytes: Calcium and Phosphate
The calcium concentration in blood plasma is primarily regulated...
 01:02
What is the Skeletal System?
 01:31
Essential Minerals for Bone Health
Calcium and Phosphorus
Calcium is a critical component of bones, especially in the form of calcium phosphate and calcium carbonate. Since the body cannot make calcium, it must be obtained from the diet. However, calcium cannot be absorbed from the small intestine without...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...