Related Experiment Videos
PDE5 inhibitors: are there differences?
1Division of Urology, University of North Carolina, Chapel Hill, North Carolina 27759-7235, USA.

Abstract:
The introduction of oral agents for the treatment of erectile dysfunction (ED) has revolutionized the treatment of men with erection problems of all severities and etiologies. Sildenafil, available on the world market since 1998 was joined in 2003 by tadalafil and vardenafil as effective save and reliable oral agents. While these agents share the method of action in common and are all contraindicated with nitrate medications, these are differences among the three agents. Sildenafil has the longest patient experience and the most robust data confirming its activity, safety and tolerability. It has recently been released for use in pulmonary hypertension as well as ED. Vardenafil, the most biochemically potent of the molecules has also been demonstrated to be effective in men with severe ED and in some patients failing sildenafil. Tadalafil is unique in its longer half life and is also tolerable, safe and effective in all severities and etiologies of ED. Tadalafil is also unique in its inhibition of PDE 11, a characteristic of unknown but probably negligible importance. Newer data have also suggested that these agents may be helpful in the treatment of lower urinary tract symptoms. Since the introduction of sildenafil in 1998, erectile dysfunction has been effectively treated with oral medications. The recent addition of vardenafil and tadalafil to the market has increased the number of phosphodiesterase type 5 inhibitors (PDE5) to three agents used throughout the world. Each of these agents has similar mechanism of action, but has distinct differences. All three drugs in this class have similar pharmacokinetic and pharmacodynamic profiles and each is effective for patients with ED of all ages, severities and etiologies. While there are clear pharmacokinetic and pharmacodynamic differences amongst these agents, clinical differences are somewhat more difficult to identify. Indeed the data of preference trials, head to head clinical trials, and selection trials are few. The differences in pharmacokinetics while having distinct advantages in marketing each drug may be difficult for clinicians and patients to identify. With the lack of data and well done clinical trials, it is difficult for the clinician to differentiate amongst the three agents and to select a PDE5 inhibitor for a specific ED patient or a specific agent to switch to if an initial PDE5 agent is unsuccessful or poorly tolerated. This discussion summarizes some of the current data on PDE5 inhibitors and their efficacy, safety, and use in other conditions.
Related Concept Videos
 01:28
Treatment for Pulmonary Arterial Hypertension: Phosphodiesterase Inhibitors
Among the PDE5 inhibitors, sildenafil (Revatio) stands out as a competitive and selective inhibitor. It operates by elevating cellular levels of cGMP and augmenting signaling through the cGMP-PKG pathway, promoting vasodilation. Upon oral...
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...
 01:23
Dipeptidyl Peptidase 4 Inhibitors
 01:23
Antihypertensive Drugs: Vasodilators
 01:31
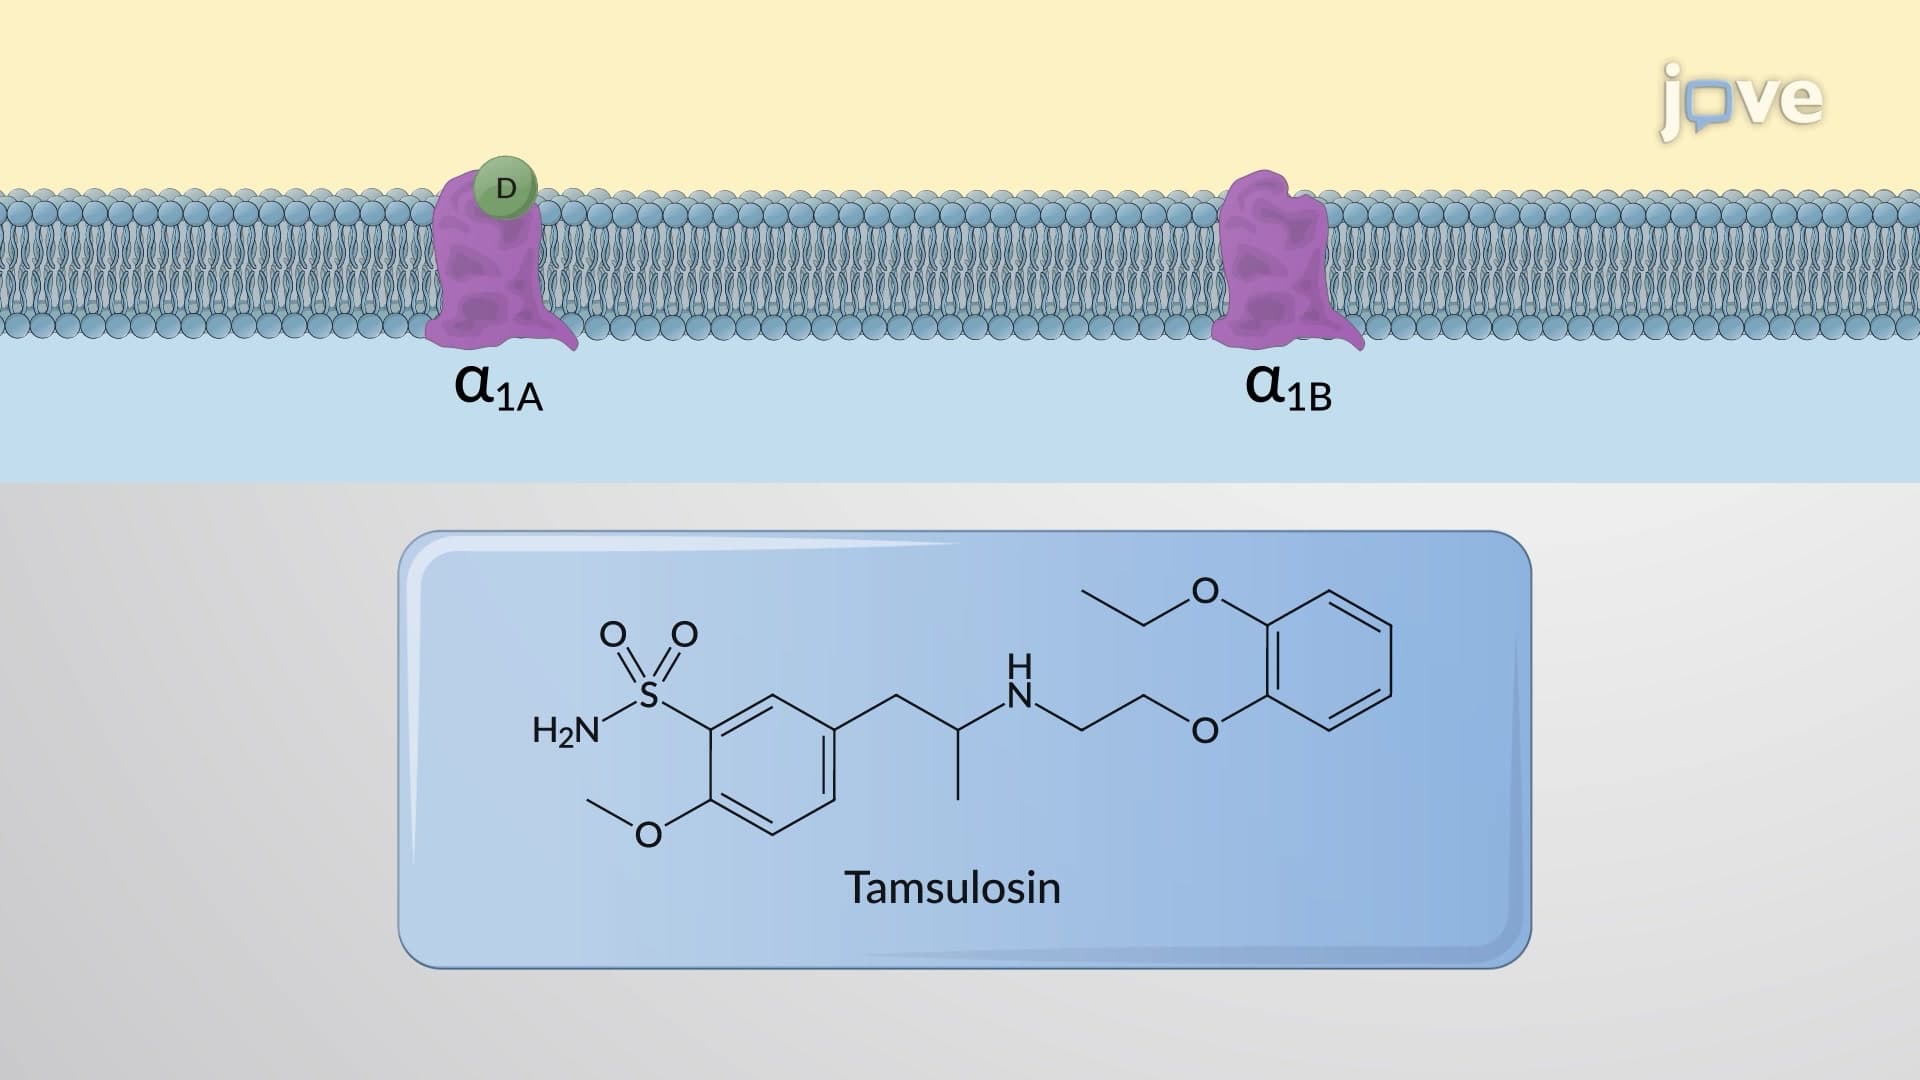
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...