Related Experiment Video
Updated: Aug 9, 2026
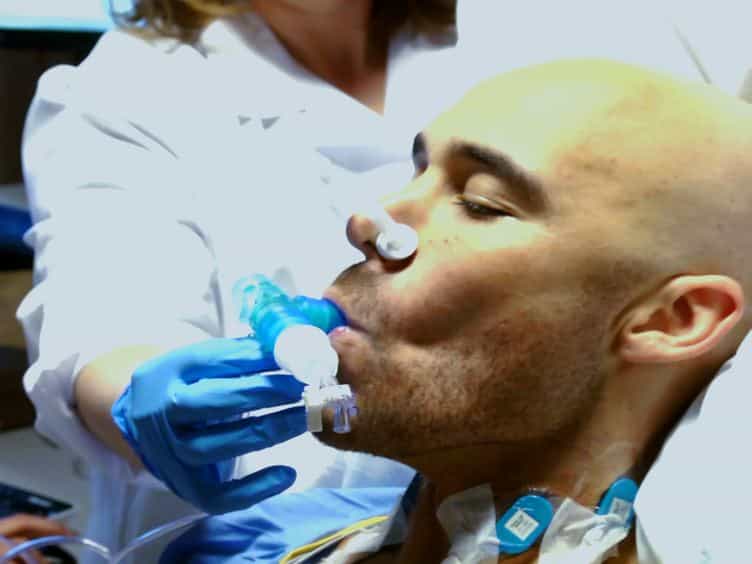

Evaluation of Respiratory Muscle Activation Using Respiratory Motor Control Assessment (RMCA) in Individuals with Chronic Spinal Cord Injury
Published on: July 19, 2013
[Neuromuscular disorders - assessment of the respiratory muscles]
1Service d'Explorations Fonctionnelles Respiratoires et Clinique des Maladies Respiratoires Hôpital Calmette, CHRU de Lille, Lille. tperez@chru-lille.fr

Abstract:
Involvement of respiratory muscles is a nearly constant feature of neuromuscular disorders, leading to respiratory failure. A careful respiratory follow up adapted to the variable time course of each disease is therefore mandatory. As the first step, a systematic clinical evaluation is essential to detect the subtle respiratory symptoms and signs related to respiratory muscle failure. Dyspnea and orthopnea are often late findings in patients with a usually severe functional impairment due to peripheral muscle weakness. Nocturnal respiratory events (obstructive sleep apnea syndrome and hypoventilation) are strongly suggested by daytime hypersomnolence and frequent morning headaches. Physical evaluation is essential to detect accessory muscle recruitment, supine abdominal paradox, and encumbrance of upper or lower airways. Vital capacity (VC) is the most classical lung function test. The major limitation of spirometry is its poor sensitivity to detect a moderate inspiratory muscle weakness. Supine VC may improve the detection of diaphragmatic involvement. Peak expiratory flow during cough (cough PEF) gives an overall evaluation of cough efficiency, values below 160 to 270 L/min suggesting poor airway clearance. Arterial blood gases are performed in case of clinical signs, significant deterioration of lung function tests, or sleep desaturations. Hypercapnia is weakly related to lung function results in patients with Steinert dystrophy and those with bulbar involvement. A specific evaluation of respiratory muscle strength is mandatory, as these tests are both sensitive and highly prognostic. Possible discrepancies (particularly in bulbar patients) between maximal inspiratory pressure (PImax) and sniff nasal inspiratory pressure (SNIP) justify to perform both measurements and to select the highest pressure. A maximal expiratory pressure (PEmax) below 45 cm H2O may indicate a compromised cough efficiency but the correlation with cough PEF may be poor. A screening nocturnal oxymetry is useful to detect sleep apneas and hypoventilation. Criteria defining significant desaturations remain however controversial. Suspicion of obstructive sleep apnea syndrome on clinical grounds or oxymetry findings should be confirmed by a conventional polysomnography.
Related Concept Videos
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...
 01:24
Physical Assessment of the Respiratory Tract II: Palpation
Thoracic Palpation
Thoracic palpation detects tenderness, masses, lesions, respiratory excursions, and vocal fremitus. The nurse assesses...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:15
Myasthenia Gravis: Diagnostic Tests
The edrophonium test is a diagnostic tool for myasthenia gravis. It involves...