Related Experiment Video
Updated: Aug 9, 2026
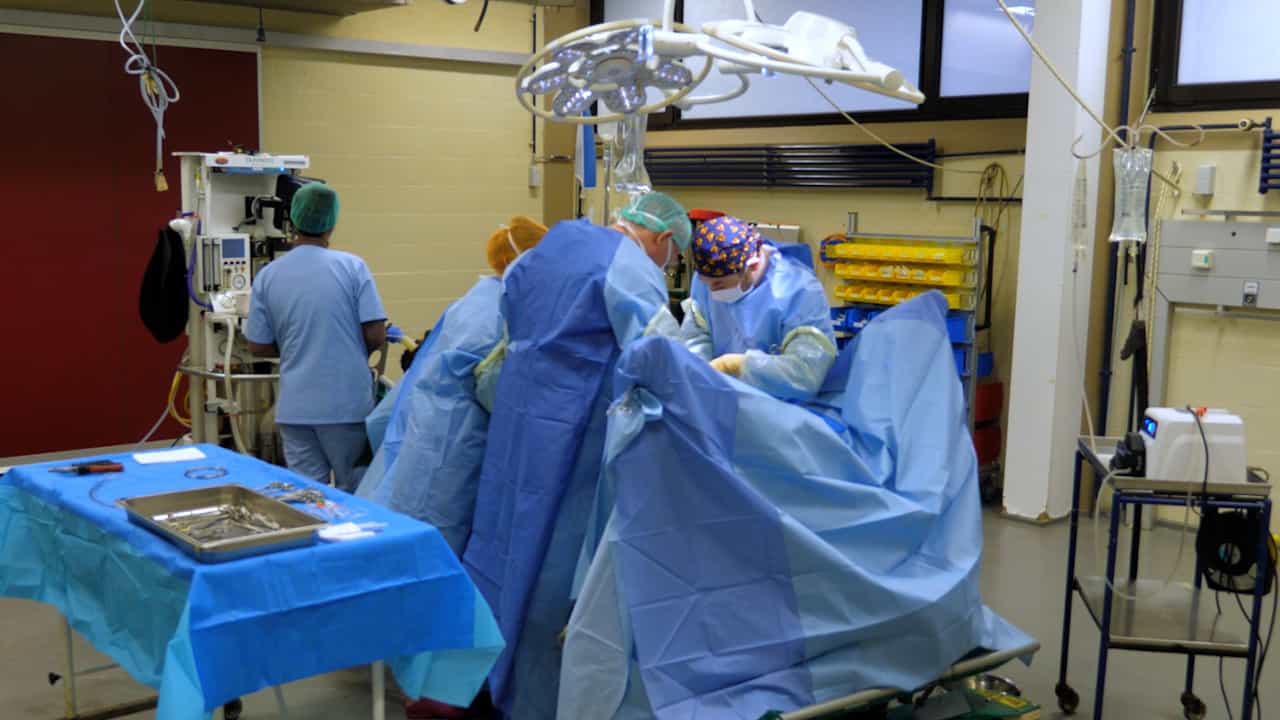

Surgical Closure of Equine Abdomen, Prevention, and Management of Incisional Complications
Published on: May 10, 2024
Frequency and risk factors for wound dehiscence/burst abdomen in midline laparotomies
S H Waqar1, Zafar Iqbal Malik, Asma Razzaq
1Department of General Surgery, Pakistan Institute of Medical Sciences, Islamabad. drshwaqar@hotmail.com

Background:
Wound dehiscence/burst abdomen is a very serious postoperative complication associated with high morbidity and mortality. It has significant impact on health care cost, both for the patients and hospitals. The aim of the study was to determine the frequency of wound dehiscence/burst abdomen in patients undergoing emergency and elective laparotomies through midline incisions and to identify the risk factors for wound dehiscence.
Methods:
This study was carried out at department of General Surgery, Pakistan Institute of Medical Sciences, Islamabad from 1st January 2002 to 31st December 2002. 117 consecutive patients undergoing laparotomy with midline incision were included. They were followed by wound examination from third postoperative day onwards to see their normal or otherwise healing.
Results:
Seven out of 117 (5.9%) patients developed wound dehiscence. Five of them (4.2%) were operated in emergency and two (1.7%) were operated on elective list.
Conclusion:
It is very clear from our study that frequency of wound dehiscence/burst abdomen is still very high in our hospital. Peritonitis, wound infection and failure to close the abdominal wall properly are most important causes of wound dehiscence. Malnourishment and malignant obstructive jaundice predispose a patient to wound dehiscence by slowing the healing, and increasing rate of wound infection.

Related Concept Videos
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:07
Intestinal Obstruction II: Pathophysiology
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations: