Related Experiment Video
Updated: Aug 9, 2026
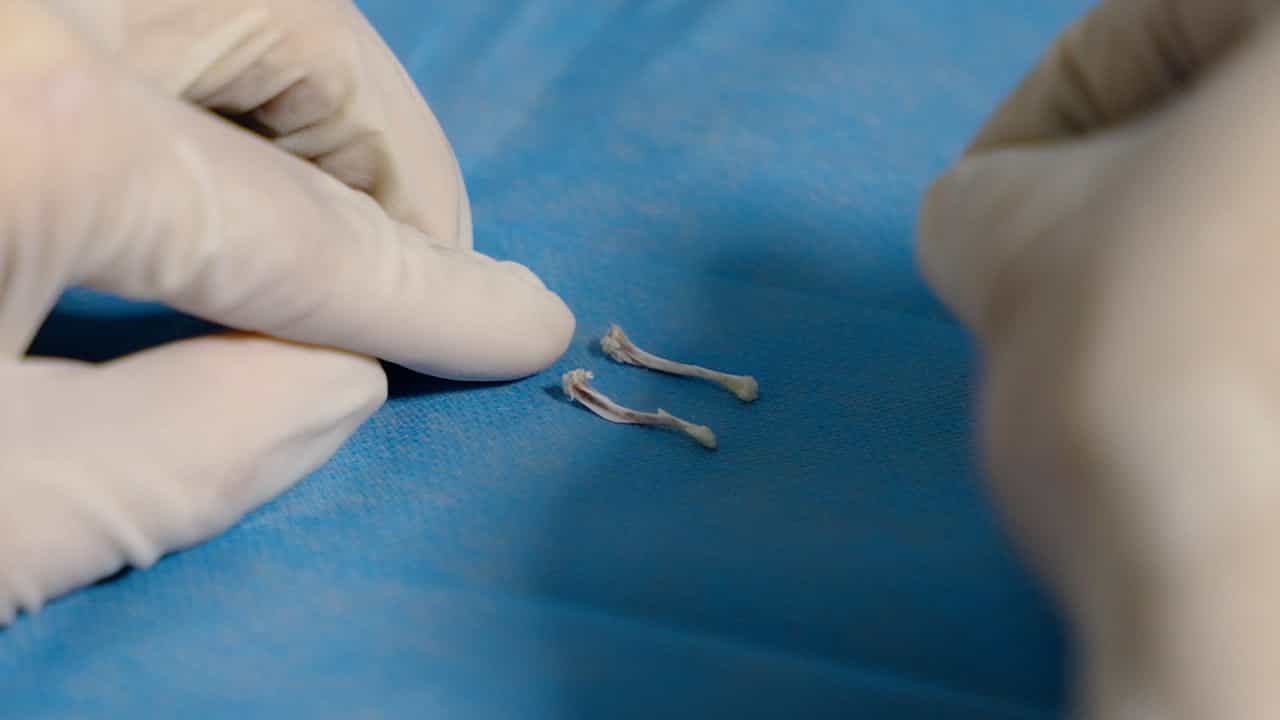

Trabecular Bone Microarchitecture Evaluation in an Osteoporosis Mouse Model
Published on: September 8, 2023
Osteoporosis in hemodialysis patients revisited by bone histomorphometry: a new insight into an old problem
F C Barreto1, D V Barreto, R M A Moyses
1Department of Internal Medicine, Division of Nephrology, Federal University of São Paulo, Brazil. fellype.barreto@terra.com.br

Osteoporosis in hemodialysis patients is associated with high morbidity and mortality and, although extensively studied by noninvasive methods, has never been assessed through bone biopsy. The aim of this study was to use histomorphometry to evaluate osteoporosis and identify factors related to its development in hemodialysis patients. We conducted a cross-sectional study involving 98 patients (35 women and 63 men; mean age: 48.4 +/- 13 years) on hemodialysis for 36.9 +/- 24.7 months. Patients were submitted to transiliac bone biopsy with double tetracycline labeling. The bone metabolism factors ionized calcium, phosphorus, bone alkaline phosphatase, deoxypyridinoline, intact parathyroid hormone, and 25(OH) vitamin D were evaluated, as were the bone remodeling cytokines osteoprotegerin (OPG), soluble receptor-activator of NF-kappabeta ligand (sRANKL) and tumor necrosis factor-alpha (TNF)alpha. Osteoporosis was defined as trabecular bone volume (BV/TV) greater than 1 s.d. below normal (men <17.4%; women <14.7%). Forty-five patients (46%) presented osteoporosis, which was correlated with white race. We found BV/TV to correlate with age, OPG/sRANKL ratio, TNFalpha levels, and length of amenorrhea. In multiple regression analysis adjusted for sex and age, length of amenorrhea, white race, and OPG/sRANKL ratio were independent determinants of BV/TV. Histomorphometric analysis demonstrated that osteoporotic patients presented normal eroded surface and low bone formation rate (BFR/BS). Osteoporosis is prevalent in hemodialysis patients. Low BFR/BS could be involved in its development, even when bone resorption is normal. Cytokines may also play a role as may traditional risk factors such as advanced age, hypogonadism, and white race.
Osteoporosis in hemodialysis patients is associated with high morbidity and mortality and, although extensively studied by noninvasive methods, has never been assessed through bone biopsy. The aim of this study was to use histomorphometry to evaluate osteoporosis and identify factors related to its development in hemodialysis patients. We conducted a cross-sectional study involving 98 patients (35 women and 63 men; mean age: 48.4 +/- 13 years) on hemodialysis for 36.9 +/- 24.7 months. Patients were submitted to transiliac bone biopsy with double tetracycline labeling. The bone metabolism factors ionized calcium, phosphorus, bone alkaline phosphatase, deoxypyridinoline, intact parathyroid hormone, and 25(OH) vitamin D were evaluated, as were the bone remodeling cytokines osteoprotegerin (OPG), soluble receptor-activator of NF-kappabeta ligand (sRANKL) and tumor necrosis factor-alpha (TNF)alpha. Osteoporosis was defined as trabecular bone volume (BV/TV) greater than 1 s.d. below normal (men <17.4%; women <14.7%). Forty-five patients (46%) presented osteoporosis, which was correlated with white race. We found BV/TV to correlate with age, OPG/sRANKL ratio, TNFalpha levels, and length of amenorrhea. In multiple regression analysis adjusted for sex and age, length of amenorrhea, white race, and OPG/sRANKL ratio were independent determinants of BV/TV. Histomorphometric analysis demonstrated that osteoporotic patients presented normal eroded surface and low bone formation rate (BFR/BS). Osteoporosis is prevalent in hemodialysis patients. Low BFR/BS could be involved in its development, even when bone resorption is normal. Cytokines may also play a role as may traditional risk factors such as advanced age, hypogonadism, and white race.

Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:40
Bone Remodeling
 01:31
Osteoclasts in Bone Remodeling
 01:21
Skeleton and Calcium Homeostasis
 01:02
What is the Skeletal System?
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...