Related Experiment Videos
Acute effects of PEEP on tidal volume and respiratory center output during synchronized ventilation in preterm
Ximena Alegría1, Nelson Claure, Yoshirou Wada
1Department of Pediatrics, Division of Newborn Medicine, University of Miami Miller School of Medicine, Miami, Florida 33101, USA.

Insights
Increasing positive end expiratory pressure (PEEP) in preterm infants on mechanical ventilation can negatively impact lung mechanics and tidal volume. Respiratory center output does not sufficiently compensate for these acute effects, especially at lower respiratory drives.
Area of Science:
- Neonatal physiology
- Respiratory mechanics
- Mechanical ventilation
Background:
- Positive end expiratory pressure (PEEP) is standard for maintaining lung volume in ventilated preterm infants.
- Acute increases in PEEP can alter lung mechanics and tidal volume.
- The impact of PEEP changes on respiratory center output (RCO) in this population is not well understood.
Purpose of the Study:
- To evaluate the acute effects of varying PEEP levels on tidal volume (V(T)), lung compliance (C(L)), and RCO.
- To assess these effects during synchronized intermittent mandatory ventilation (SIMV) in preterm infants with differing basal respiratory drives.
Main Methods:
- Preterm infants were studied under SIMV with PEEP levels of 2, 4, and 6 cm H(2)O.
- Peak inspiratory pressure (PIP) was adjusted to maintain constant airway pressure changes.
- Respiratory center output (RCO) was measured via diaphragmatic electrical activity, with inspired CO(2) adjusted to modulate respiratory drive.
Main Results:
- Higher PEEP levels significantly reduced lung compliance (C(L)), tidal volume (V(T)), and minute ventilation (V'(E)).
- Respiratory center output (RCO) did not show a significant change across PEEP levels.
- A trend towards increased RCO was observed at lower respiratory drives with higher PEEP.
Conclusions:
- Elevated PEEP levels can acutely impair lung mechanics and ventilation in preterm infants.
- The respiratory center output does not adequately compensate for these negative effects.
- Careful consideration of PEEP settings is necessary in this vulnerable population.
Background:
Positive end expiratory pressure (PEEP) is routinely used in mechanically ventilated preterm infants to maintain lung volume. An acute increase in PEEP can affect lung mechanics and tidal volume, but it is unknown if these effects elicit compensatory changes in respiratory center output.
Objectives:
To investigate the acute effects of changes in PEEP on tidal volume (V(T)), lung compliance (C(L)), and respiratory center output (RCO) during synchronized intermittent mandatory ventilation (SIMV) in preterm infants at different levels of basal respiratory drive.
Methods:
Preterm infants were studied during SIMV at three levels of PEEP (2, 4, and 6 cm H(2)O for 2-3 min each) and at two levels of inspired CO(2). Peak inspiratory pressure (PIP) was adjusted to maintain the same delta pressure at the airway. RCO was assessed by measuring total diaphragmatic electrical activity. The level of inspired CO(2) was adjusted by modifying the instrumental dead space.
Results:
Sixteen preterm infants GA: 25 +/- 2 weeks, BW: 786 +/- 242 g, age: 18 +/- 15 days, SIMV: rate 14 +/- 3 b/min, Ti: 0.35 +/- 0.01 s, PIP: 16 +/- 1 cm H(2)O, and FiO(2): 0.31 +/- 0.06 were studied. At both levels of inspired CO(2), C(L), V(T), and V'(E) from spontaneous and mechanical breaths decreased significantly with higher PEEP. RCO did not change, but at lower respiratory drive, there was a trend towards an increase in RCO with higher PEEP.
Conclusion:
Higher PEEP levels can have acute negative effects on lung mechanics and ventilation in preterm infants without a sufficient compensatory increase in RCO.
Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:29
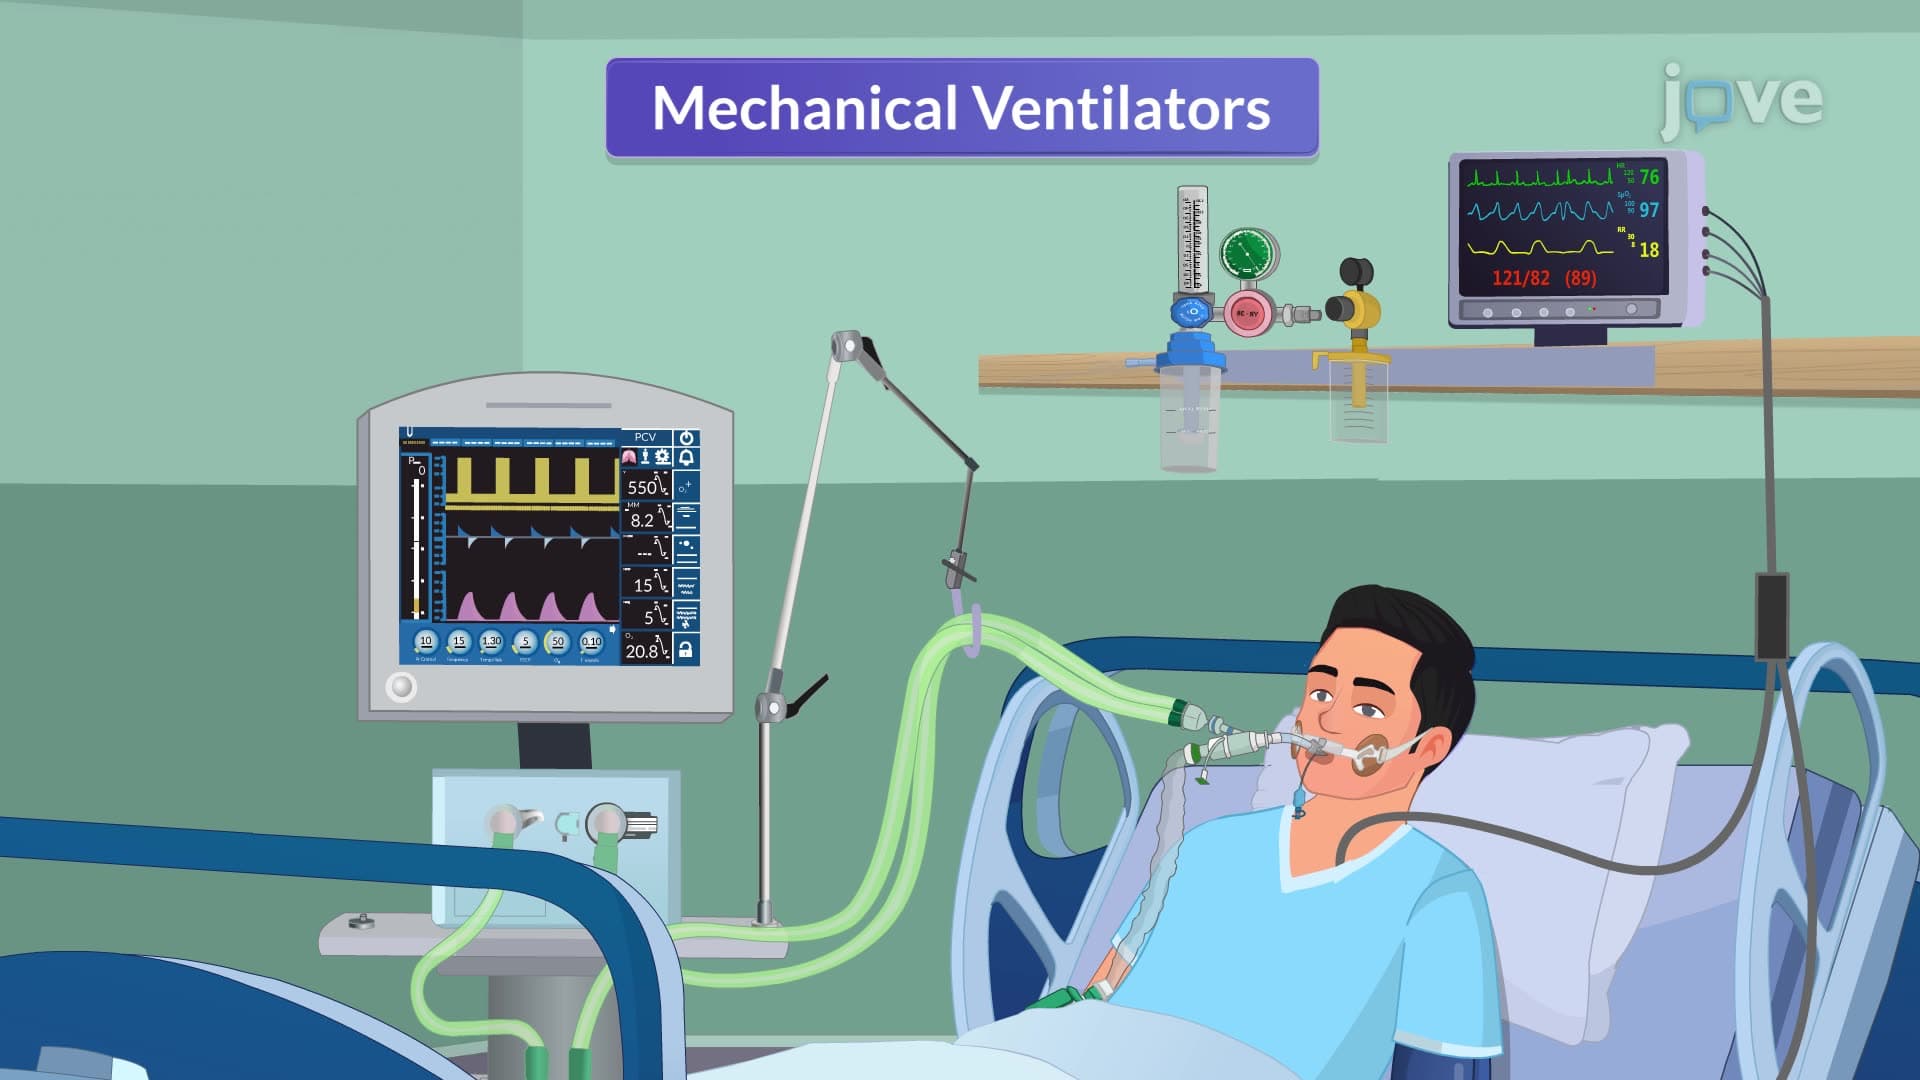
Mechanical Ventilation I: Indication and Settings
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: