Related Experiment Video
Updated: Aug 7, 2026
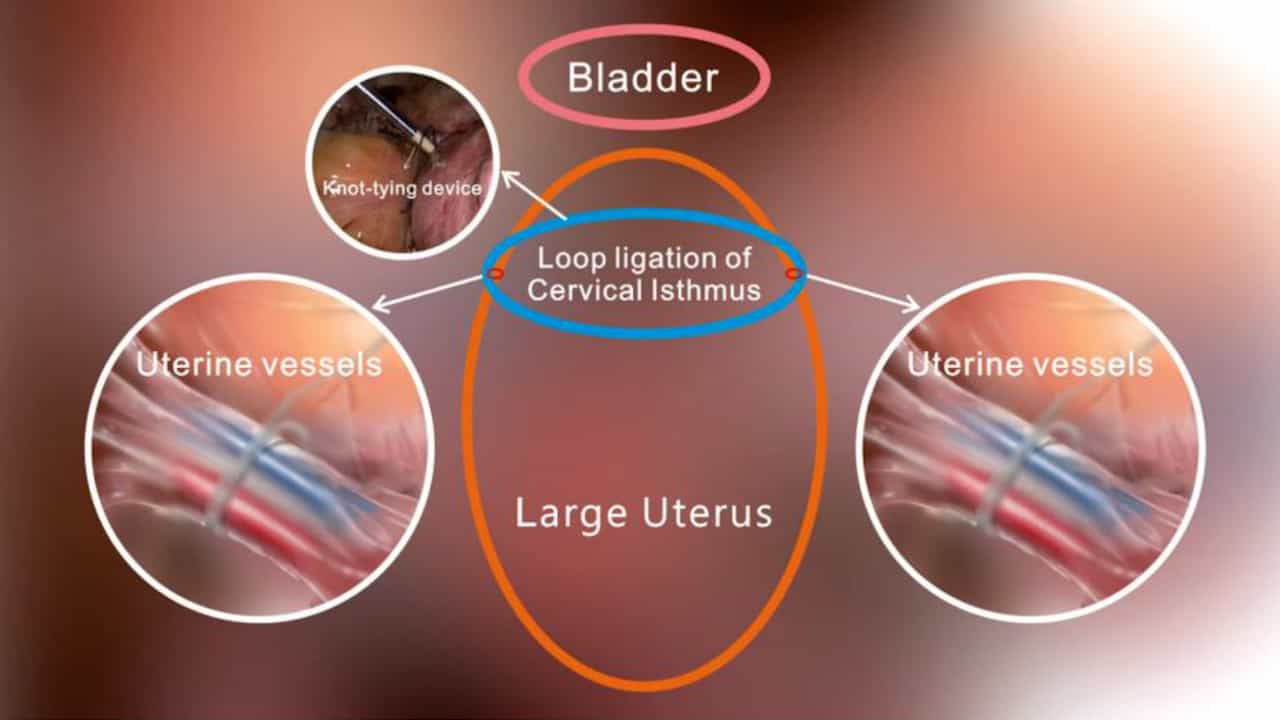

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Uterine artery embolization and hysteroscopic resection to treat retained placenta accreta: A case report
James A Greenberg1, Julie D Miner, Susan K O'Horo
1Department of Obstetrics and Gynecology, Brigham & Women's Hospital, Harvard Medical School, Boston, Massachusetts, USA. jagreenberg@partners.org

Retained placenta is a serious cause of postpartum hemorrhage. Compounding this problem is the rare finding of a retained placenta accreta. Different authors have presented management options for retained placenta accreta that include methotrexate, uterine artery embolization, dilation and curettage, hysteroscopic loop resection, and hysterectomy. We report here on a patient who was diagnosed with a retained placenta accreta and underwent successful conservative treatment with uterine artery embolization followed by hysteroscopic morcellation. Whereas other methods have failed due to bleeding and/or infection, this case illustrates a potential new means of addressing this challenging obstetrical complication.
Retained placenta is a serious cause of postpartum hemorrhage. Compounding this problem is the rare finding of a retained placenta accreta. Different authors have presented management options for retained placenta accreta that include methotrexate, uterine artery embolization, dilation and curettage, hysteroscopic loop resection, and hysterectomy. We report here on a patient who was diagnosed with a retained placenta accreta and underwent successful conservative treatment with uterine artery embolization followed by hysteroscopic morcellation. Whereas other methods have failed due to bleeding and/or infection, this case illustrates a potential new means of addressing this challenging obstetrical complication.