Related Experiment Video
Updated: Aug 7, 2026

Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
Assessment of the different methods to predict equilibrated Kt/V in pediatric hemodialysis
Chookiet Kietkajornkul1, Prapaipim Thirakhupt, Yupapin Chulamokha
1Nephrology Division, Department of Pediatrics, Queen Sirikit National Institute of Child Health.

Insights
Urea rebound in pediatric hemodialysis patients completes within 60 minutes post-dialysis. Single-pool Kt/V overestimates dialysis adequacy, while the Maduell model best correlates with equilibrated Kt/V.
Area of Science:
- Nephrology
- Pediatric Dialysis
- Biomedical Engineering
Background:
- Urea rebound, a post-hemodialysis phenomenon, impacts dialysis adequacy assessment.
- Accurate measurement of dialysis dose (Kt/V) is crucial for pediatric patients.
Purpose of the Study:
- To quantify urea rebound in children undergoing hemodialysis.
- To compare the accuracy of various Kt/V calculation models in this population.
Main Methods:
- Analysis of 50 hemodialysis sessions in 5 pediatric patients (ages 5-18).
- Blood urea sampling at multiple time points: pre-dialysis, intradialysis, post-dialysis, and up to 1 hour post-dialysis.
- Comparison of six Kt/V calculation models: single-pool, Daugirdas, equilibrated, rate equation, Maduell, and Smye.
Main Results:
- Urea rebound was complete by 60 minutes post-dialysis, averaging 30.68%.
- Single-pool Kt/V significantly overestimated dialysis dose compared to equilibrated Kt/V.
- The Maduell model demonstrated the best correlation with equilibrated Kt/V, unlike rate equation and Smye models.
Conclusions:
- Urea rebound in pediatric hemodialysis patients is a significant and prolonged event.
- Single-pool Kt/V calculations are unsuitable for assessing dialysis adequacy in children.
- The Maduell model is recommended for more accurate Kt/V assessment in pediatric hemodialysis.
Objectives:
To determine the degree of urea rebound in children on hemodialysis and compare the different calculation models for Kt/V.
Material And Method:
The present study was performed in 50 hemodialysis sessions of 5 pediatric patients, 2 males and 3 females, aged 5-18 years, who had received hemodialysis for 7-48 months. Blood urea samples were obtained at the beginning, 70 minutes intradialysis, the end and every 10 minutes for 1 hour post- dialysis. The compared 6 different models of Kt/V were single pool, Daugirdas, equilibrated, rate equation, Maduell and Smye method.
Results:
Urea rebound was found to be completed at least 60 minutes post- dialysis and mean percentage value was 30.68 +/- 9.663. Mean value of equilibrated Kt/V was 1.442 +/- 0.259 while that of single-pool Kt/V calculated by InC1/C2 was 1.705 +/- 0.252 leading to overestimation of Kt/V by 0.265 +/- 0.075. Mean value calculated by Daugirdas method was 2.083 +/- 0.336. Mean values obtained by rate equation, Maduell and Smye methods were 1.485 +/- 0.209, 1.442 +/- 0.209 and 1.379 +/- 0.343 which differed from equilibrated Kt/V by 0.086 +/- 0.058 (p = 0.002), 0.069 +/- 0.063 (p = 0.967) and 0.132 +/- 0.132 (p = 0.015), respectively.
Conclusion:
Urea rebound in pediatric patients is completed at least 60 minutes after cessasion of hemodialysis. Kt/V calculated from single-pool is not suitable for children. The Maduell model gives the best correlation to equilibrated Kt/V when compared to rate equation and Smye models.

Related Concept Videos
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:30
Continuous Renal Replacement Therapy
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:20
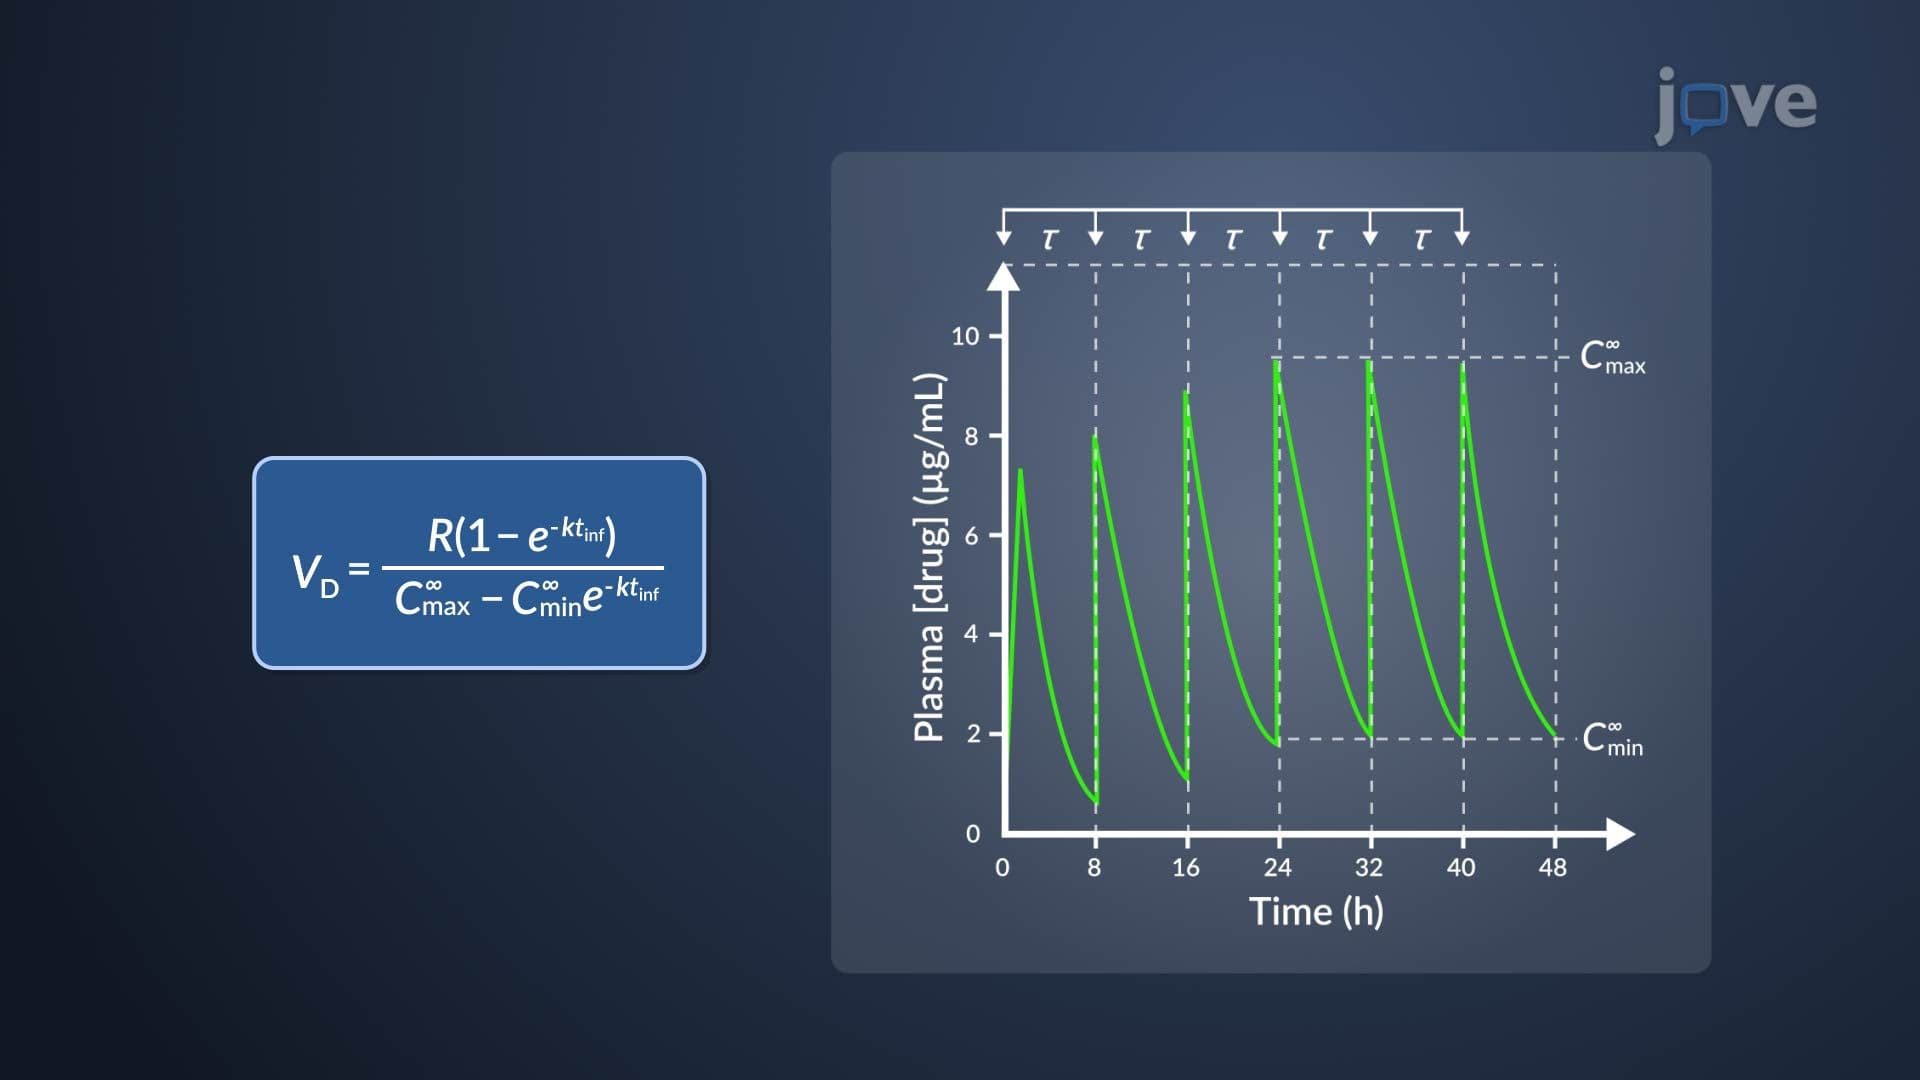
Estimation of k and VD of Aminoglycosides
 01:25
Hemodialysis I: Introduction