Related Experiment Video
Updated: Jul 20, 2026


Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Guidelines for disorders of mineral metabolism and secondary hyperparathyroidism should not yet be modified
Joachim H Ix1, L Darryl Quarles, Glenn M Chertow
1Division of Nephrology, Department of Medicine, Box 0532, HSE 672, University of California, San Francisco, CA 94143-0532, USA. jix@medicine.ucsf.edu

Abstract:
This brief article is a response to the article by Monge et al. on page 326 entitled Reappraisal of 2003 NKF-K/DOQI guidelines for management of hyperparathyroidism in chronic kidney disease patients. We contend that there is insufficient evidence to support the changes to clinical practice and clinical practice guidelines proposed by Monge and colleagues. We recommend that clinical trials be conducted to resolve these points of contention and other critical issues in the management of disorders of mineral metabolism in chronic kidney disease, including secondary hyperparathyroidism. The focus should be on evaluating the effects of alternative strategies on survival, as well as clinical manifestations of cardiovascular and bone disease.
Insights
Evidence is insufficient to support revised guidelines for hyperparathyroidism in chronic kidney disease. More clinical trials are needed to evaluate management strategies for mineral and bone disease, focusing on patient survival and cardiovascular outcomes.
Area of Science:
- Nephrology
- Endocrinology
- Mineral Metabolism
Background:
- Critique of Monge et al.'s reappraisal of NKF-K/DOQI guidelines for hyperparathyroidism in chronic kidney disease (CKD).
- Concerns regarding the sufficiency of evidence supporting proposed changes in clinical practice and guidelines.
Discussion:
- The current evidence base does not adequately support the proposed revisions to the management of secondary hyperparathyroidism in CKD patients.
- Disagreements exist regarding the interpretation of data and its implications for clinical decision-making.
Key Insights:
- Insufficient evidence exists to validate the proposed modifications to the 2003 NKF-K/DOQI guidelines.
- The current approach to managing hyperparathyroidism in CKD requires further rigorous investigation.
Outlook:
- Further clinical trials are essential to resolve current controversies in managing mineral and bone disorders in CKD.
- Future research should prioritize evaluating the impact of alternative management strategies on patient survival and the progression of cardiovascular and bone disease.
Related Concept Videos
 00:59
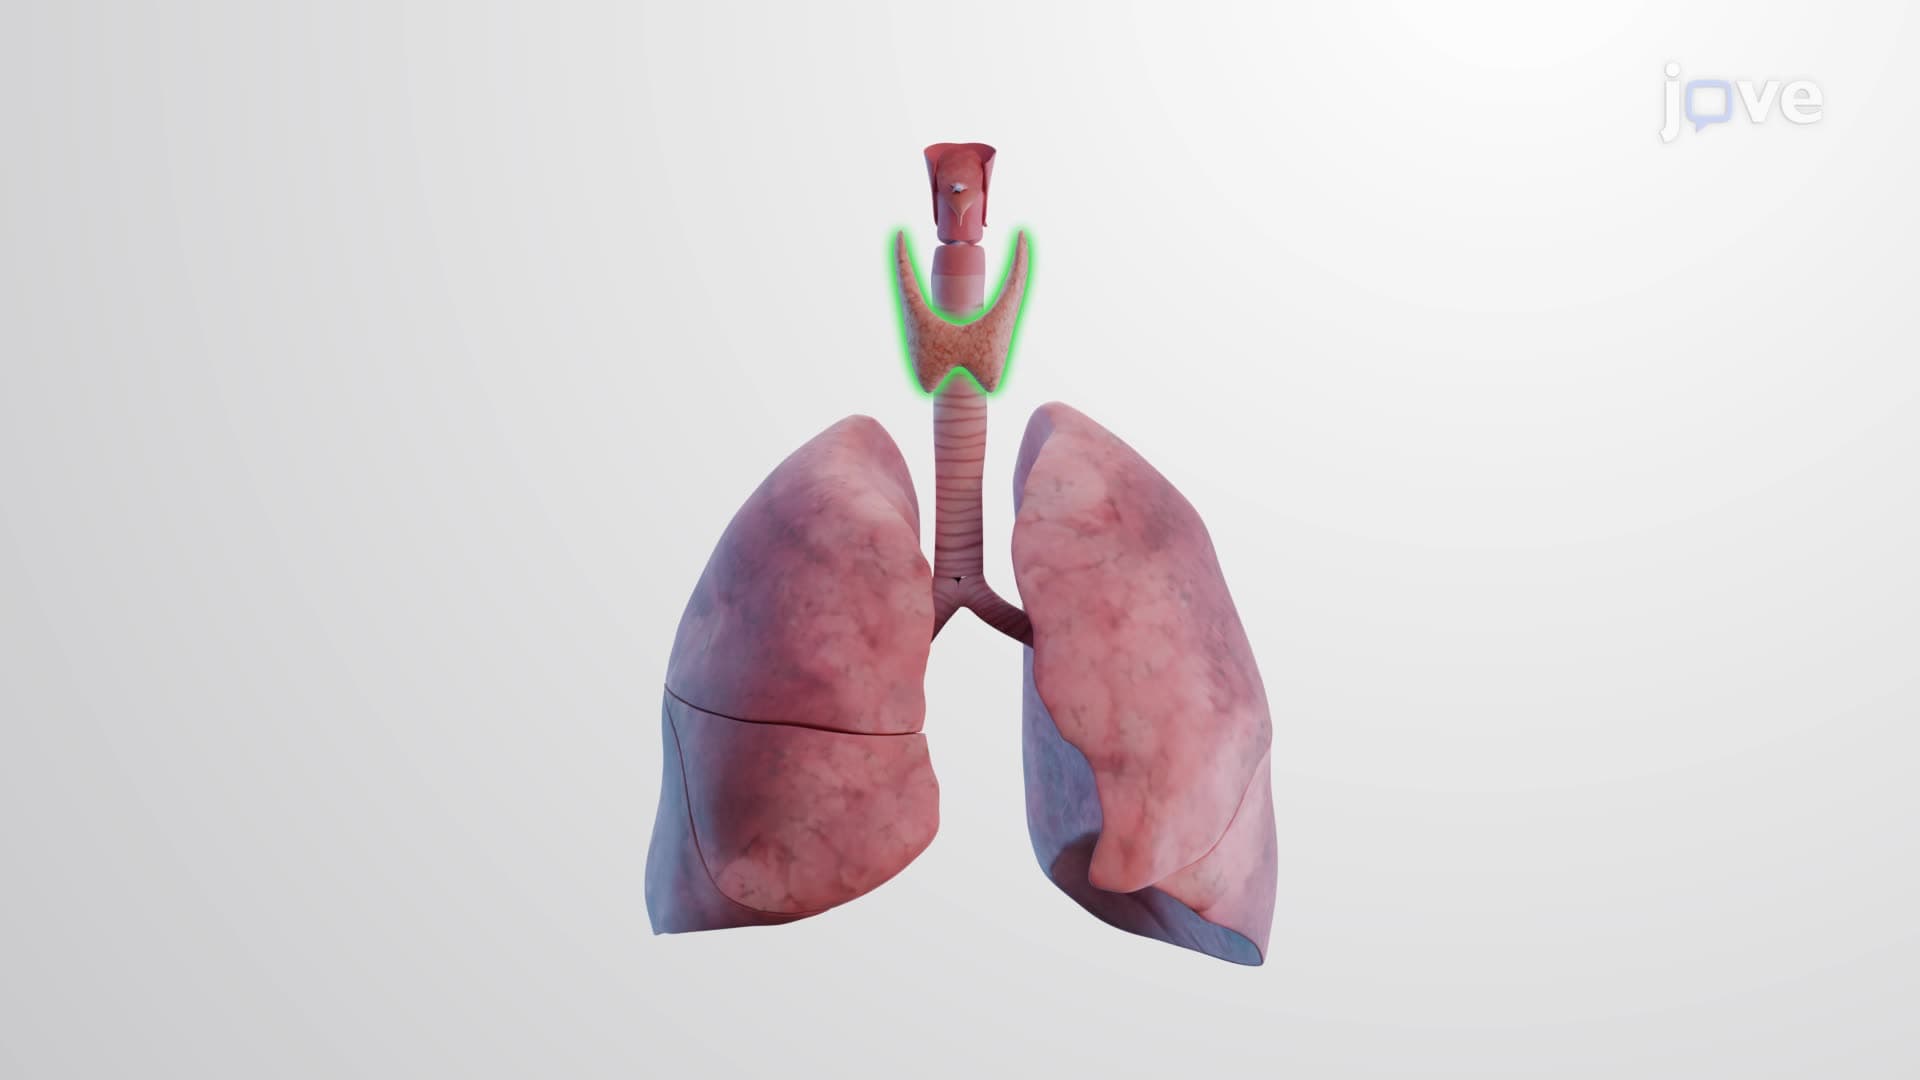
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:25
Peritoneal Dialysis III: Nursing Management
 01:30
Urinary Tract Calculi III: Medical Management