Related Experiment Video
Updated: Jul 19, 2026

Establishment and Evaluation of a Risk Prediction Model for Pathological Escalation of Gastric Low-Grade Intraepithelial Neoplasia
Published on: February 16, 2024
Sporadic versus hereditary gastrinomas of the duodenum and pancreas: distinct clinico-pathological and
Martin Anlauf1, Nele Garbrecht, Tobias Henopp
1Department of Pathology, University of Kiel, Michaelisstrasse 11, 24105 Kiel, Germany. manlauf@path.uni-kiel.de

Abstract:
Gastrinomas are defined as gastrin secreting tumors that are associated with Zollinger-Ellison syndrome (ZES). ZES is characterized by elevated fasting gastrin serum levels, positive secretin stimulation test and clinical symptoms such as recurrent peptic ulcer disease, gastroesophageal reflux disease and occasional diarrhea. Genetically, nonhereditary (sporadic) gastrinomas are distinguished from hereditary gastrinomas, which are associated with multiple endocrine neoplasia type 1 (MEN1) syndrome. In general, duodenal gastrinomas are small and solitary if they are sporadic and multiple as well as hereditary. The sporadic gastrinomas occur in the duodenum or in the pancreas while the hereditary gastrinomas almost all occur in the duodenum. Our series of 77 sporadic duodenal neuroendocrine tumors (NETs) includes 18 patients (23.4%) with gastrinomas and ZES. Of 535 sporadic NETs in the pancreas collected from the NET archives of the departments of pathology in Zurich, Switzerland, and Kiel, Germany, 24 patients (4.5%) suffered from sporadic pancreatic gastrinomas and ZES. These NETs have to be distinguished from tumors with immunohistochemical positivity for gastrin but without evidence of ZES. An additional 19 patients suffered from MEN1 and ZES. These patients showed exclusively duodenal gastrinomas, but not pancreatic gastrinomas. The prognosis of sporadic and MEN1-associated duodenal gastrinomas is better than that of pancreatic gastrinomas, since they progress slowly to liver metastasis. In summary, sporadic and MEN1-associated gastrinomas in the duodenum and pancreas show different clinico-pathological and genetic features. The incidence of sporadic duodenal gastrin-producing tumors is increasing, possibly due to optimized diagnostic procedures. In contrast, pancreatic MEN1-associated gastrinomas seem to be extremely rare. A considerable subset of tumors with immunohistochemical expression of gastrin but without evidence of ZES should be designated as functionally inactive NETs expressing gastrin, but not as gastrinomas.
Related Concept Videos
 01:26
Gastritis II: Pathophysiology
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds to M3...
 01:25
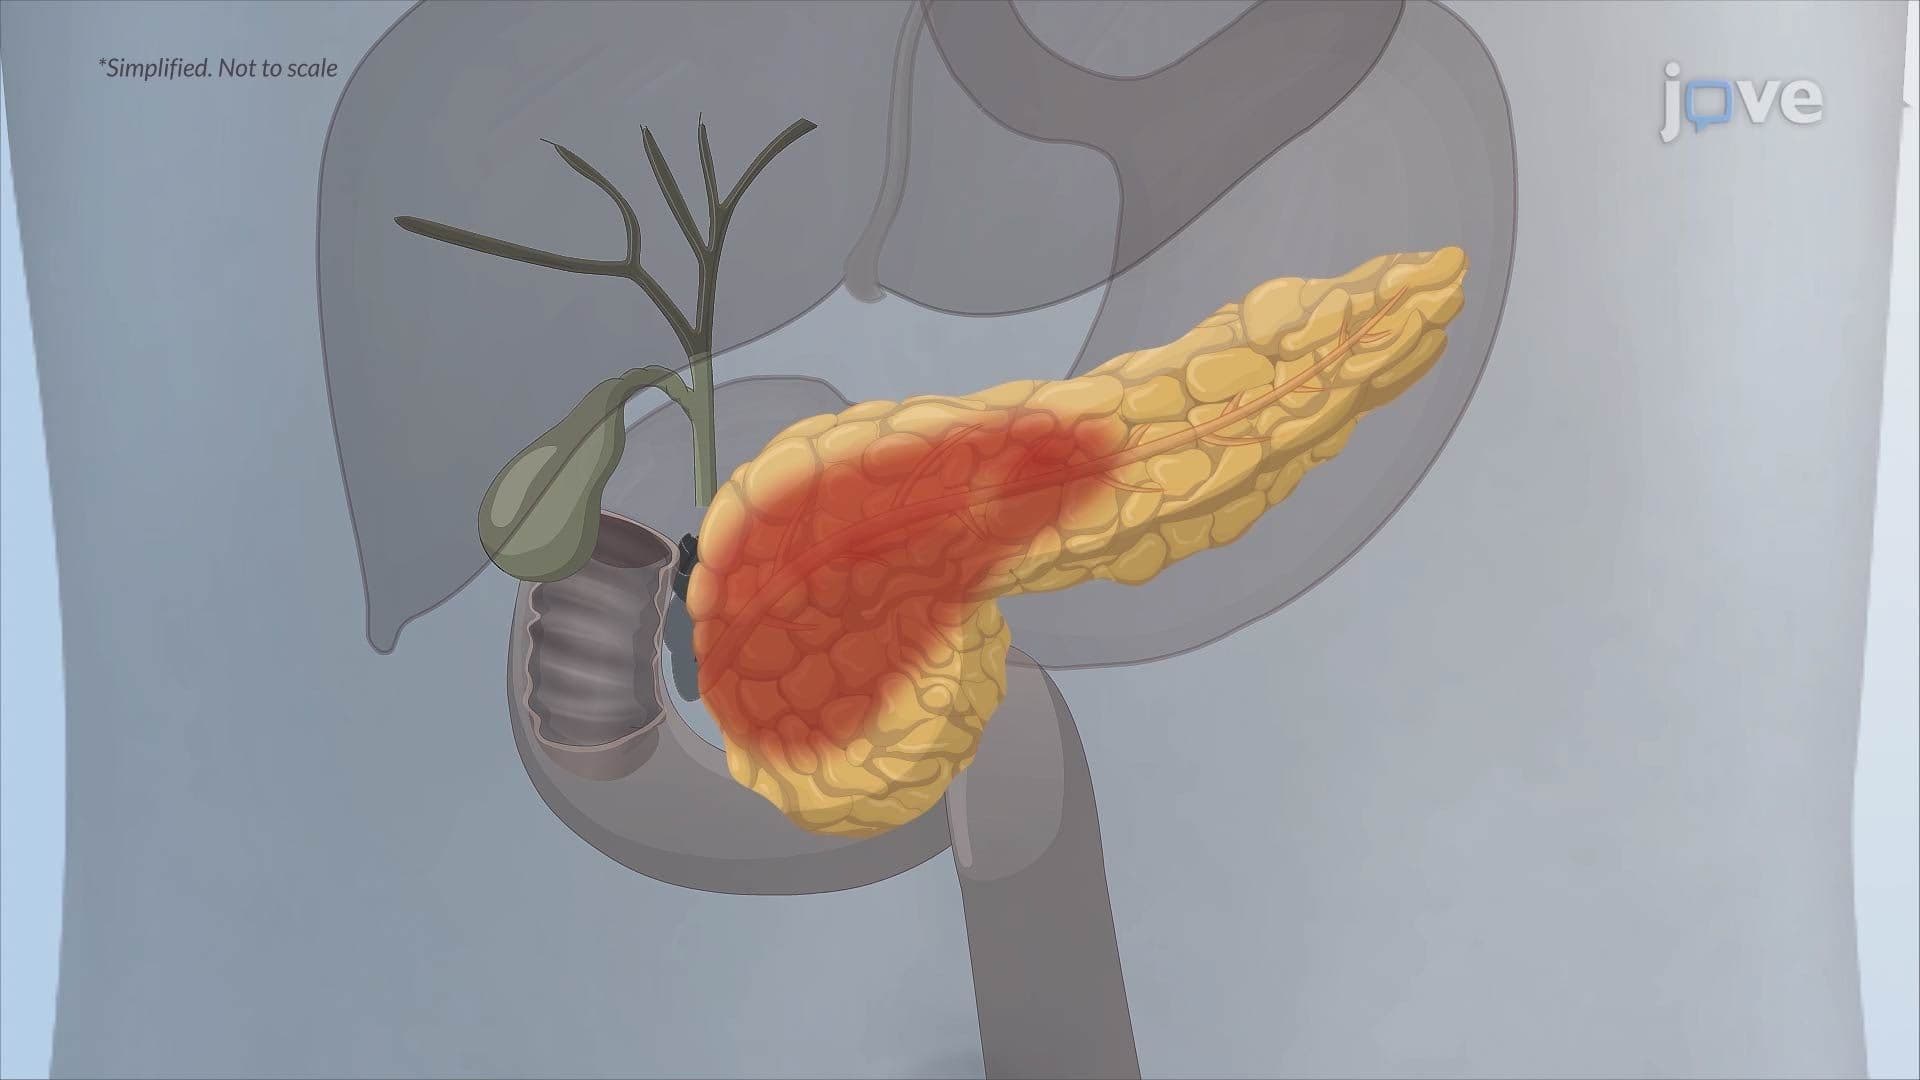
Chronic Pancreatitis I: Introduction