Prediction of acetabular development after closed reduction by overhead traction in developmental dysplasia of the hip
Related Experiment Video
Updated: Jul 19, 2026
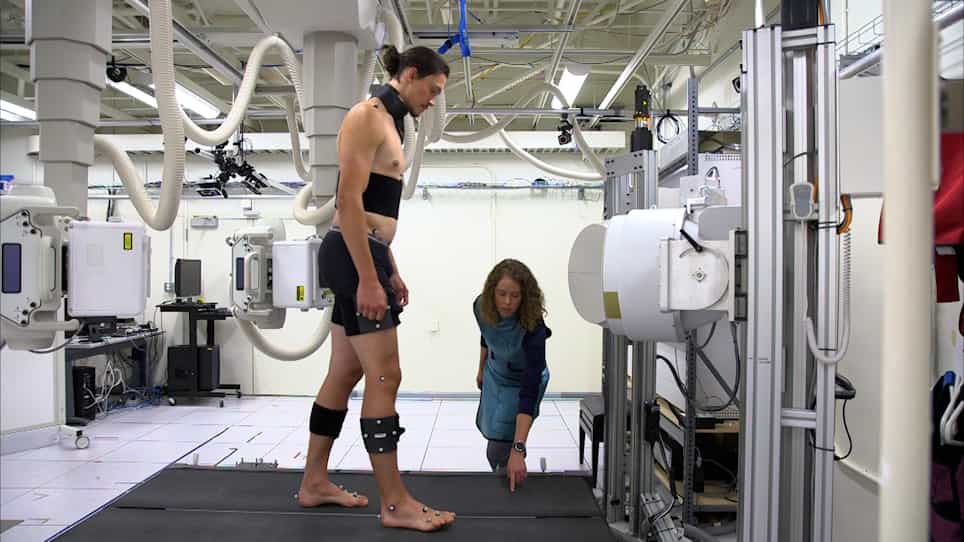
In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Hiroshi Kitoh1, Takahiko Kitakoji, Mitsuyasu Katoh
1Department of Orthopaedic Surgery, Nagoya University School of Medicine, 65 Tsurumai-cho, Showa-ku, Nagoya, 466-8550, Japan.

Insights
Acetabular index and center-edge angle measurements after hip dysplasia reduction can predict long-term outcomes. These early indicators guide treatment timing for acetabuloplasty, preventing unnecessary surgeries.
Area of Science:
- Orthopedic surgery
- Pediatric orthopedics
- Developmental dysplasia of the hip (DDH) research
Background:
- Predicting acetabular development post-reduction is crucial for timely acetabuloplasty in DDH.
- Overhead traction (OHT) is a common treatment for DDH, but its long-term outcomes require further understanding.
Purpose of the Study:
- To identify early and reliable predictors of future acetabular dysplasia in hips treated with OHT.
- To optimize surgical timing for acetabuloplasty and avoid unnecessary interventions.
Main Methods:
- Retrospective review of 45 hips in 40 patients treated with OHT for DDH.
- Analysis of serial measurements including acetabular index (AI) and center-edge angle (CE).
- Correlation of early radiographic findings with skeletal maturity outcomes (Severin classification).
Main Results:
- 38% of hips showed unsatisfactory results (Severin III) at skeletal maturity.
- Acetabular index (AI) at 4 years and center-edge angle (CE) at 5 years post-reduction were significant predictors.
- Bilateral DDH and poor acetabular coverage in the uninvolved hip were associated with poorer outcomes.
Conclusions:
- AI (4 years) and CE (5 years) after OHT are the earliest predictors of final acetabular development.
- Acetabuloplasty decisions should consider these predictors around 4-5 years post-reduction.
- Bilateral DDH and contralateral hip status are key prognostic factors for acetabular development.
Background:
The prediction of acetabular development after reduction of developmental dysplasia of the hip (DDH) is important to ensure optimal timing of acetabuloplasty and to avoid unnecessary surgery. The objective of this study was to find early and reliable predictors of future acetabular dysplasia in the hips reduced by overhead traction (OHT).
Methods:
We retrospectively reviewed 45 hips in 40 patients treated by OHT for DDH without additional procedures. The average age at the time of closed reduction was 9.3 months, and the average age at the latest examination was 17.3 years. Residual hip dysplasia at skeletal maturity was defined according to Severin's classification. The following variables were evaluated as possible predictors of the final outcome: age at reduction, severity of the dislocation, serial measurements of acetabular index (AI), center-edge angle of Wiberg (CE), and the center-head discrepancy distance (CHDD).
Results:
Sixty-two percent of the hips had satisfactory results in Severin I/II and 38% had unsatisfactory results in Severin III. Bilateral DDH showed significantly poorer outcome than unilateral DDH. The average AI of the unsatisfactory group was significantly greater than that of the satisfactory group at 4 years or more after reduction. Similarly, the average CE of the satisfactory group was greater than that of the unsatisfactory group at 5 years or more after reduction. In unilateral cases, the AI and the CE of the uninvolved hip at 1 year after reduction also correlated with the final outcome of the involved hip.
Conclusions:
The AI of 4 years and the CE of 5 years after reduction were the earliest predictors of the final outcome. Careful consideration for the need of acetabuloplasty would be given at 4 or 5 years after reduction by OHT. Bilateral DDH and poor acetabular coverage of the uninvolved hip in unilateral DDH were the prognostic factors of unfavorable acetabular development of the dislocated hip.