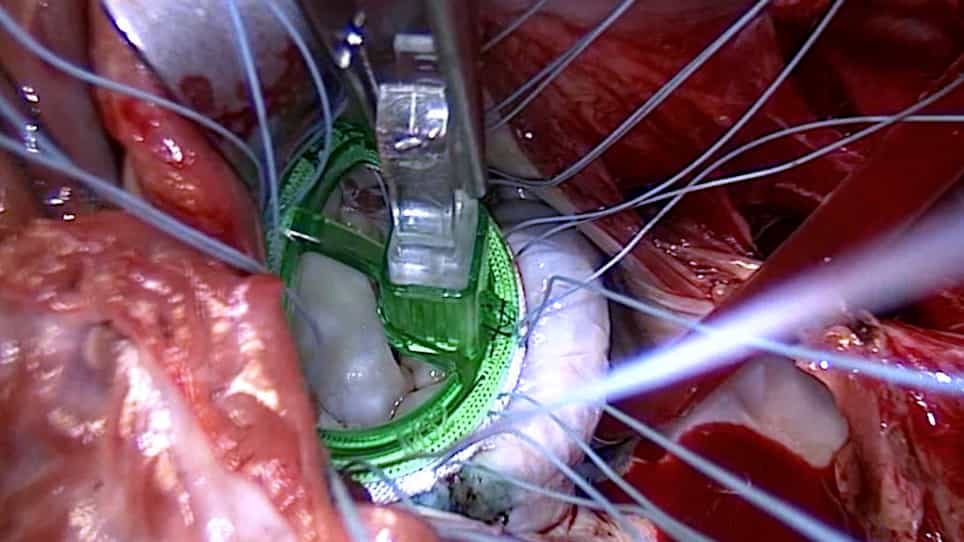
Spontaneous chordae rupture of tricuspid valve in patient with chronic renal failure

Hyungseop Kim1, Yun-Kyeong Cho, Chang-Wook Nam

  • 1Division of Cardiology, Department of Internal Medicine, Keimyung University, Dongsan Medical Center, Junggu Dongsandong 194, Daegu, Republic of Korea. khyungseop@dsmc.or.kr

Related Concept Videos

Mitral Regurgitation I: Introduction01:20

Mitral Regurgitation I: Introduction

Mitral regurgitation is characterized by the backward circulation of blood from the left ventricle to the left atrium during systole, a phase of the cardiac cycle when the heart contracts and pumps blood out of the chambers. This abnormal flow occurs primarily due to the dysfunction of the mitral valve or its supporting structures, which include the mitral leaflets, chordae tendineae, annulus, and papillary muscles.Etiology and Mechanisms:Primary Mitral Regurgitation: This type arises from...
Chronic Kidney Disease II: Clinical Manifestations01:24

Chronic Kidney Disease II: Clinical Manifestations

Chronic Kidney Disease (CKD) progressively impairs multiple body systems due to the accumulation of uremic toxins, which disrupt cellular functions across various organs.Neurologic symptomsNeurologic symptoms often arise early in CKD, as uremic toxin buildup drives changes in cognitive and motor functions. Patients frequently experience fatigue, headache, confusion, difficulty concentrating, and, in severe cases, seizures. Peripheral neuropathy commonly manifests as burning sensations in the...
Continuous Renal Replacement Therapy01:30

Continuous Renal Replacement Therapy

Continuous Renal Replacement Therapy, also known as CRRT, is a procedural treatment for acute kidney injury (AKI) that gradually removes uremic toxins and fluids while maintaining acid-base balance and stabilizing electrolytes. It is particularly useful for hemodynamically unstable patients. Unlike intermittent hemodialysis, which is faster, CRRT provides a gentler approach over 24 hours, closely mimicking the function of natural kidneys. However, CRRT is not ideal for patients with...
Acute Kidney Injury II: Pathophysiology01:29

Acute Kidney Injury II: Pathophysiology

Acute kidney injury (AKI) causes are categorized into three primary categories based on the location of the injury: prerenal, intrarenal (or intrinsic), and postrenal causes. This classification guides clinical management and illustrates how different pathways can impair kidney function.Etiology and Pathophysiology of Acute Kidney Injury1. Prerenal causesEtiology: Prerenal Acute Kidney Injury, the most common type, occurs when reduced blood flow to the kidneys decreases filtration capacity...
Renal Failure: Dose Adjustments01:11

Renal Failure: Dose Adjustments

In patients with renal impairment, drugs undergo significant changes in their pharmacokinetics, which require dosage adjustments to ensure safe and effective therapy.
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
Acute Kidney Injury III: Clinical Manifestations01:29

Acute Kidney Injury III: Clinical Manifestations

Acute Kidney Injury (AKI) progresses through distinct clinical phases: the oliguric, diuretic, and recovery phases, each marked by unique manifestations and challenges.Oliguric Phase:The oliguric phase is the initial stage of AKI, typically lasting 10 to 14 days. This phase is marked by a significant reduction in urine output, usually less than 400 mL per day, indicating decreased kidney function. Fluid retention is a prominent feature, leading to symptoms such as edema, hypertension, and...