Related Experiment Video
Updated: Jul 19, 2026
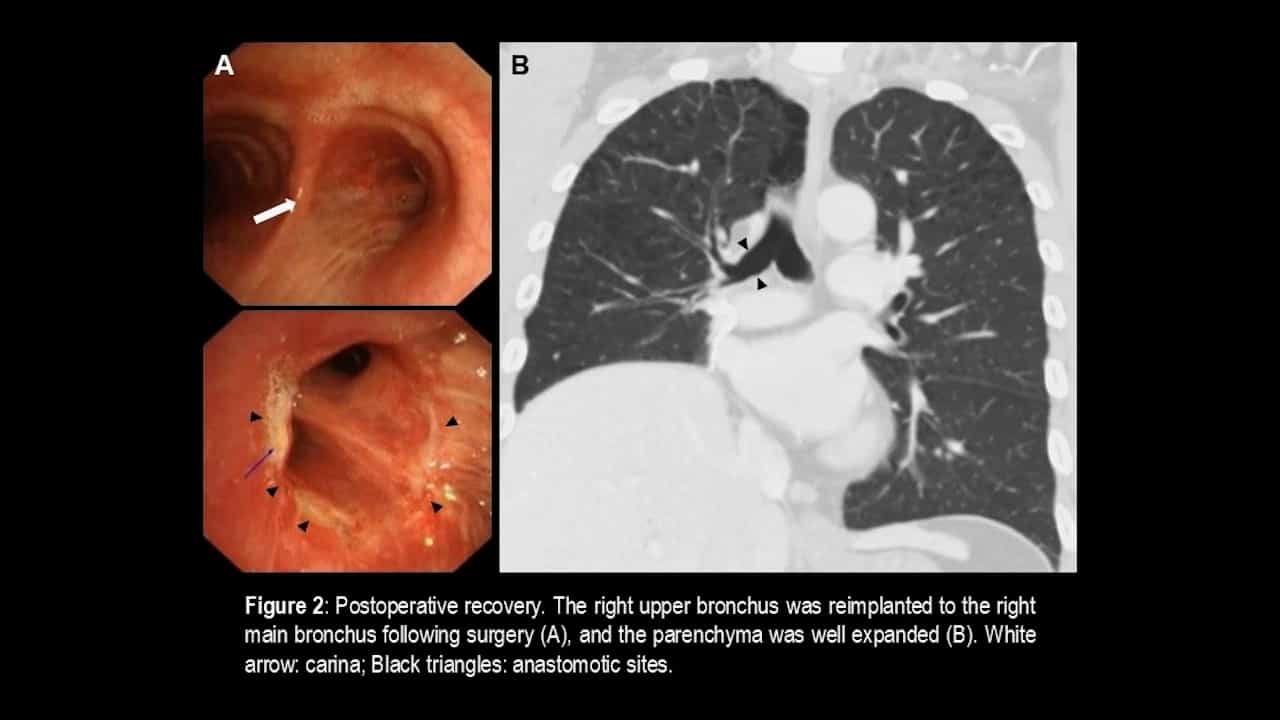
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
Surgery, radiotherapy, and chemotherapy in carcinoma of the esophagus
1University of Southern California, Department of Surgery, Los Angeles, California 90033, USA.

Abstract:
Esophageal carcinoma remains a highly lethal disease that has shown a recent profound increase in prevalence and an equally dramatic epidemiologic shift. There is a well recognized causal association between gastroesophageal reflux disease and adenocarcinoma of the esophagus, and the molecular events underlying this progression from mucosal injury, to metaplasia, to dysplasia, to carcinoma are now becoming clear. Current diagnostic modalities and preoperative staging systems all have significant limitations. Fortunately, chemoprevention strategies and the identification of clinically useful molecular biomarkers that may be used to stage disease and select appropriate therapy are on the horizon. The extent of surgical resection for esophageal carcinoma remains an area of great controversy. Disease that is confined to the mucosa is being diagnosed more commonly, and endoscopic ablative techniques have been proposed. To date, however, preoperative discrimination of tumor depth and presence of regional nodal metastases remains inadequate in these very early lesions, and caution is urged before adopting therapies that may compromise cure. For disease penetrating the mucosa, the extent of surgical therapy must be tailored by the objectives of treatment (cure vs palliation) and preoperative stage. Surgical resection is the current standard of care, with combined-modality therapy reserved for prohibitive surgical candidates. No clear survival benefit has been documented for neoadjuvant radiotherapy or chemotherapy alone. The results of preoperative combined-modality therapy, including three prospective, randomized trials, are encouraging but to date have not shown a definite benefit.
Related Concept Videos
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 02:49
Cancer Therapies
However, cancer treatments can pose several challenges, as therapies used to kill cancer cells are generally also toxic to normal cells. Moreover, cancer cells mutate rapidly and can develop resistance to chemical agents or radiation therapy. Besides, all types of cancer cells may not respond to the same therapy. Some cancer cells respond to one...