Related Experiment Video
Updated: Jul 19, 2026


Nerve-sparing Mid-urethral Obstruction (NeMO) in Female Small Rodents
Published on: April 25, 2017
Refractory overactive bladder in men: update on novel therapies
Casey K Ng1, Ricardo R Gonzalez, Alexis E Te
1Department of Urology, Weill Medical College of Cornell University, 525 E. 68th St., F-9 West, Box 261, New York, NY 10021, USA.

Abstract:
Overactive bladder (OAB) in men is an entity that may be challenging to diagnose and treat, especially in the presence of bladder outlet obstruction. The application of oral medical treatments of lower urinary tract symptoms attributed to benign prostatic hyperplasia has traditionally utilized alpha-adrenergic blockers and 5alpha-reductase inhibitors. After failure of oral medical therapies, surgical options are traditionally offered. Even after surgical options are successful, lower urinary tract symptoms that are secondary to OAB persist. These patients merit a trial of antimuscarinic drugs. Additionally, certain patients with concomitant bladder outlet obstruction who have not been surgically relieved can still merit a trial of antimuscarinic drugs without significant risk of developing urinary retention. When these oral antimuscarinic drugs fail, options still remain for treating men with refractory OAB. Successful application of various diagnostic approaches and the initiation of conservative options as well as other options, such as neuromodulation for refractory urgency and urge incontinence, can help the patient. Finally, emerging data support the use of intradetrusor injections of botulinum toxin for refractory OAB.
Insights
Overactive bladder (OAB) in men, especially with bladder outlet obstruction, requires tailored treatment. Antimuscarinic drugs and newer options like botulinum toxin injections offer solutions for refractory symptoms.
Area of Science:
- Urology
- Men's Health
- Pharmacology
Background:
- Overactive bladder (OAB) in men presents diagnostic and therapeutic challenges, particularly when co-occurring with bladder outlet obstruction.
- Traditional treatments for lower urinary tract symptoms (LUTS) in benign prostatic hyperplasia (BPH) include alpha-blockers and 5-alpha-reductase inhibitors, followed by surgery.
- Persistent LUTS secondary to OAB can occur even after successful surgical interventions for BPH.
Purpose of the Study:
- To review the diagnostic and treatment strategies for overactive bladder in men.
- To discuss the role of antimuscarinic drugs in men with OAB, including those with concomitant bladder outlet obstruction.
- To explore advanced treatment options for refractory OAB in men.
Main Methods:
- Literature review of diagnostic approaches and therapeutic interventions for OAB in men.
- Analysis of the efficacy and safety of oral antimuscarinic drugs.
- Evaluation of surgical outcomes and subsequent OAB management.
- Review of neuromodulation and botulinum toxin as treatment modalities.
Main Results:
- Antimuscarinic drugs are indicated for men with persistent OAB symptoms, even with unre lieved bladder outlet obstruction, with careful risk assessment for urinary retention.
- For cases refractory to oral medications, neuromodulation and intradetrusor injections of botulinum toxin are effective options.
- A stepwise approach combining conservative measures, pharmacotherapy, and advanced interventions is crucial.
Conclusions:
- Men with OAB, especially those with bladder outlet obstruction, benefit from a structured treatment algorithm.
- Antimuscarinic therapy is a viable option, with careful consideration of potential side effects.
- Refractory OAB in men can be effectively managed with neuromodulation and botulinum toxin injections.
Related Concept Videos
 01:30
Urinary Tract Calculi III: Medical Management
 01:30
Urinary Tract Infection III: Diagnostic Studies and Interprofessional Care
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:23
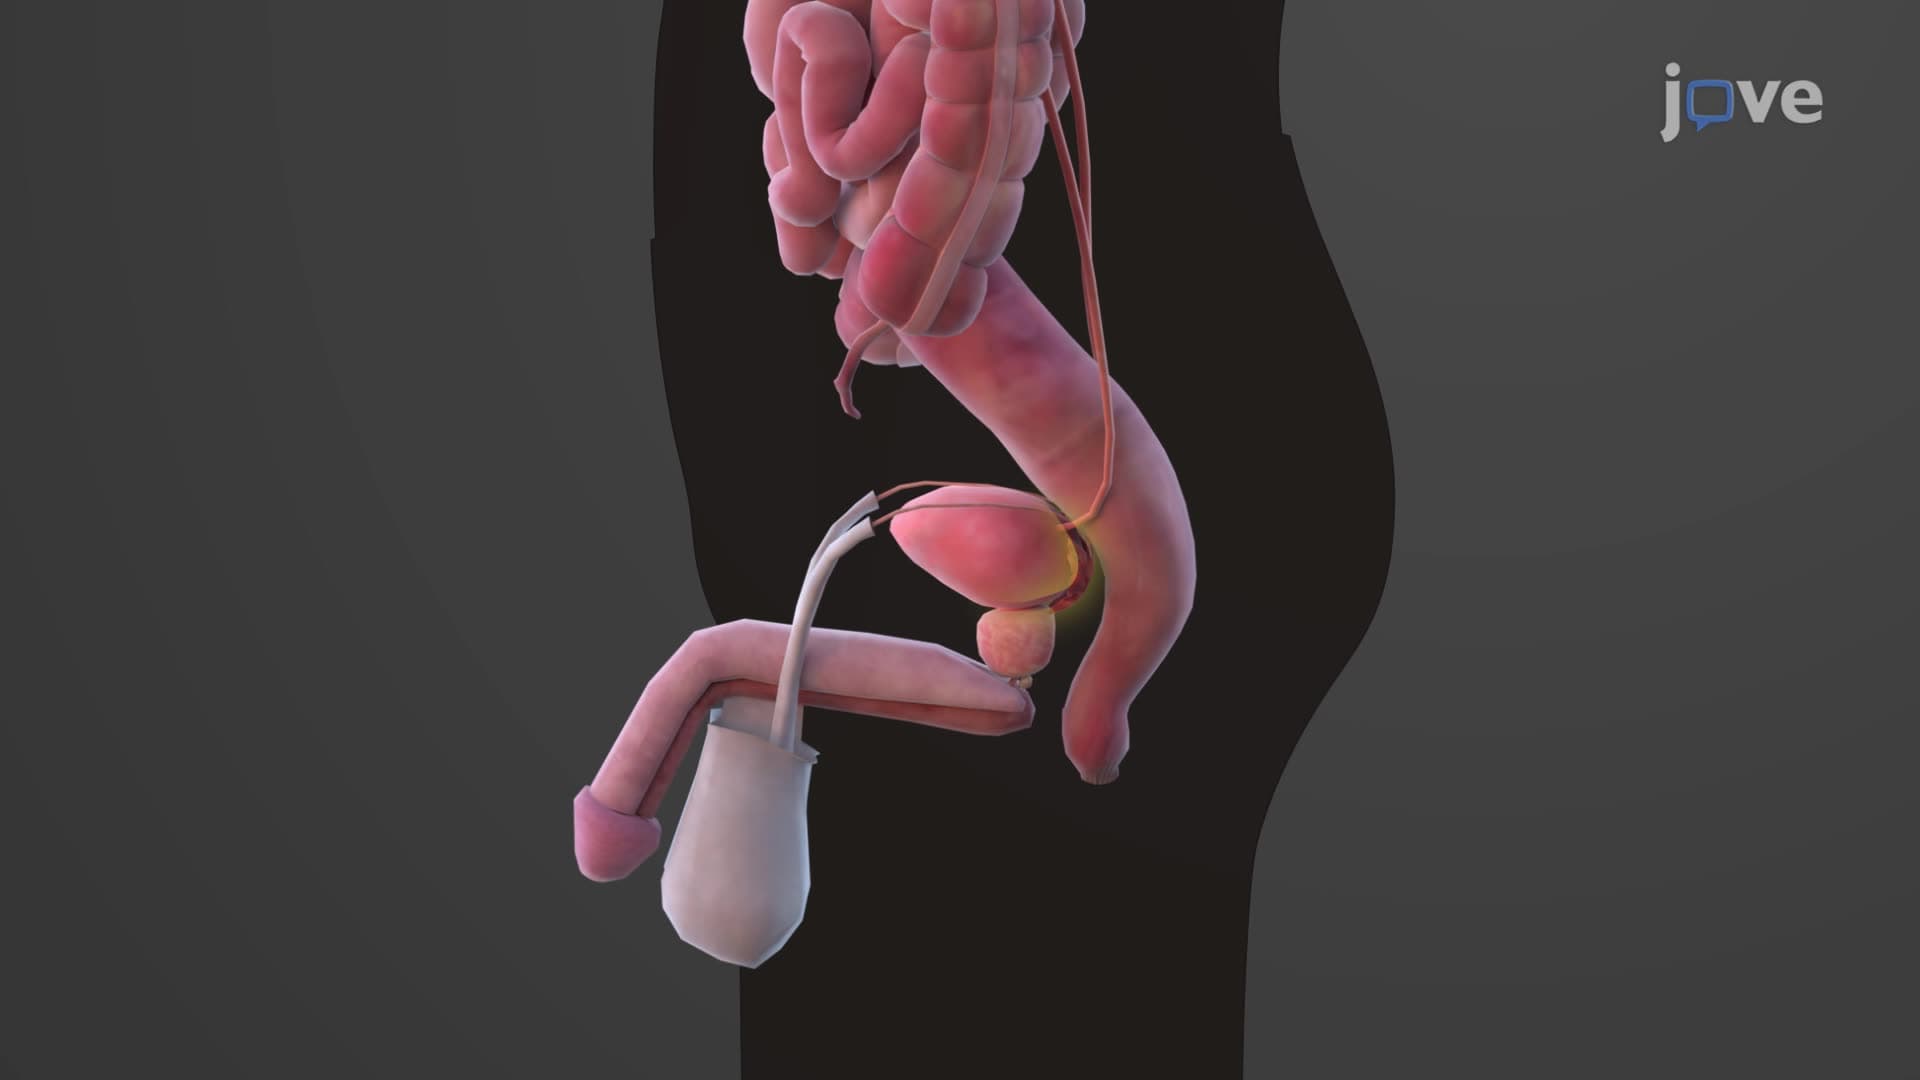
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:17
Urinary Tract Infection IV: Nursing Management