Related Experiment Video
Updated: Feb 15, 2026
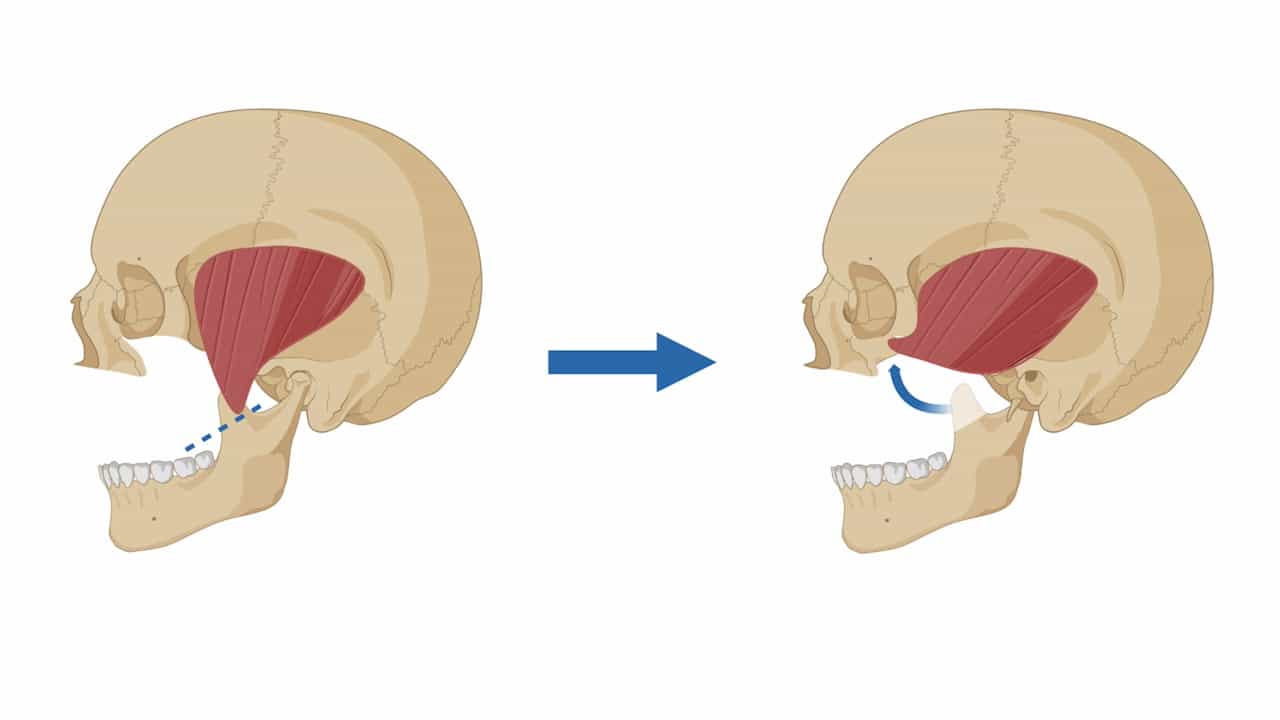

Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
Salvage of infected spinal hardware with paraspinous muscle flaps: anatomic considerations with clinical correlation
C Scott Hultman1, Glyn E Jones, Albert Losken
1Division of Plastic and Reconstructive Surgery, University of North Carolina, Chapel Hill, NC 27599-7195, USA. cshult@med.unc.edu

Purpose:
Infected spinal stabilization devices represent a significant reconstructive challenge by threatening spinal stability and increasing the risk of neurologic complications. This study provides an anatomic and clinical investigation of posterior midline trunk reconstruction using paraspinous muscle flaps as the primary method of repair.
Methods:
We retrospectively analyzed a series of 25 consecutive patients (mean age, 57.2 years; range, 32-78 years) with complex spinal wounds, reconstructed with paraspinous muscle flaps, at a single university healthcare system. To help define the versatility of these muscle flaps, we also performed cadaveric dissections with lead oxide injections in 10 specimens, with an emphasis on regional blood supply, flap width, and arc of rotation.
Results:
From 1994 to 2000, we successfully reconstructed 25 patients with complex spinal wounds, using 49 paraspinous muscle flaps as the primary method of reconstruction. Hardware present in 22 patients was replaced or retained in 17 cases. Long-term spinal fusion with preservation of neurologic status was observed in all patients, with no cases of dehiscence or reinfection. Wound complications included cerebrospinal fluid leak (1), skin necrosis (1), sinus tracts (3), and seroma (2). Mean length of stay was 24 days (range, 8-57 days). One postoperative death occurred. Paraspinous dissections and injections confirmed a segmental type IV blood supply with medial and lateral perforators, arising from intercostal vessels superiorly and lumbar and sacral vessels inferiorly. Flap width was 8 cm at the sacral base, 5 cm at the level of the inferior scapular angle, and 2.5 cm at the first thoracic vertebra.
Conclusions:
Paraspinous muscle flaps can be used as the primary reconstructive option to cover and preserve spinal hardware, control local infection, and enable long-term spinal stabilization. Cadaveric dissections confirmed the usefulness of paraspinous flaps, which can be based upon lateral or medial perforators and can be safely mobilized to reliably reconstruct complex spinal wounds.
Related Concept Videos
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 02:20
Correlations
 01:27
Correlation and Causation
Correlation versus Causation
If the dependent variable increases or decreases when the independent variable increases, there is a positive or negative...
 01:09
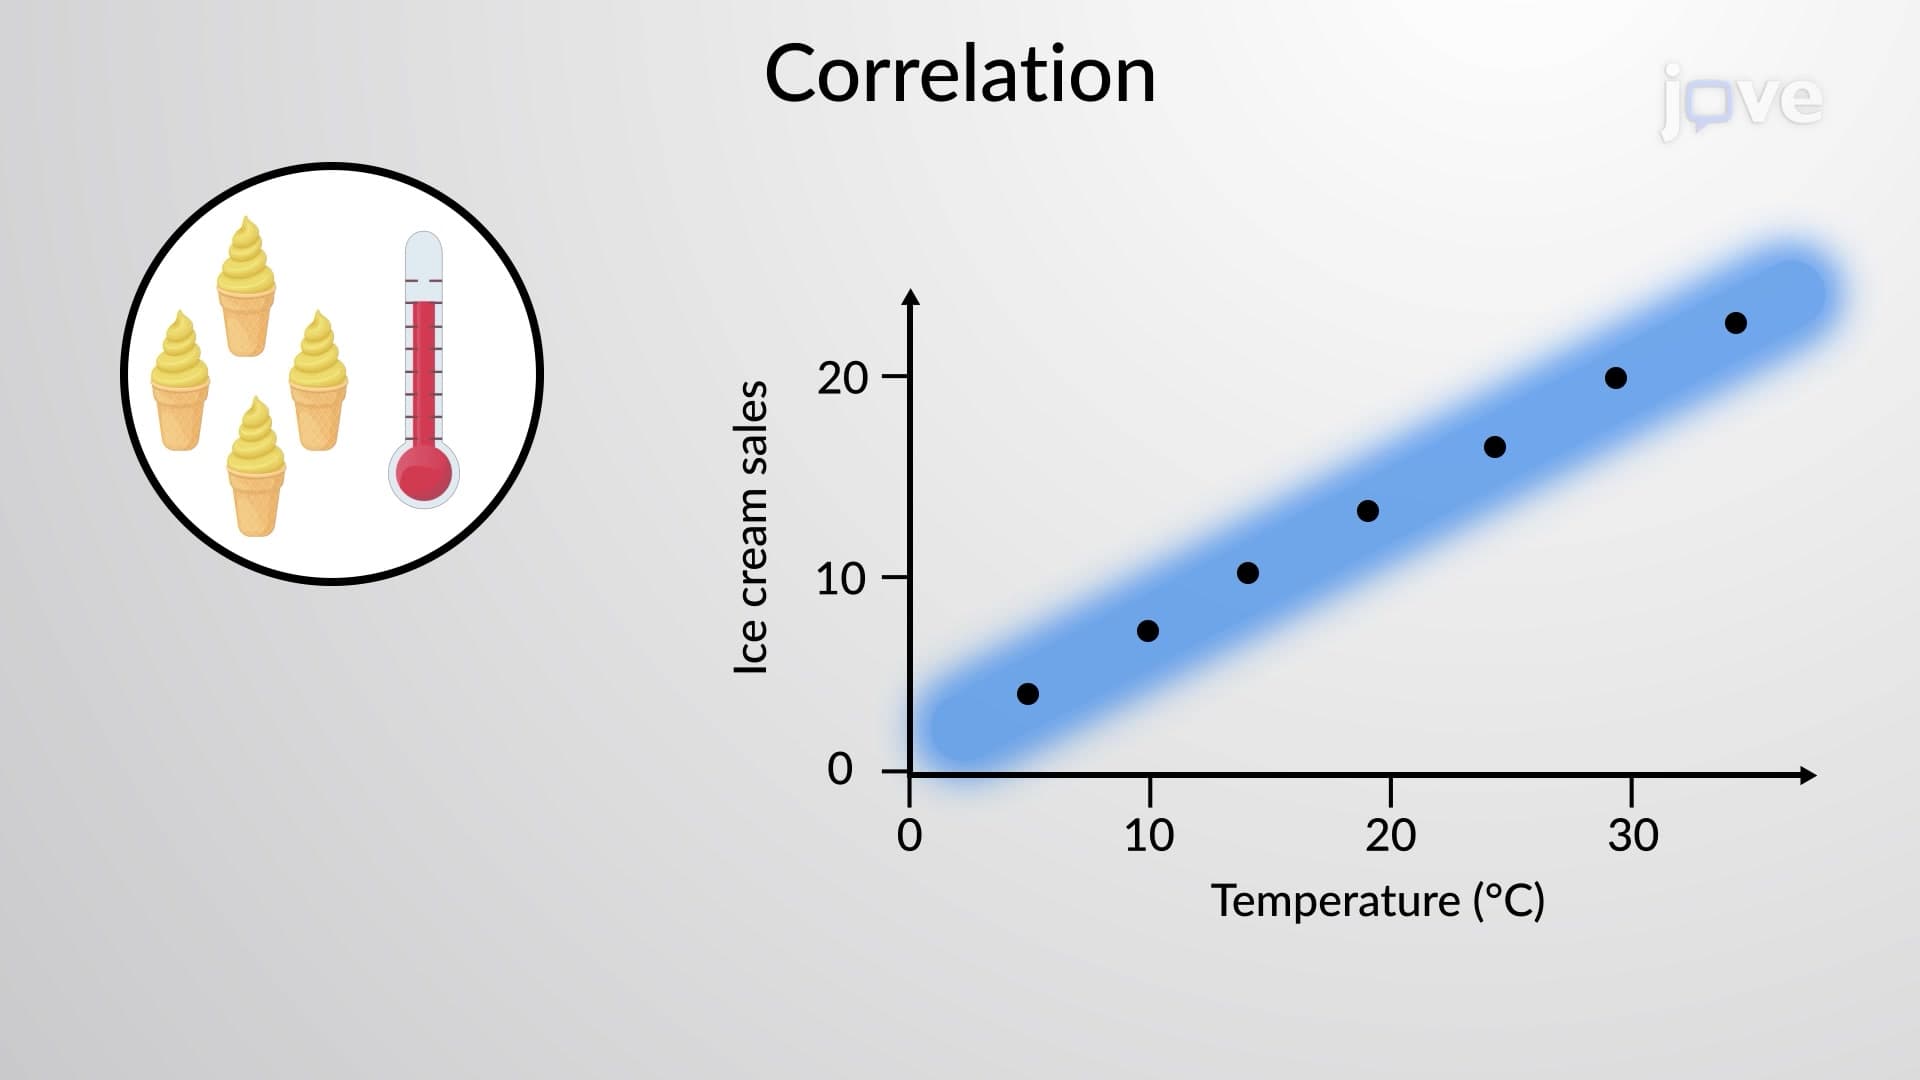
Correlation
Two variables, for example, a and b, are said to be positively correlated if both variables move in the same direction. In other words, a positive correlation exists between two variables, a and b, if:
 01:22
Design Consideration
The factor of safety is another key...