Related Experiment Video
Updated: Jul 19, 2026
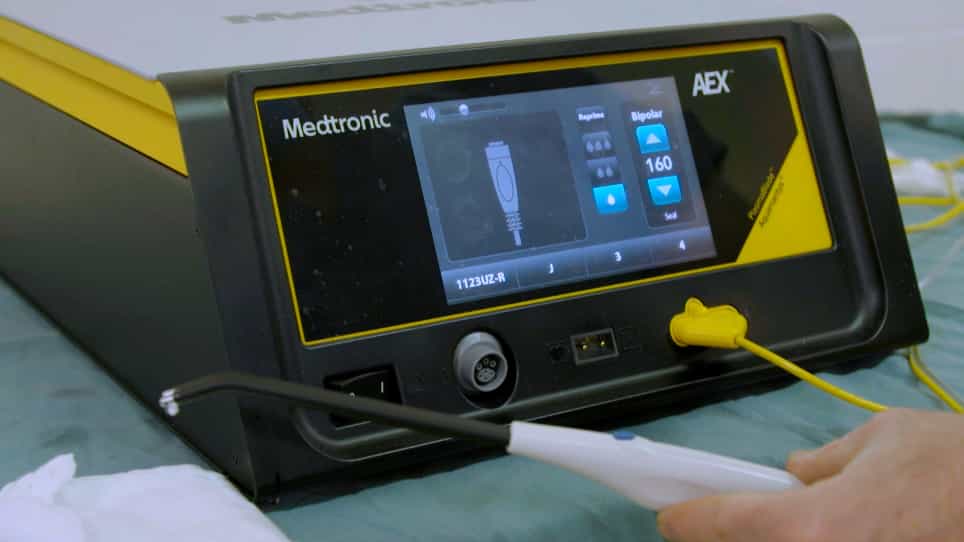

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Failure of nonoperative management of abdominal solid organ injuries
Dan A Galvan1, Andrew B Peitzman
1Department of Critical Care Medicine, University of Pittsburgh, Pittsburgh, Pennsylvania 15213, USA.

Insights
Nonoperative management of blunt splenic injury is generally successful in children and adults. However, careful consideration of factors influencing failure rates is crucial to improve outcomes and avoid patient harm.
Area of Science:
- Trauma Surgery
- Pediatric Surgery
- Surgical Management
Background:
- Nonoperative management (NOM) of blunt splenic injury has been standard in pediatric surgery for 25 years.
- NOM of blunt liver and spleen trauma became a template in adult trauma surgery.
- NOM offers significant benefits to hemodynamically stable patients with blunt liver or splenic trauma.
Purpose of the Study:
- To review the success and failure rates of nonoperative management for blunt splenic and liver injuries.
- To identify factors influencing the success or failure of nonoperative management.
- To discuss strategies for improving organ salvage and reducing failures in NOM.
Main Methods:
- Review of recent literature on nonoperative management of blunt splenic and liver injuries.
- Analysis of factors impacting success and failure rates.
- Discussion of clinical judgment, imaging, and interventional techniques.
Main Results:
- Factors influencing NOM success/failure include guidelines, postsplenectomy infection risk, clinical judgment, CT findings, multiple solid organ injuries, hollow viscus injury risk, and angioembolization drawbacks.
- Despite documented failures, NOM has been generally successful for blunt splenic and liver trauma.
- Ongoing efforts aim to enhance organ salvage and minimize NOM failures.
Conclusions:
- Nonoperative management of blunt splenic and liver injuries is largely successful.
- Continuous efforts are needed to improve organ salvage rates and reduce failure instances.
- Balancing enthusiasm for NOM advancement with patient safety is paramount to avoid imperiling vulnerable subpopulations.
Purpose Of Review:
Nonoperative management of the spleen has been the conventional approach for dealing with blunt splenic injury in children for 25 years. Following acceptance in the field of pediatric surgery, nonoperative management of blunt injury to the liver and spleen became the template in adult trauma surgery. It has proven to be of unequivocal benefit to the majority of hemodynamically stable pediatric and adult patients who have suffered blunt liver or splenic trauma. Offsetting these gains, has been the presence of failures.
Recent Findings:
The recent literature has focused on factors which may impact the nonoperative management success or failure rate. These factors include initiation of guidelines, risk of overwhelming postsplenectomy infection, character of clinical judgment, role of computed tomography in detecting associated intraabdominal injuries, the presence of more than one solid organ injury, risk of associated hollow viscus injury, and the drawbacks of angioembolization.
Summary:
Despite the failures of nonoperative management outlined in this review, the approach has been generally successful. Efforts at improving organ salvage rates and diminishing failures with this approach continue. Notwithstanding our enthusiasm to advance this method of patient care, we must avoid imperiling a subpopulation of patients in our attempt to improve nonoperative management success rates.
Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:07
Intestinal Obstruction II: Pathophysiology
 01:26
Aneurysm III: Interprofessional Care
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:29
Intestinal Obstruction I: Introduction