Related Experiment Videos

[A case of duodenal carcinoma with massive peritoneal carcinomatosis complicating a pulmonary embolism]

Kohei Shitara1, Masaki Munakata, Yuh Sakata

  • 1Dept. of Medical Oncology, Misawa City Hospital.

Related Concept Videos

Pulmonary Embolism I: Introduction01:29

Pulmonary Embolism I: Introduction
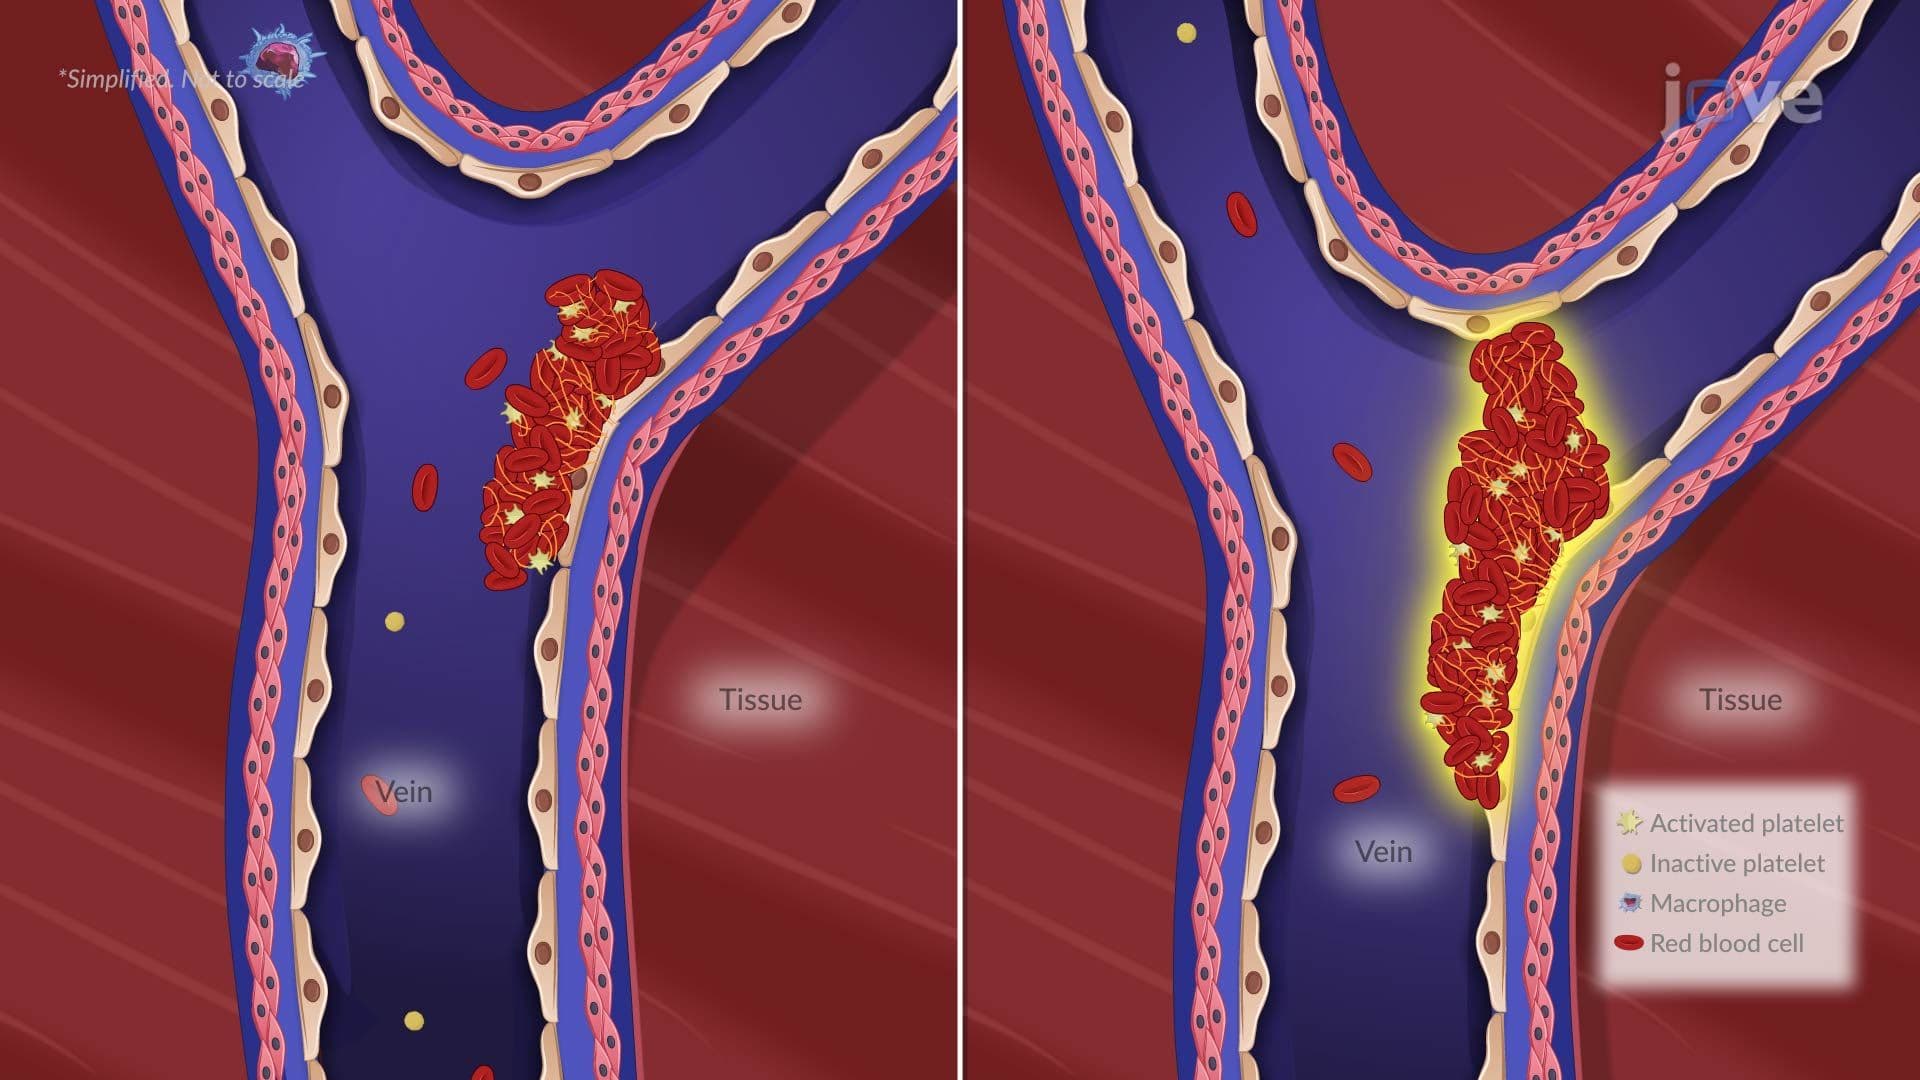
Pulmonary embolism (PE) occurs when a thrombus, fat or air embolus, amniotic fluid, or tumor tissue blocks one or more pulmonary arteries. These blockages originate in the venous system or the right side of the heart.EtiologyPE primarily arises from deep vein thrombosis (DVT) and other hypercoagulable states, such as inherited thrombophilias. Additional etiological factors include venous stasis, commonly seen in obesity, and endothelial injury from surgery and trauma. Less common causes include...
Pulmonary Embolism I: Introduction01:19

Pulmonary Embolism I: Introduction

A blood clot, or thrombus, is a semi-solid mass composed of fibrin, platelets, and red blood cells. When it forms within a vessel, it can obstruct blood flow, known as thrombosis. If part of the clot detaches, it becomes an embolus that can travel and block distant vessels. When this occurs in the pulmonary arteries, it causes a condition known as pulmonary embolism (PE).Origin and ImpactMost often, the embolus originates from a thrombus in the deep veins of the lower limbs, a condition called...
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care01:29

Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care

Diagnosing Pulmonary EmbolismDiagnosing pulmonary embolism (PE) involves clinical assessment and advanced imaging tests. The preferred diagnostic tool is the spiral (helical) CT scan or CT angiography (CTA), which uses intravenous contrast media to visualize the pulmonary vasculature and identify emboli.A ventilation-perfusion (V/Q) scan is an alternative for patients unable to receive contrast media. This scan includes both perfusion and ventilation scanning. Perfusion scanning involves...
Intestinal Obstruction II: Pathophysiology01:07

Intestinal Obstruction II: Pathophysiology

Intestinal obstruction triggers a series of physiological responses, starting with gas and fluid accumulation in the bowel segment proximal to the obstruction, leading to distension. This distended intestine compresses the diaphragm, hindering lung expansion and potentially leading to reduced respiratory effort, atelectasis, and pneumonia.To overcome the blockage, the gut intensifies contractions, causing colicky abdominal pain, nausea, and vomiting, which reduces fluid and food intake and...
Pulmonary Embolism III: Nursing Management01:27

Pulmonary Embolism III: Nursing Management

A pulmonary embolism occurs when a thrombus, amniotic fluid, tumor tissue, fat, or air embolus blocks one or more pulmonary arteries. Effective nursing management and patient education are crucial for improving outcomes and preventing recurrence.Nursing management starts with obtaining a comprehensive patient history, particularly noting any history of deep vein thrombosis (DVT). Assess for clinical manifestations, including dyspnea, chest pain, crackles, heart murmurs, and signs of right-sided...
Peptic Ulcer Disease III: Clinical Manifestations and Complications01:25

Peptic Ulcer Disease III: Clinical Manifestations and Complications

Duodenal UlcersDuodenal ulcers are the most common form of peptic ulcer disease, presenting with chronic, intermittent epigastric pain. Pain typically appears 2–3 hours after meals, especially when the stomach is empty, often waking patients at night. It is characteristically relieved by food or antacids (“pain–food–relief”). Some patients remain asymptomatic until complications like bleeding or perforation emerge, particularly with NSAID or anticoagulant use.Gastric UlcersGastric ulcers share...