Related Experiment Video
Updated: Jul 17, 2026


A Modified Simple Method for Induction of Myocardial Infarction in Mice
Published on: December 3, 2021
A population-based analysis of the class effect of beta-blockers after myocardial infarction
Stéphane Rinfret1, Michal Abrahamowicz, Jack Tu
1Division of Cardiology, Department of Medicine, Centre Hospitalier de l'Université de Montréal, Montreal, Quebec, Canada.

Insights
Beta-blockers reduce mortality after acute myocardial infarction (AMI). However, this study found higher mortality with metoprolol compared to acebutolol or atenolol, challenging the idea of a universal class effect for AMI secondary prevention.
Area of Science:
- Cardiology
- Pharmacology
- Public Health
Background:
- Long-term beta-blocker use is associated with reduced mortality following acute myocardial infarction (AMI).
- The existence of a class effect for beta-blockers in secondary AMI prevention remains uncertain.
Purpose of the Study:
- To investigate whether beta-blockers exhibit a class effect in reducing mortality among elderly patients post-AMI.
- To compare the mortality rates associated with metoprolol, atenolol, and acebutolol in secondary AMI prevention.
Main Methods:
- Analysis of administrative healthcare data for Canadian patients aged 65+ discharged with AMI (1996-2000).
- Comparison of mortality rates between patients prescribed metoprolol, acebutolol, or atenolol within 90 days of discharge.
- Statistical control for clinical characteristics, comorbidities, and medication dosage and duration.
Main Results:
- Among 31,576 patients, metoprolol was most common (67%), followed by atenolol (24%) and acebutolol (9%).
- Acebutolol (HR 0.71) and atenolol (HR 0.79) were associated with significantly lower mortality compared to metoprolol, after adjusting for multiple factors.
- No significant differences in clinical characteristics or beta-blocker coverage duration were observed between the groups.
Conclusions:
- The observed differential mortality rates challenge the notion of a uniform class effect for beta-blockers in the secondary prevention of AMI.
- Metoprolol use was associated with higher mortality compared to atenolol and acebutolol in this elderly cohort.
- Further research is warranted to understand the specific mechanisms underlying these observed differences.
Background:
Long-term treatment with beta-blockers reduces mortality after acute myocardial infarction (AMI). Whether beta-blockers exert a class effect is unknown.
Methods:
We analyzed mortality after AMI in Canadian patients 65 years or older who were discharged from hospital with a diagnosis of AMI from April 1996 to March 2000. Administrative data from Quebec, Ontario, and British Columbia were merged. We compared patients prescribed with metoprolol, acebutolol, or atenolol within 90 days after discharge.
Results:
Among 31576 patients, 67% were prescribed with metoprolol, 24% with atenolol, and 9% with acebutolol. Clinical characteristics and proportion of days covered with a beta-blocker prescription were similar across groups. Although controlling for time-dependent covariates representing current use and dosage, as well as for age, sex, congestive heart failure, and several other comorbidities, patients who filled a prescription for acebutolol (hazard ratio 0.71, 95% CI 0.62-0.81) or atenolol (hazard ratio 0.79, 95% CI 0.73-0.87) had significantly lower mortality in comparison with metoprolol.
Conclusions:
The higher mortality observed in patients receiving metoprolol compared with those receiving atenolol or acebutolol challenges the concept of a class effect of beta-blockers for secondary prevention of AMI.

Related Concept Videos
 01:22
Heart Failure Drugs: β-Blockers
 01:28
Antihypertensive Drugs: Types of β-Blockers
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
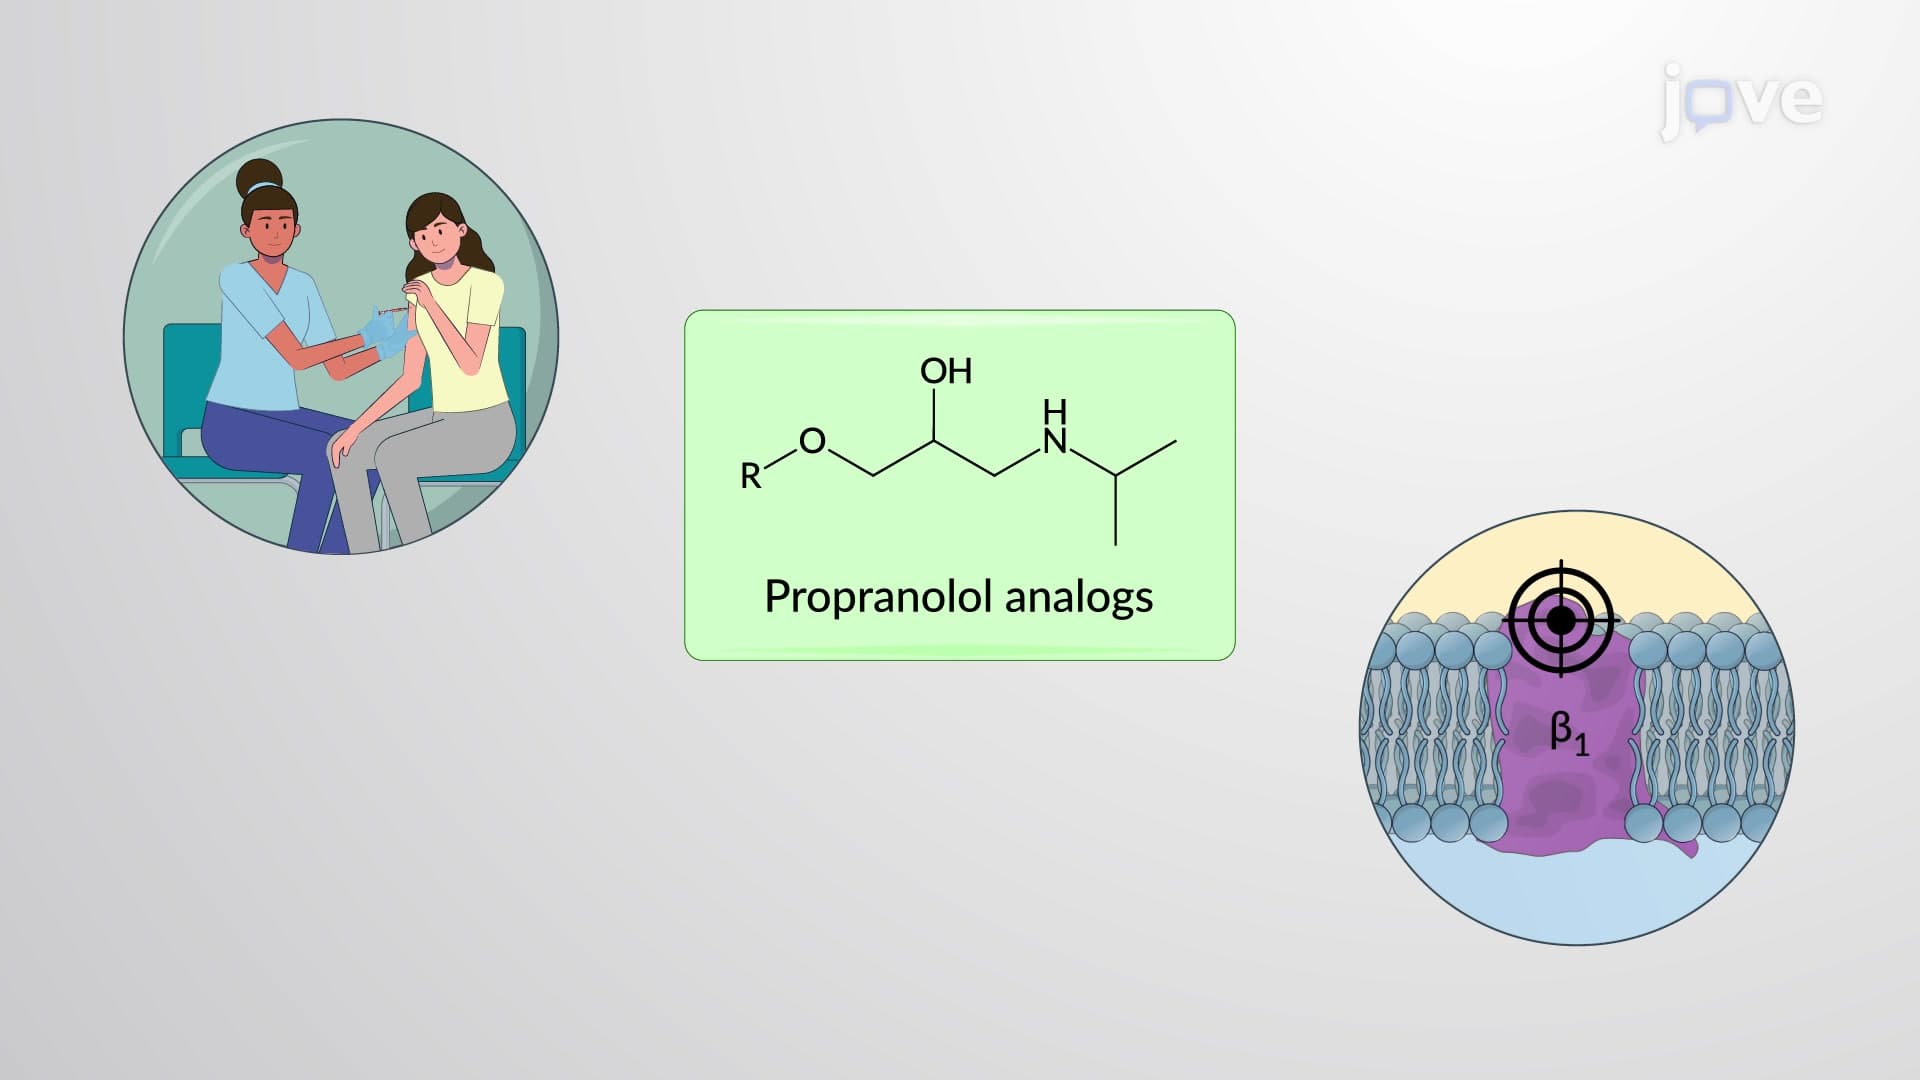 01:25
Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers