Ultrasound-diagnosed cardiac tamponade after blunt abdominal trauma-treated with emergent thoracotomy
Related Experiment Video
Updated: Jul 17, 2026
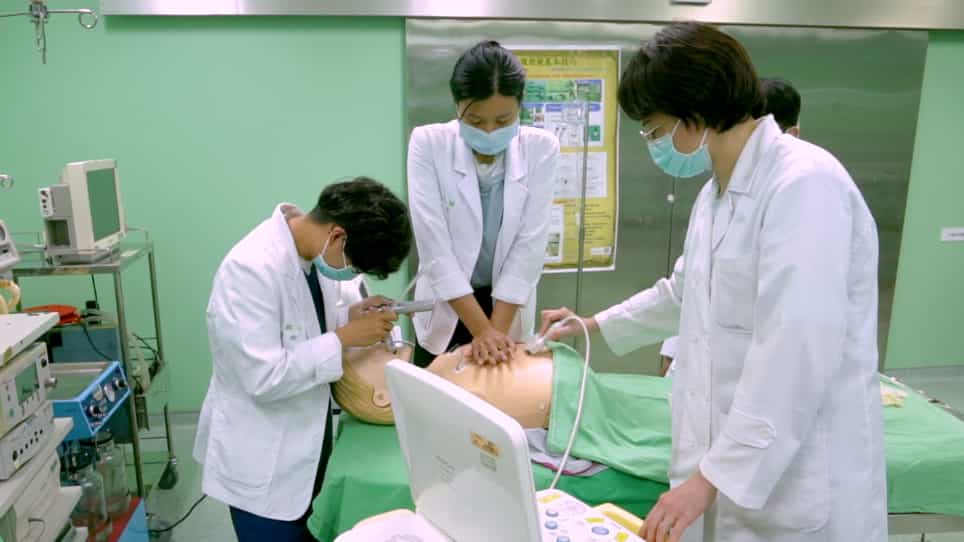
Ultrasonographic Assessment During Cardiopulmonary Resuscitation
Published on: October 24, 2020
Jay Menaker1, Jeremy Cushman, Jon Mark Vermillion
1R. Adams Cowley Shock Trauma Center, University of Maryland School of Medicine, Baltimore, Maryland, USA.

Abstract:
Ultrasound imaging enhances the physician's ability to evaluate, diagnose, and treat emergency department (ED) patients. Because ultrasound imaging is often time-dependent in the acutely ill or injured patient, the emergency physician is in an ideal position to use this technology. Focused ultrasound examinations provide immediate information and can answer specific questions about the patient's physical condition. We report a case in which blunt trauma to the abdomen and pre-existing pericardial fluid, due to human immunodeficiency virus (HIV), caused pericardial tamponade, diagnosed by bedside ultrasonography, and subsequent cardiac arrest. An ED thoracotomy released this tamponade, and spontaneous cardiac activity returned. The indications for and efficacy of ED thoracotomy have been debated for many years. Multiple studies have shown that patients with isolated penetrating chest trauma have the best outcome and that patients with blunt trauma without signs of life at the scene or in the ED have the poorest. We demonstrate the importance of ultrasound use by emergency physicians to assess trauma patients with pulseless electrical activity and suggest that in specific clinical situations after blunt trauma, an ED thoracotomy can be life saving.

Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care