Related Experiment Video
Updated: Jul 17, 2026
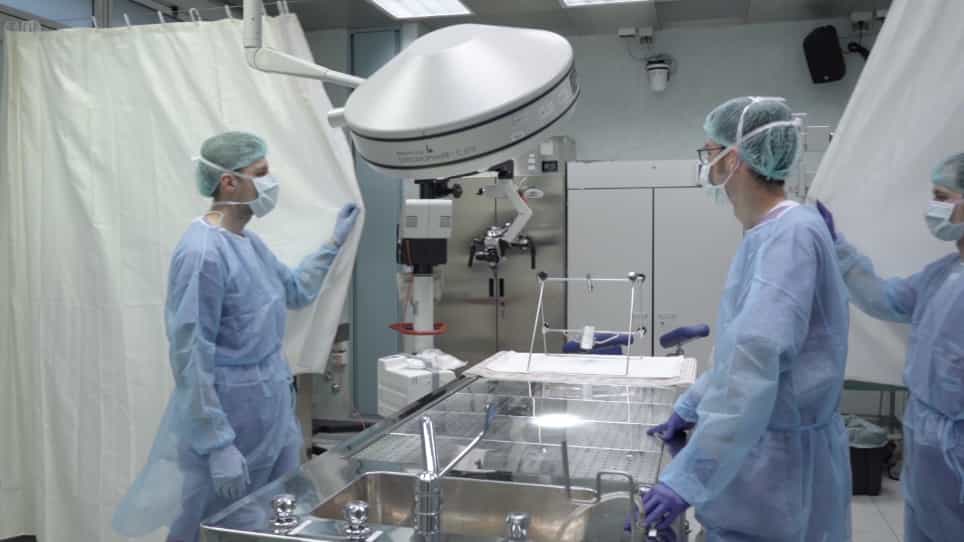

Learning Modern Laryngeal Surgery in a Dissection Laboratory
Published on: March 18, 2020
Laryngeal cancer at the korle bu teaching hospital accra ghana
Ed Kitcher1, J Yarney, Rk Gyasi
1Department of Surgery University of Ghana Medical School, P O Box 4236 Accra.

Summary Introduction:
Laryngeal cancer is the commonest Head and Neck cancer seen at the Ear Nose and Throat (ENT) Unit Korle-Bu Teaching Hospital. The aim of this study was to determine the number of cases of laryngeal cancer seen at the Korle Bu Teaching Hospital, establish epidemiological parameters of the disease and to outline preventive measures.
Method:
One hundred and fifteen (115) patients who were managed for laryngeal cancer from 1(st) January 1998 to 31(st) December 2003 were studied retrospectively with respect to age, sex, duration of symptoms at presentation, risk factors, symptoms complex, histopathology, stage of tumor, details of treatment offered and follow up.
Results:
The age range was 17-85 years with a mean of 55.5 years (SD10.7). Majority of the patients (90.4%) were above 40 years. The commonest symptom at presentation was dysphonia. A significant proportion of cases (37.3%) presented with locally advanced disease. The commonest histological type of laryngeal tumour seen was squamous cell carcinoma. The treatment offered consisted of radiotherapy for 83 (79.8%) patients and total laryngectomy with neck dissection when necessary for 17 (16.3%) patients who also had postoperative radiotherapy. Only 58 (69.9%) patients completed radiotherapy treatment and in all 32 (24.3 %) patients did not report for any treatment. Majority of patients failed to report for post treatment follow up.
Conclusions:
We conclude that significant number of patients with laryngeal cancer presented with locally advanced disease and dysphonia was the commonest symptom.
Related Concept Videos
 01:21
Larynx
Anatomy of the Larynx
The larynx consists of various components, including cartilage, muscles, and vocal cords. Its structure includes three large unpaired cartilages—the thyroid, cricoid, and epiglottis—and three smaller paired cartilages—the arytenoids, corniculates, and...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:27
Esophageal Achalasia
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...