Related Experiment Video
Updated: Jul 16, 2026


Following in Real Time the Impact of Pneumococcal Virulence Factors in an Acute Mouse Pneumonia Model Using Bioluminescent Bacteria
Published on: February 23, 2014
A worldwide perspective of atypical pathogens in community-acquired pneumonia
Forest W Arnold1, James T Summersgill, Andrew S Lajoie
1Division of Infectious Diseases, University of Louisville, Louisville, KY 40292, USA. f.arnold@louisville.edu

Rationale:
Controversy still exists in the international literature regarding the need to use antimicrobials covering atypical pathogens when initially treating hospitalized patients with community-acquired pneumonia (CAP). In different regions of the world, monotherapy with a beta-lactam antimicrobial is common.
Objectives:
We sought to correlate the incidence of CAP due to atypical pathogens in different regions of the world with the proportion of patients treated with an atypical regimen in those same regions. In addition, we sought to compare clinical outcomes of patients with CAP treated with and without atypical coverage.
Methods:
A secondary analysis was performed using two comprehensive international databases. World regions were defined as North America (I), Europe (II), Latin America (III), and Asia and Africa (IV). Time to reach clinical stability, length of hospital stay, and mortality were compared between patients treated with and without atypical coverage.
Measurements And Main Results:
The incidence of CAP due to atypical pathogens from 4,337 patients was 22, 28, 21, and 20% in regions I-IV, respectively. The proportion of patients treated with atypical coverage from 2,208 patients was 91, 74, 53, and 10% in regions I-IV, respectively. Patients treated with atypical coverage had decreased time to clinical stability (3.7 vs. 3.2 d, p < 0.001), decreased length of stay (7.1 vs. 6.1 d, p < 0.01), decreased total mortality (11.1 vs. 7%, p < 0.01), and decreased CAP-related mortality (6.4 vs. 3.8%, p = 0.05).
Conclusions:
The significant global presence of atypical pathogens and the better outcomes associated with antimicrobial regimens with atypical coverage support empiric therapy for all hospitalized patients with CAP with a regimen that covers atypical pathogens.
Insights
Empiric treatment for community-acquired pneumonia (CAP) should include atypical pathogen coverage. This approach improves clinical outcomes, reduces hospital stays, and lowers mortality rates in hospitalized patients with CAP.
Area of Science:
- Infectious Diseases
- Pharmacology
- Public Health
Background:
- International guidelines debate the necessity of atypical pathogen coverage in community-acquired pneumonia (CAP) treatment.
- Monotherapy with beta-lactam antimicrobials is a common initial approach in many global regions.
Purpose of the Study:
- To correlate the global incidence of atypical pathogens in CAP with regional treatment patterns.
- To compare clinical outcomes for CAP patients receiving atypical pathogen coverage versus those who did not.
Main Methods:
- Secondary analysis of two international databases.
- Categorization of world regions into North America, Europe, Latin America, and Asia/Africa.
- Comparison of time to clinical stability, hospital length of stay, and mortality rates.
Main Results:
- Atypical pathogens were present in 20-28% of CAP cases across regions.
- Atypical coverage varied significantly by region (10-91%).
- Patients receiving atypical coverage showed improved clinical stability, shorter hospital stays, and reduced mortality.
Conclusions:
- Atypical pathogens are globally prevalent in CAP.
- Antimicrobial regimens including atypical coverage are associated with better patient outcomes.
- Empiric CAP therapy should incorporate atypical pathogen coverage for all hospitalized patients.

Related Concept Videos
 01:14
Atypical Pneumonia
 01:29
Pneumonia I: Introduction
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:29
Pneumonia II: Pathophysiology
 01:30
Pneumonia III: Complications and Assessment
 01:29
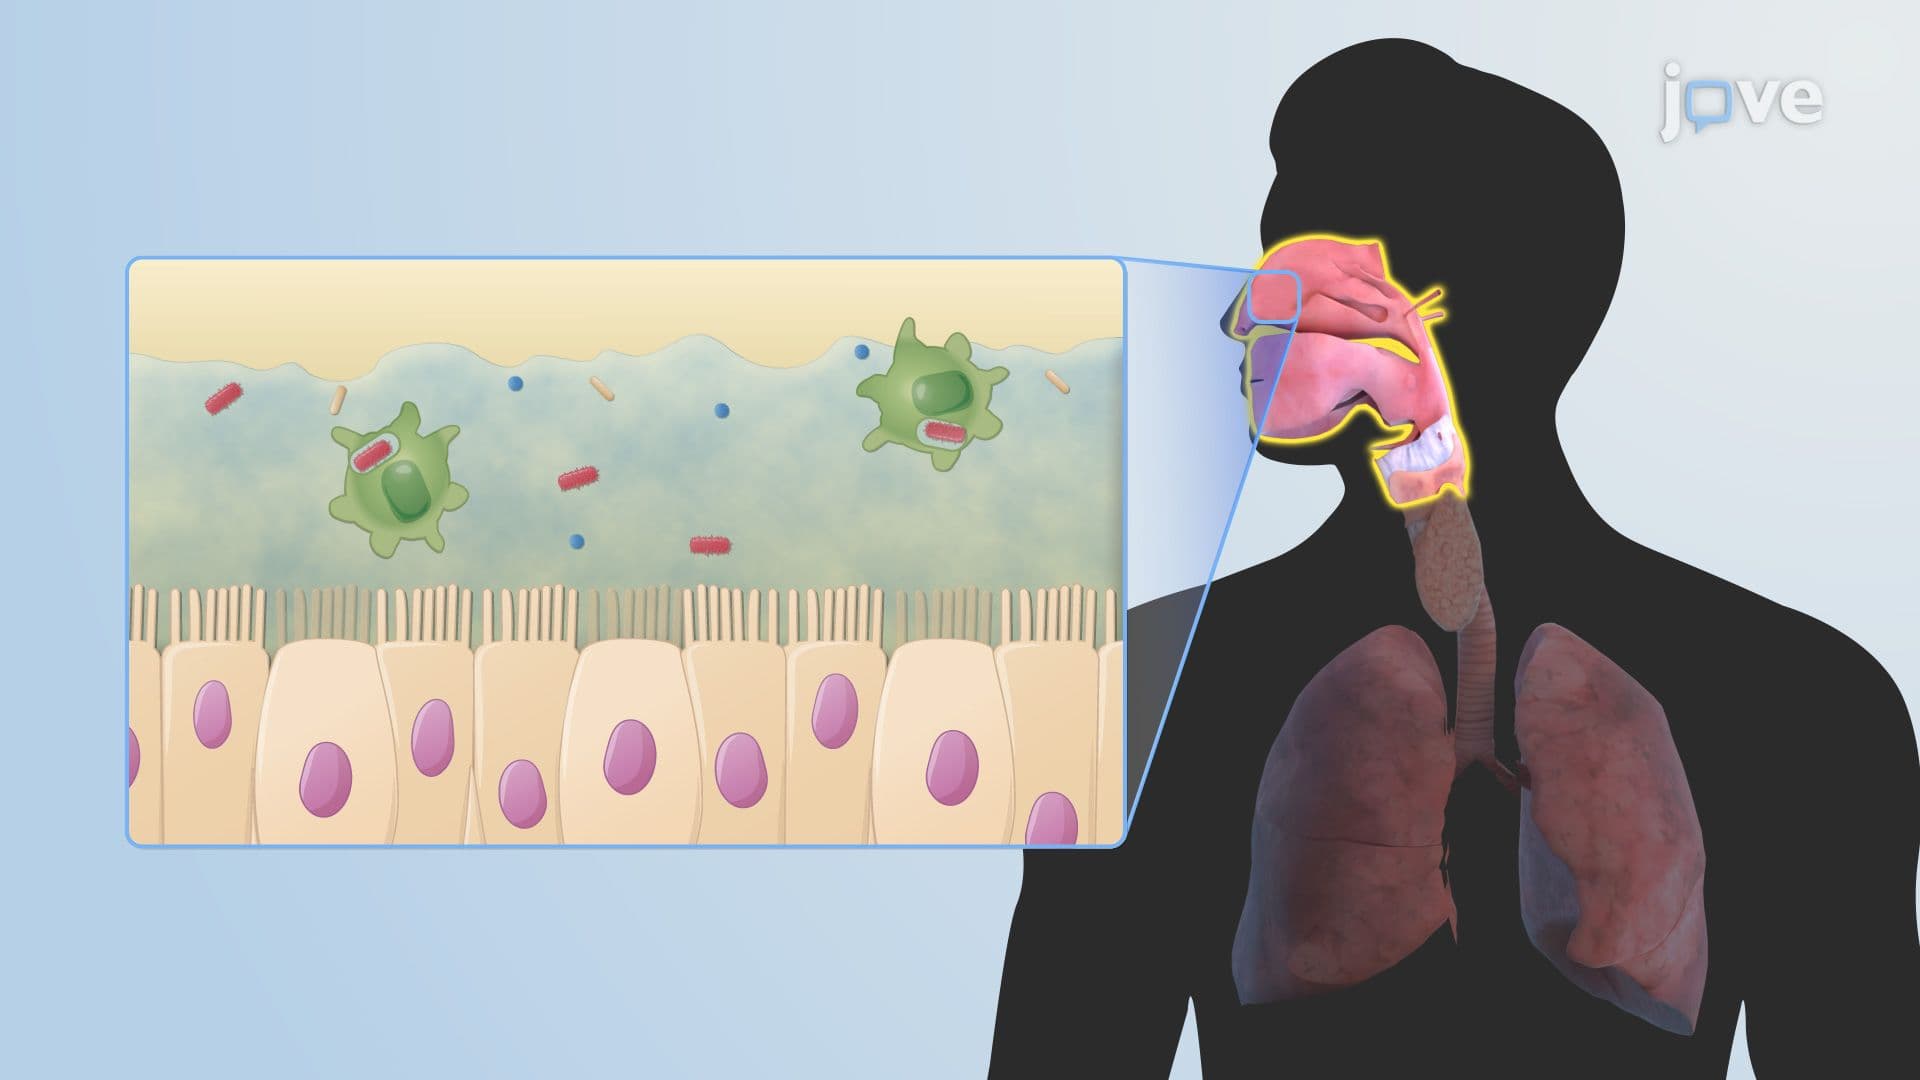
Microbiota of the Respiratory Tract