Related Experiment Video
Updated: Jul 16, 2026
Synergizing Antegrade Endoscopic with Bridging Vein Harvesting for Improvement of Great Saphenous Vein Graft Quality from the Lower Leg
Published on: November 19, 2019
[Preservation of the saphenous vein during inguinal lymphadenectomy for vulval malignancies]
Xiao-Ling Zhang1, Xiu-Gui Sheng, Hui-Qin Li
1Department of Gynecologic Oncology, Shandong Provincial Cancer Hospital, Jinan, Shandong, 250117, P. R. China. 13608921932@jnmobile.com.

Background & Objective:
The conventional operation for the patients with vulval malignancies is radical vulvectomy and bilateral inguinal lymphadenectomy with partial saphenous vein trunk ligation and resection, but the quality of life of the patients was declined severely because of multiple postoperative complications. This study was to explore the influences of preserving the saphenous vein during inguinal lymphadenectomy for vulval malignancies on operation, prognosis, and complications.
Methods:
A total of 64 patients with vulval malignancies, treated in Shandong Provincial Cancer Hospital from Jan. 1989 to Dec. 2005, were divided into 2 groups: the saphenous vein was preserved in 31 patients and ligated in 33 patients during inguinal lymphadenectomy. The operating time, intraoperative blood loss, 5-year survival rate, recurrence rate, and complications were compared between the 2 groups.
Results:
The median operating time of bilateral inguinal lymphadenectomy was 155 min (130-170 min) in preservation group, and 140 min (120-170 min) in ligation group (P>0.05). The median intraoperative blood loss was 295 ml (100-450 ml) in preservation group, and 270 ml (150-390 ml) in ligation group (P>0.05). The 5-year overall survival rate was 67.3%û it was 68.0% in preservation group and 66.7% in ligation group (P>0.05). Till Mar. 2006, 5 sides of inguinal lymph nodes relapsed in 3 patients in preservation group, and 7 sides in 5 patients in ligation group; the recurrence rates were 8.9% (5/56), and 12.1% (7/58) (P>0.05). The occurrence rates of acute low extremity lymph edema, low extremity phlebitis, chronic low extremity edema, and chronic leg pain were significantly lower in preservation group than in ligation group (11.3% vs. 25.8%, P<0.05; 43.5% vs. 66.7%, P<0.01; 25.0% vs. 48.3%, P<0.01; 23.2% vs. 46.6%, P<0.01); the occurrence of leg cellulitis and sense abnormity were also less in preservation group than in ligation group (P<0.05).
Conclusions:
Preserving the saphenous vein trunk during inguinal lymphadenectomy for vulval malignancies reduces multiple postoperative complications without compromising treatment outcome. This modified operative modality is valuable to be recommended.
Related Concept Videos
 01:18
Veins of the Abdomen and Pelvis
The inferior vena cava is fed by numerous smaller veins. The lumbar veins, for instance, drain the posterior abdominal wall, emptying both directly into the inferior vena cava and into the...
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:15
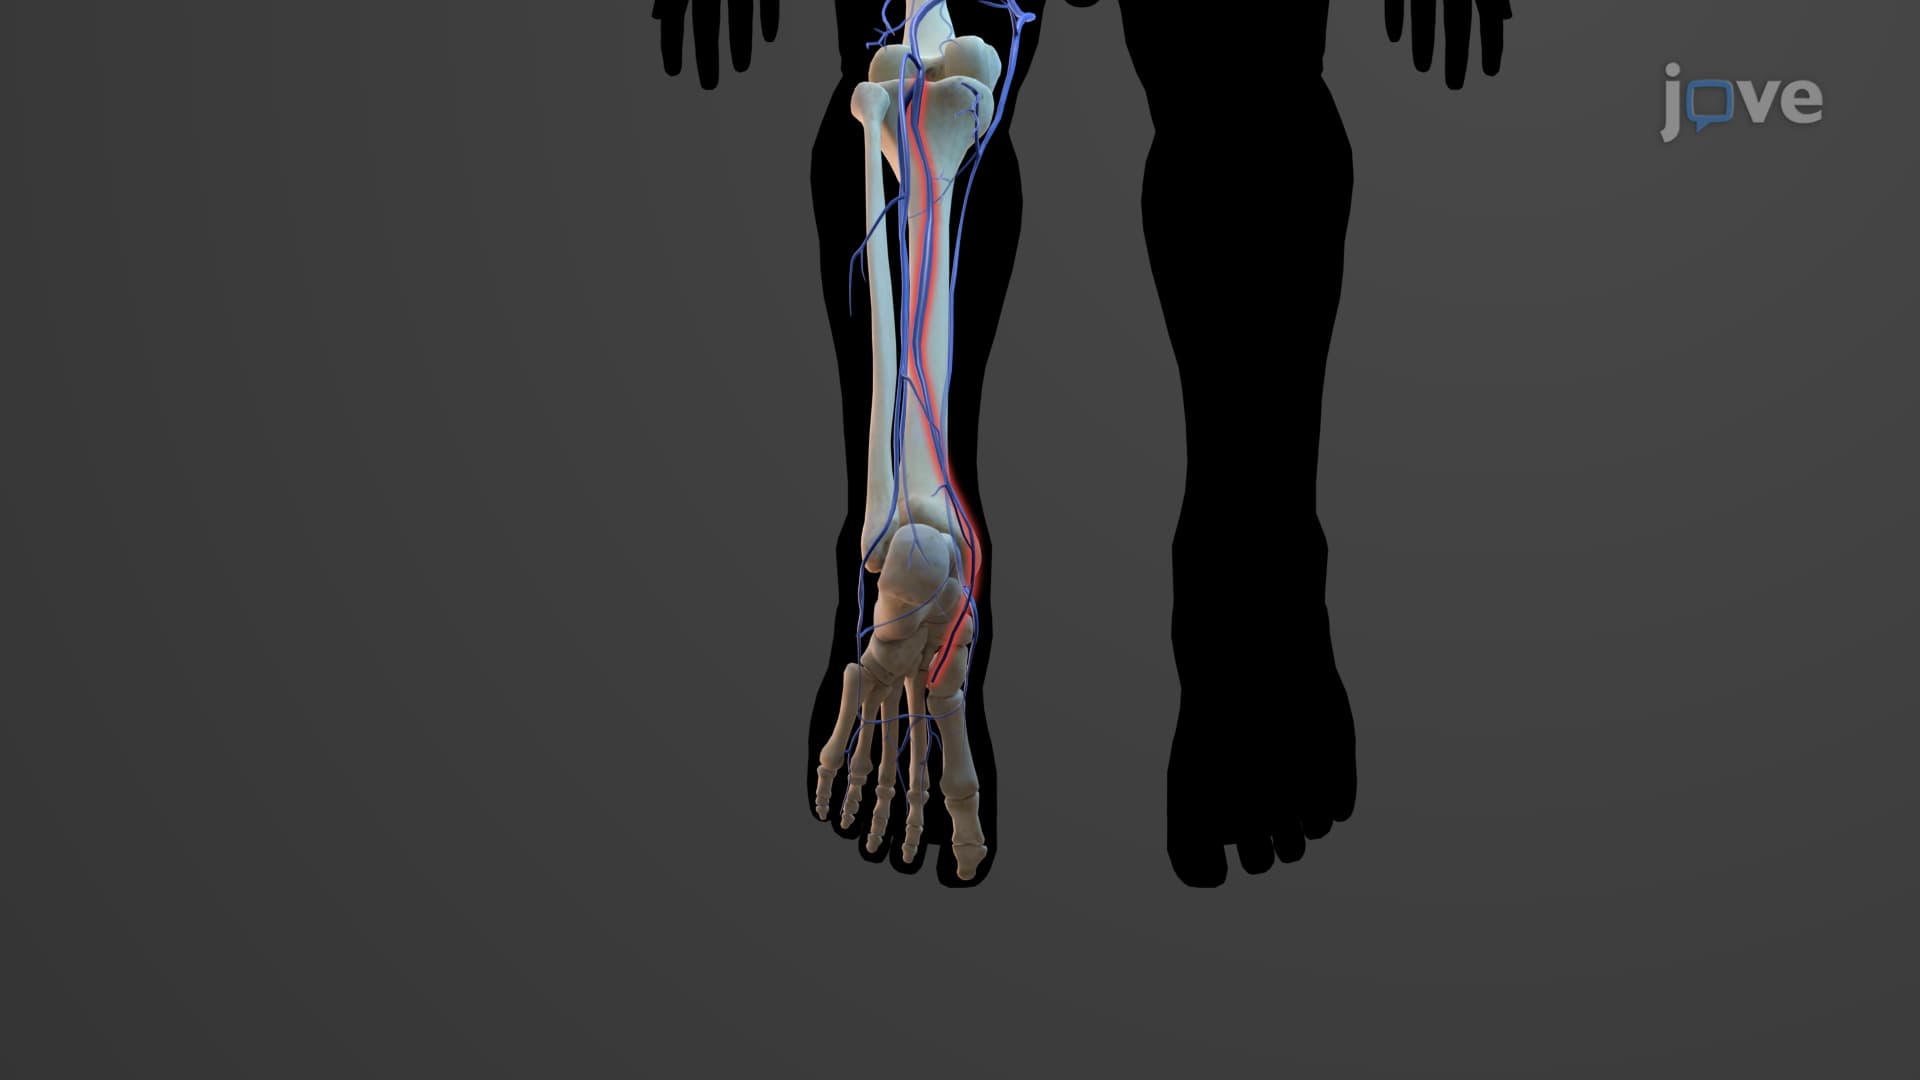
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the knee,...
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:15
Development of the Lymphatic System
The first lymph sacs to form are the paired jugular lymph sacs located at the junction of the internal jugular and subclavian veins. From these sacs, lymphatic capillary plexuses extend to the thorax, upper limbs, neck, and head, eventually forming lymphatic vessels. Each jugular lymph sac maintains a...
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies