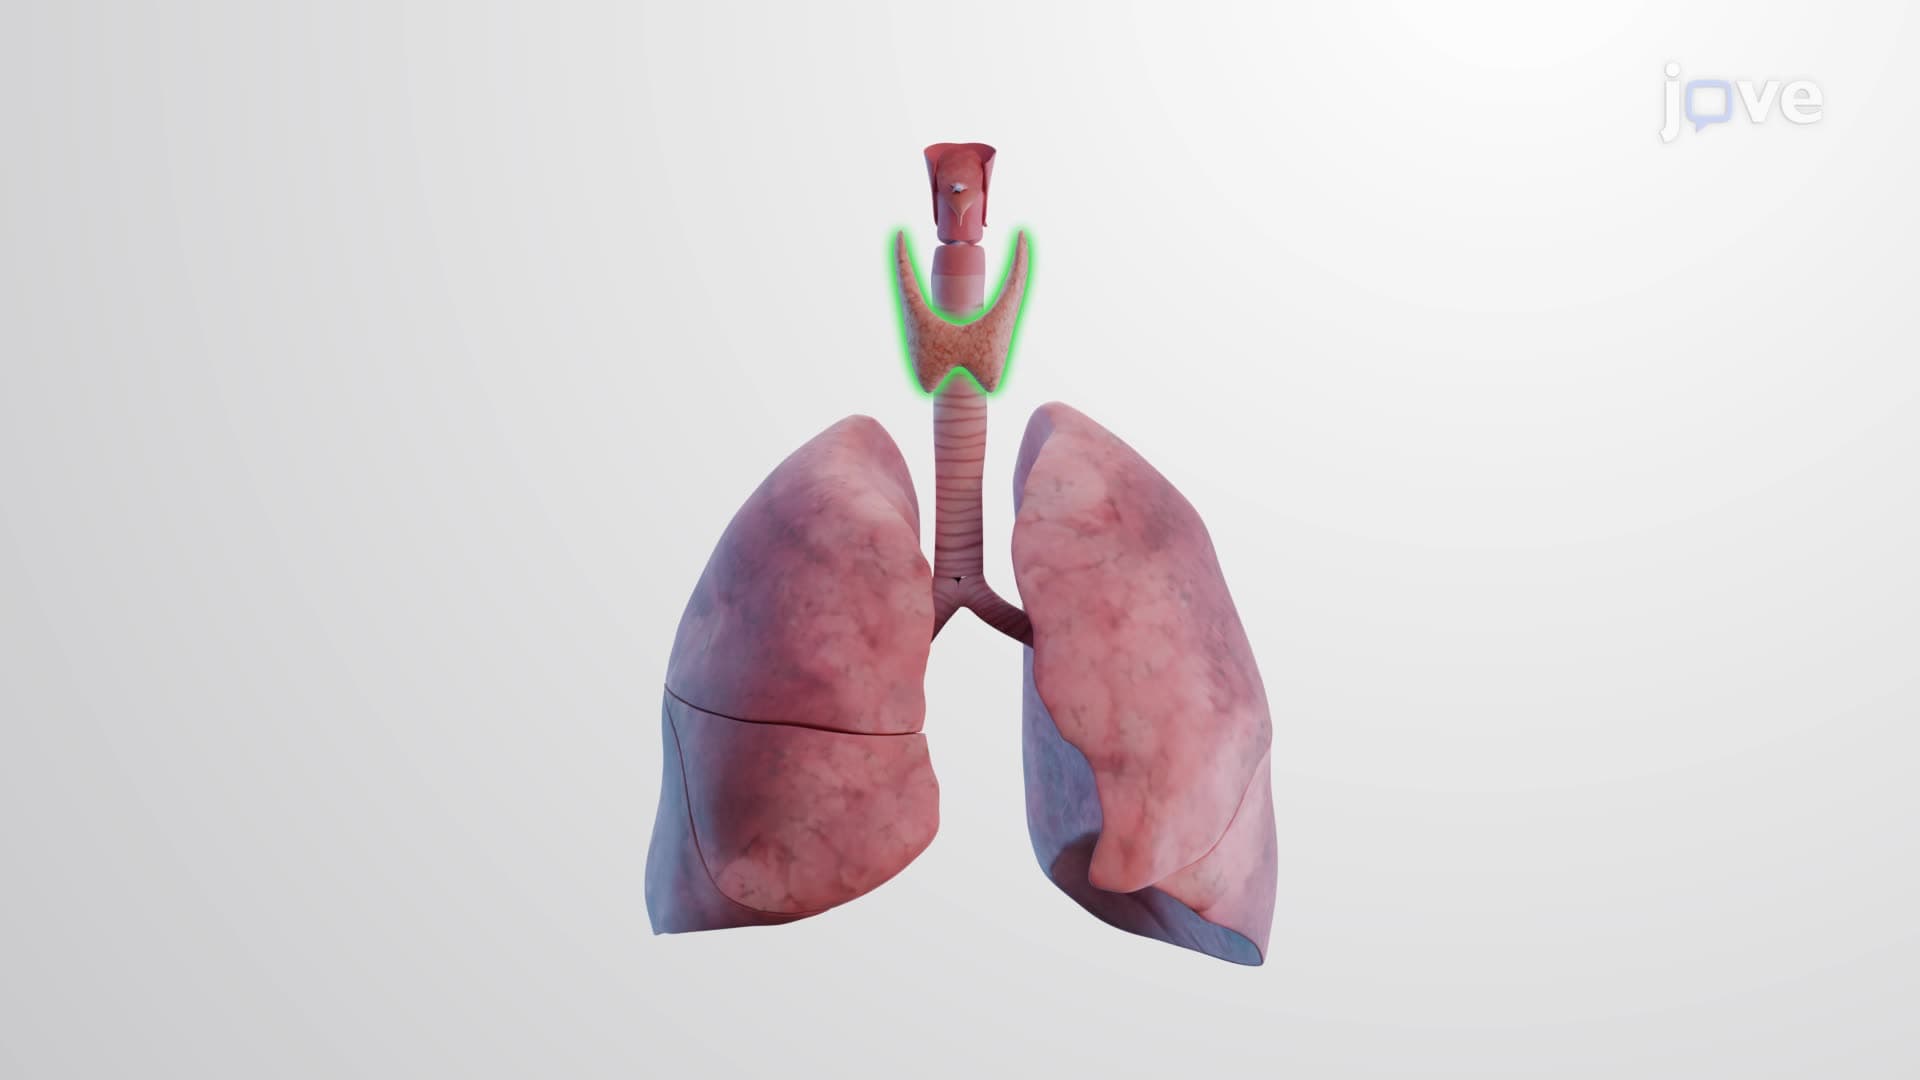
Intraoperative diagnosis and treatment of parathyroid cancer and atypical parathyroid adenoma
Related Experiment Video
Updated: Jul 16, 2026
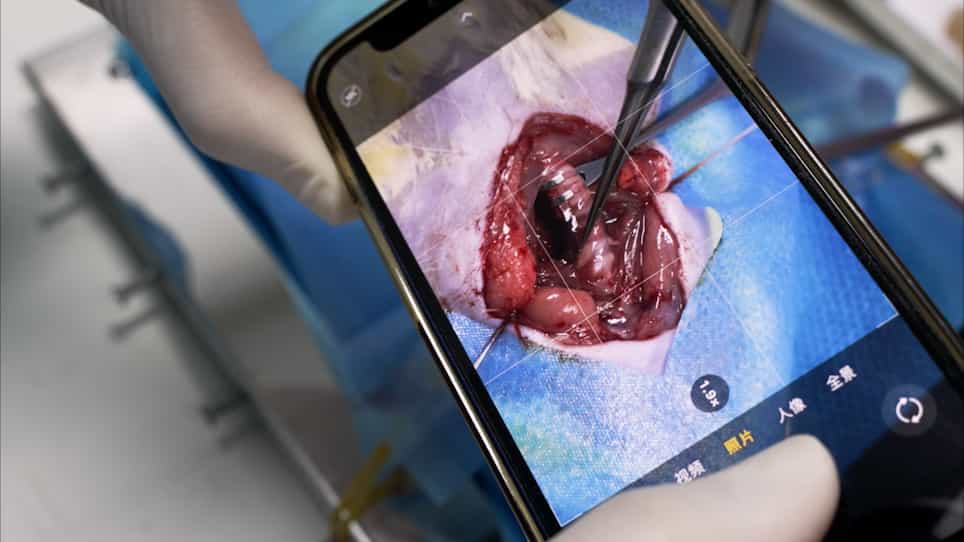
Establishment of a Simple and Effective Rat Model for Intraoperative Parathyroid Gland Imaging
Published on: August 17, 2022
G Ippolito1, F F Palazzo, F Sebag
1Department of Endocrine Surgery, La Timone University Hospital, Marseilles, France.

Background:
Distinction of parathyroid cancer from atypical parathyroid adenoma (APA) at operation is difficult. The aim of this study was to determine whether parathyroid cancer and APA have different operative findings and long-term outcomes.
Methods:
A retrospective review was undertaken of patients with suspicious or malignant parathyroid tumours treated between 1974 and 2005. Parathyroid cancer was defined as a lesion with vascular or tissue invasion, and APA as a neoplasm with broad fibrous bands, trabecular growth, mitosis and nuclear atypia.
Results:
Twenty-seven patients with suspicious or malignant parathyroid tumours were identified. After histological review, parathyroid cancer was confirmed in 11 patients (group 1) and 16 tumours were classified as APA (group 2). The clinical presentation and operative findings of the two types of tumour were indistinguishable. At initial surgery, seven patients in group 1 underwent en bloc resection, and four had parathyroidectomy. Four of the seven patients who had en bloc resection had recurrences. No recurrences were observed in the other seven patients in group 1 at a median follow-up of 65 months. In group 2, eight patients had en bloc resection and eight had parathyroidectomy; no patient had recurrence at a median follow-up of 91 months.
Conclusion:
Operative findings cannot distinguish APA from parathyroid cancer reliably. Without evidence of macroscopic local invasion, the value of en bloc resection at initial surgery remains debatable.