Related Experiment Video
Updated: Jul 15, 2026

Generation of Recombinant Arenavirus for Vaccine Development in FDA-Approved Vero Cells
Published on: August 1, 2013
Hemorrhagic fevers: few clues after 25 years
P L Petit1, B K Johnson, J Hermans
1Department of Microbiology, Schieland Hospital, Burg. Knappertlaan 25, 3116 BA Schiedam, The Netherlands.

Abstract:
There is a high prevalence of Ebola antibodies found in the Kenya population, related to geographical area and season, although the clinical disease was never found and the virus was not isolated. A field study was carried out in 7 hospitals in western Kenya, 1986 -1987 (including surveillance studies in suspect areas), to intensify collection and transport of samples, testing facilities, patient observation with record keeping and follow-up. This study involved 1109 admitted patients with fever and/or bleeding, 155 contacts of haemorrahagic fever antibody (Hfab) patients, and 916 people in suspect areas. Respectively 160,44 and 80 persons were found Hfab positive mainly to Ebola, using an indirect immunofluorescent assay. From 676 viral cultures no virus was isolated. A relationship between antibody titres and ecological factors, social habitat, age, sex or season was not found. The non-specificity of IF testing was demonstrated by: 1) the disagreement between the results of two reference laboratories; 2) the unpredictability of the titre conversation course; and 3) by proving a significant cross-reactivity with Borrelia burgdorferii antibodies, Plasmodium falcparum antibodies and Salmonella typhi antibodies. Renewed testing in 1995 of 90 positive sera (with low titres) showed 19 sera to be positive by Elisa (2 in Zaire, 1 in Sudan, 9 in Reston and 7 in Cote d'Ivoire) from which 4 were confirmed by IFI 2 in Reston and 2 in Cote d'Ivoire. These findings are more proof that non-human virulent strains of Filoviridae, especially Ebola virus, are around in Kenya.

Related Concept Videos
 01:18
Yellow Fever
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:25
Hepatitis
 01:26
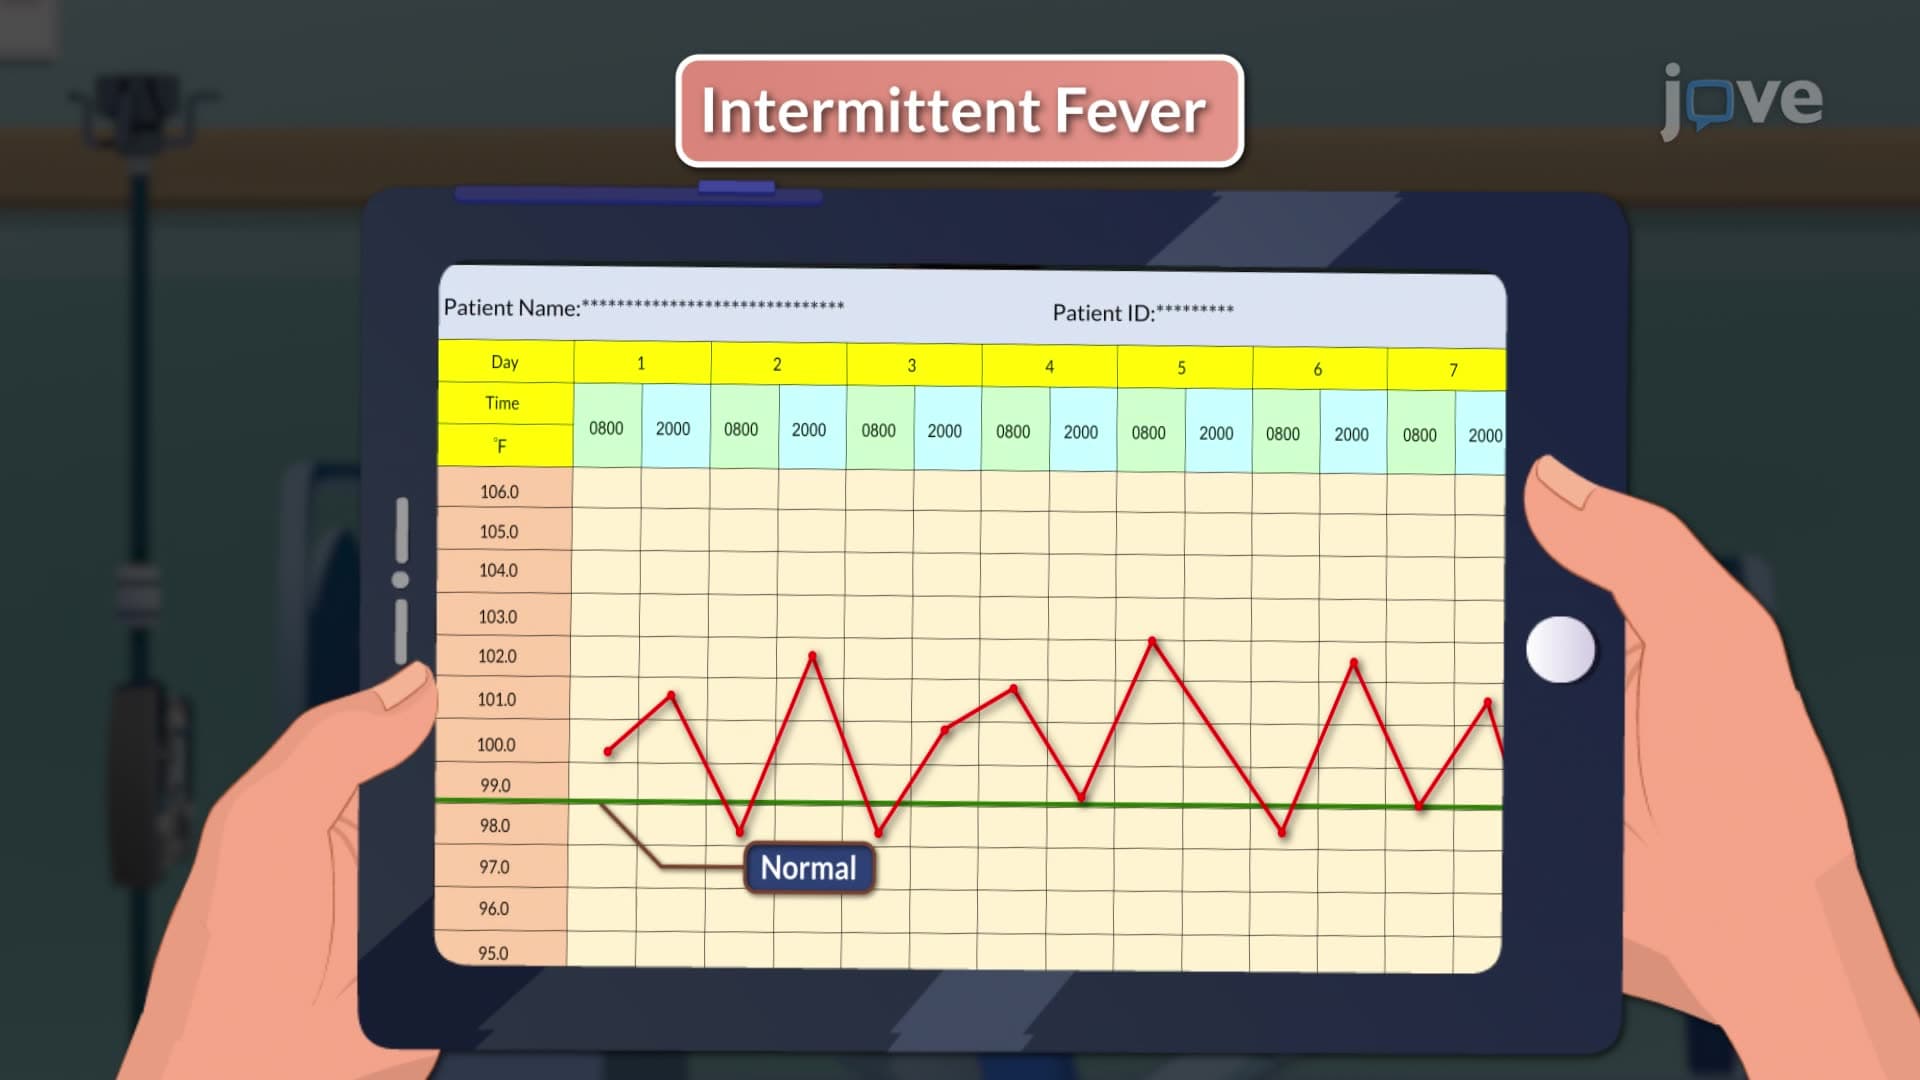
Patterns of Fever