Related Experiment Video
Updated: Jul 15, 2026
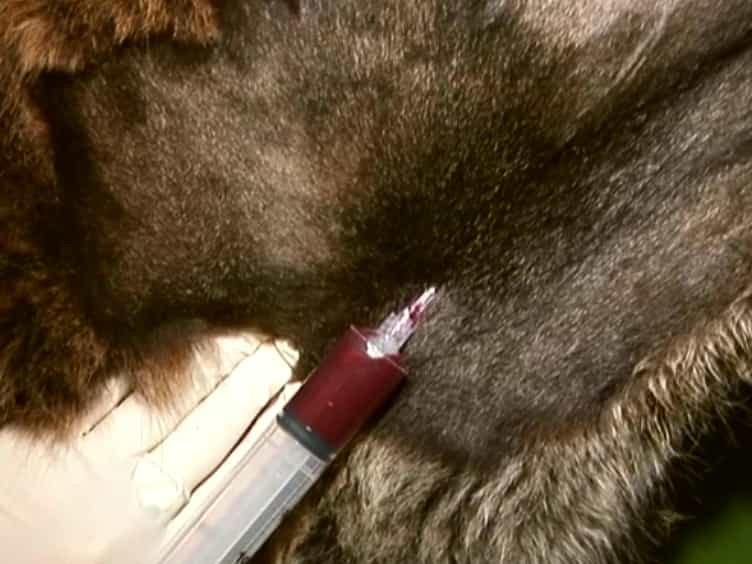

Application of Long-term cultured Interferon-γ Enzyme-linked Immunospot Assay for Assessing Effector and Memory T Cell Responses in Cattle
Published on: July 11, 2015
[Latent tuberculosis infection in healthcare workers--evaluation of an Interferon-gamma release assay]
A Nienhaus1, R Loddenkemper, B Hauer
1Berufsgenossenschaft für Gesundheitsdienst und Wohlfahrtspflege, Hamburg. albert.nienhaus@bgw-online.de

Introduction:
The Interferon-gamma release assay (IGRA) is a promising alternative to the tuberculin skin test (TST) for the diagnosis of latent tuberculosis infection (LTBI). But so far only limited experience is available regarding the performance of these IGRAs especially in occupational medicine when used for screening healthcare workers (HCW).
Method:
In an ongoing study employees of three German hospitals are screened for LTBI using the TST Mendel-Mantoux and the IGRA (QuantiFERON-TB Gold in Tube) simultaneously. Information on earlier tests which had been performed with the multipuncture tests were obtained by interview. Risk factors for a positive test result were calculated using multivariate logistic regression.
Results:
The analysis comprises 161 employees for whom information on all the tests - multipuncture test, TST Mendel-Mantoux and IGRA were available. The multipuncture test was positive in 34.8 %, the TST Mendel-Mantoux in 26.7 % and the IGRA in 12.4 % of the participants. When adjusting for the proportion of positive test results caused by cross-reaction with BCG vaccination, the prevalence of LTBI reduces to 18.8 % in the multipuncture test and 19.2 % in the TST Mendel-Mantoux. The Test results of the IGRA were positively correlated with age while the results of the two in-vivo tests were not.
Discussion:
The multipuncture test and the TST Mendel-Mantoux overestimate the prevalence of LTBI in HCW. A positive result in the TST should be verified by the IGRA before any further actions are recommended. A larger data base is needed in order to confirm that the IGRA is more sensitive in diagnosing a LTBI than the skin tests.
Related Concept Videos
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...