Related Experiment Video
Updated: Sep 3, 2026

Two Techniques to Create Hypoparathyroid Mice: Parathyroidectomy Using GFP Glands and Diphtheria-Toxin-Mediated Parathyroid Ablation
Published on: March 14, 2017
Primary hyperparathyroidism during pregnancy
1Department of Surgery, Northeastern Ohio Universities College of Medicine, Akron City Hospital 44304.

Historically, primary hyperparathyroidism during pregnancy was associated with significant risk of maternal morbidity and fetal death. Maternal hypercalcemia results in fetal hypercalcemia, leading to suppression of fetal parathyroid gland function. Neonatal hypocalcemia with tetany is a common occurrence after birth when maternal calcium flow is interrupted. From 1930 to 1990, 109 cases of women with primary hyperparathyroidism associated with pregnancy have been reported, 39 of whom were treated surgically before delivery. Although fetal mortality rates for medically treated women have improved, fetal morbidity continues to remain higher than in women who undergo surgical treatment of parathyroid disease during pregnancy. Of 850 patients treated surgically for primary hyperparathyroidism since 1960, 12 were pregnant. Four of the patients were treated medically during pregnancy and underwent surgery after delivery; all four infants had neonatal hypocalcemia and tetany. The remaining eight patients were treated surgically during pregnancy: six in the second trimester and two (one with associated pancreatitis and one with hypercalcemic crisis) during the first trimester. There was no fetal or maternal morbidity or death in the surgical group. Parathyroid adenomas were present in 10 of the patients, hyperplasia in one, and parathyroid carcinoma in one. The management of maternal primary hyperparathyroidism diagnosed during pregnancy should be based on the patient's symptoms and severity of disease. Hyperparathyroidism characterized by progressive symptoms should be treated surgically, preferably during the second trimester. Symptom-free patients and those with mild hypercalcemia diagnosed in the third trimester may be managed medically, postponing operation until after delivery.
Historically, primary hyperparathyroidism during pregnancy was associated with significant risk of maternal morbidity and fetal death. Maternal hypercalcemia results in fetal hypercalcemia, leading to suppression of fetal parathyroid gland function. Neonatal hypocalcemia with tetany is a common occurrence after birth when maternal calcium flow is interrupted. From 1930 to 1990, 109 cases of women with primary hyperparathyroidism associated with pregnancy have been reported, 39 of whom were treated surgically before delivery. Although fetal mortality rates for medically treated women have improved, fetal morbidity continues to remain higher than in women who undergo surgical treatment of parathyroid disease during pregnancy. Of 850 patients treated surgically for primary hyperparathyroidism since 1960, 12 were pregnant. Four of the patients were treated medically during pregnancy and underwent surgery after delivery; all four infants had neonatal hypocalcemia and tetany. The remaining eight patients were treated surgically during pregnancy: six in the second trimester and two (one with associated pancreatitis and one with hypercalcemic crisis) during the first trimester. There was no fetal or maternal morbidity or death in the surgical group. Parathyroid adenomas were present in 10 of the patients, hyperplasia in one, and parathyroid carcinoma in one. The management of maternal primary hyperparathyroidism diagnosed during pregnancy should be based on the patient's symptoms and severity of disease. Hyperparathyroidism characterized by progressive symptoms should be treated surgically, preferably during the second trimester. Symptom-free patients and those with mild hypercalcemia diagnosed in the third trimester may be managed medically, postponing operation until after delivery.

Related Concept Videos
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:21
Skeleton and Calcium Homeostasis
 00:59
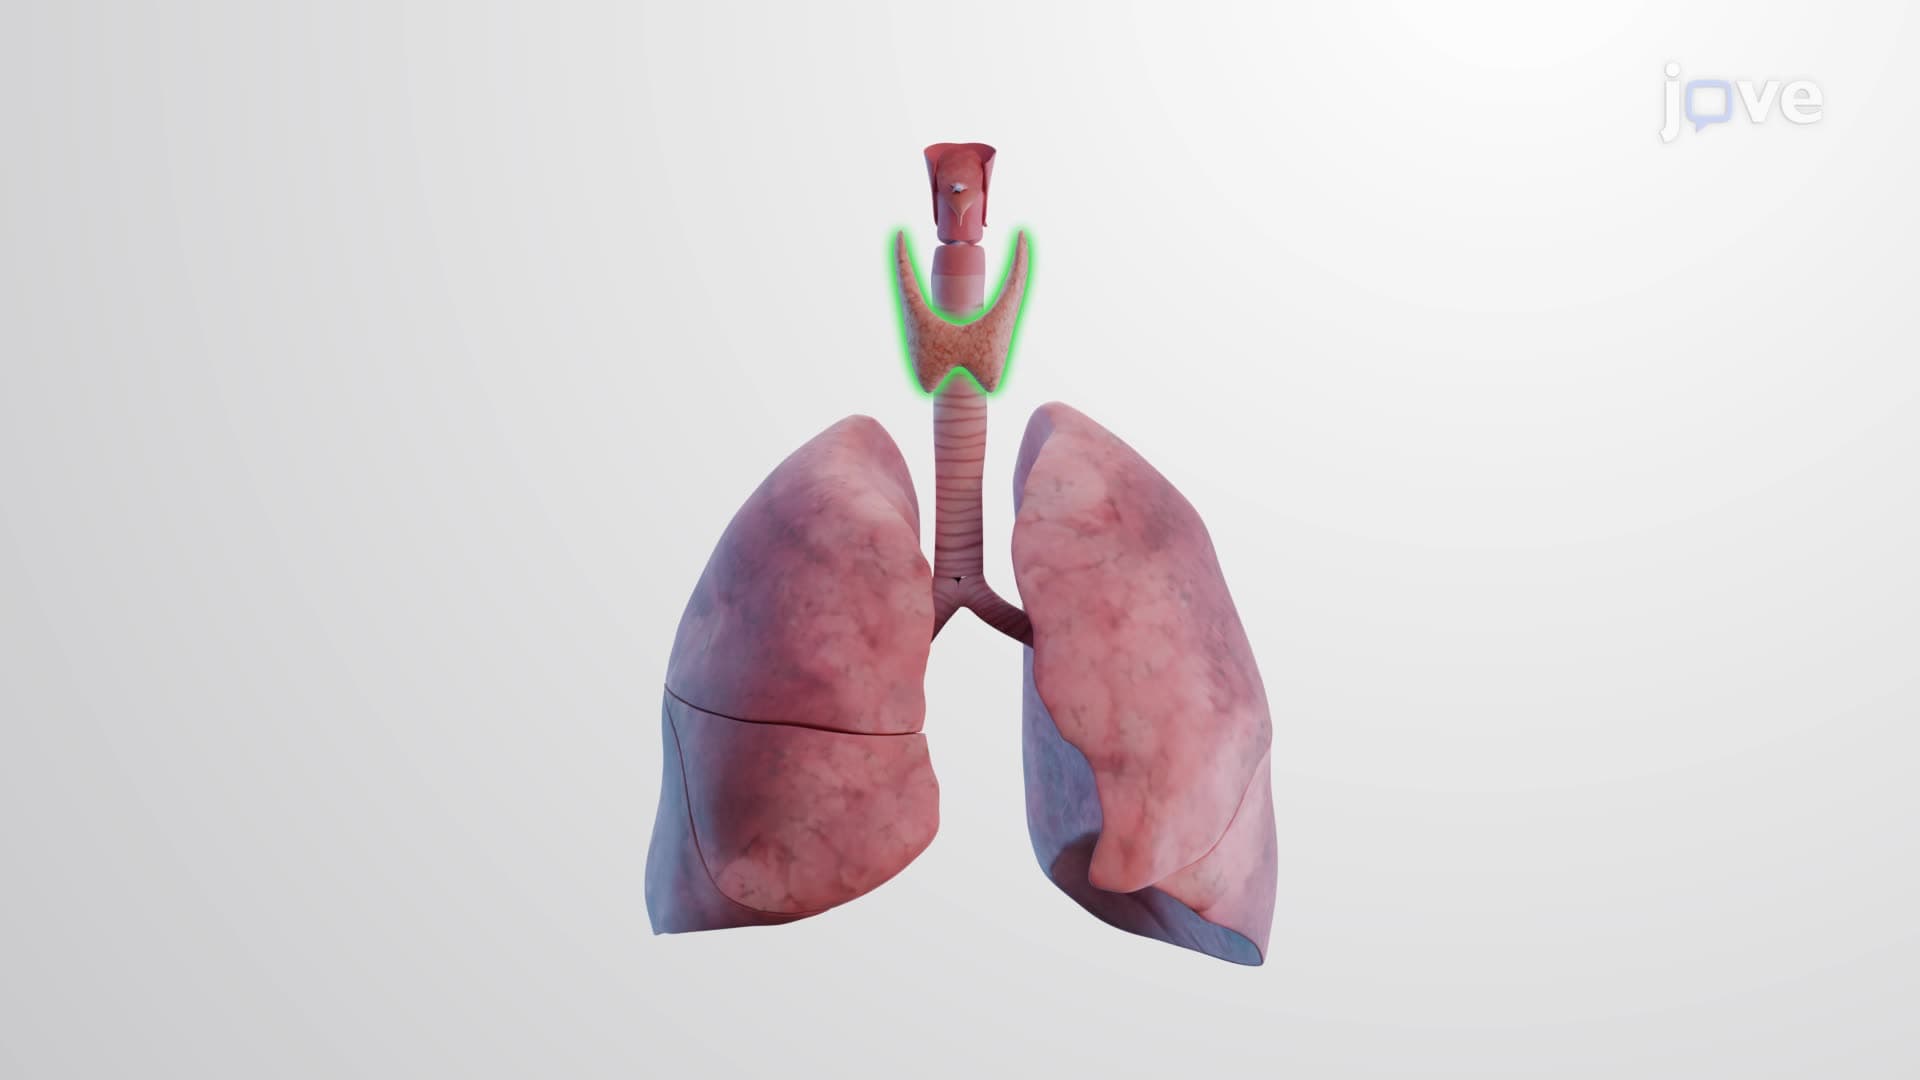
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:24
Graves Disease II: Pathophysiology