Related Experiment Video
Updated: Jul 15, 2026
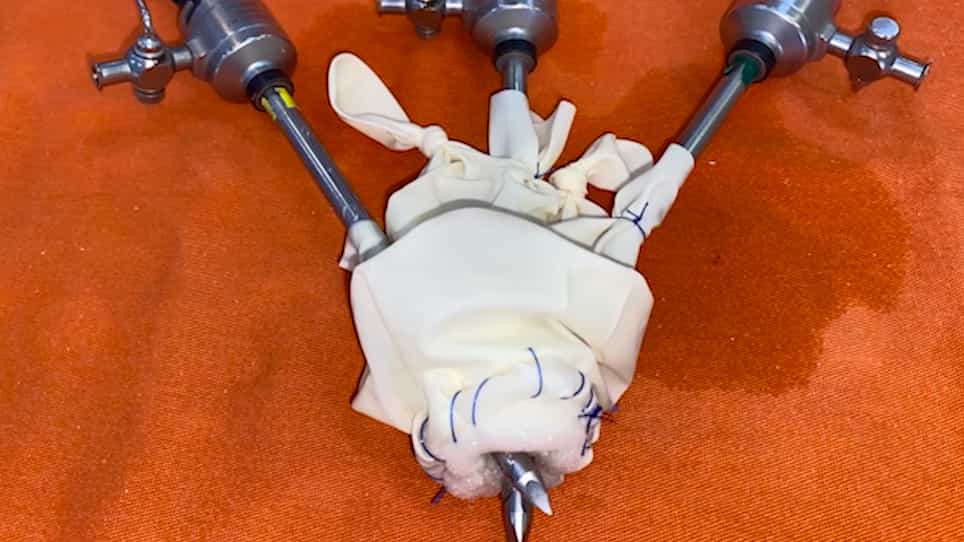

Low-Cost Single-Port (LoCoSP) Device for a Transcervical Approach in Minimally Invasive Transhiatal Esophagectomy
Published on: September 11, 2021
Upper mediastinal node dissection for hypopharyngeal and cervical esophageal carcinomas
Shigeru Hirano1, Kunihiko Nagahara, Sueyoshi Moritani
1Department of Otolaryngology-Head and Neck Surgery, Kyoto University Graduate School of Medicine, Sakyo-ku, Japan.

Objectives:
Hypopharyngeal cancer (HPC) and cervical esophageal cancer (Ce) are aggressive tumors with a poor prognosis. Multiple lymph node metastases often occur in the upper mediastinum, as well as in the neck, and thus upper mediastinal dissection (MD) is crucial to improving the cure rate. However, excessive MD can increase postoperative morbidity and mortality, making it important to employ the proper technique and appropriate extent of dissection. In the present retrospective study we aimed to determine the proper extent of upper MD according to tumor site and stage. The benefit and risk of upper MD are also discussed.
Methods:
Chart review was completed for patients who underwent upper MD, including 64 patients with HPC, 21 patients with Ce, and 9 patients with Ce extending to involve the upper thoracic esophagus (Ce/Ut). The incidence and distribution of lymph node metastases in the upper mediastinum were assessed by postoperative histopathologic examination. Postoperative complications of upper MD, as well as the impact on survival and locoregional control, were also reviewed.
Results:
Upper mediastinal metastases were detected in 7.8% of HPC patients, 33.3% of Ce patients, and 55.6% of Ce/Ut patients. In HPC patients, mediastinal metastases were usually associated with T4 primary tumors (80%), whereas positive nodes in the upper mediastinum were detected regardless of T stage in both Ce and Ce/Ut. Only 1 Ce/Ut patient with a T4 tumor developed late nodal metastasis in the lower mediastinum. The 5-year disease-specific survival and locoregional control rates were 58.6% and 90.2% in HPC, 45.5% and 94.1% in Ce, and 38.9% and 77.7% in Ce/Ut, respectively. Rupture of the greater vessels after MD was observed in 5 cases (5.3%).
Conclusions:
The present results indicate excellent locoregional control rates following upper MD, while major complications such as arterial breakdown were rare. It is suggested that upper MD may be an essential and adequate procedure for patients with Ce or Ce/Ut tumors, and may also be required for cases of HPC with a T4 primary to improve locoregional control of the disease.
Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:27
Esophageal Achalasia
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...