Related Experiment Video
Updated: Jul 14, 2026


Dual Test Gas Pulmonary Diffusing Capacity Measurement During Exercise in Humans Using the Single-Breath Method
Published on: February 2, 2024
Human cardiovascular dose-response to supplemental oxygen
1Department of Anesthesia and Intensive Care, and Departments of Hand and Plastic Surgery and Burn Intensive Care, University Hospital, Linköping, Sweden.

Aim:
The aim of the study was to examine the central and peripheral cardiovascular adaptation and its coupling during increasing levels of hyperoxaemia. We hypothesized a dose-related effect of hyperoxaemia on left ventricular performance and the vascular properties of the arterial tree.
Methods:
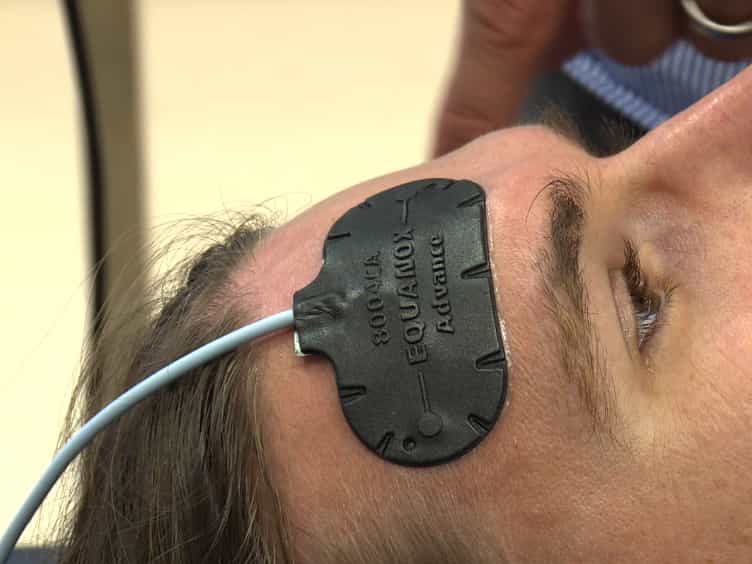
Oscillometrically calibrated arterial subclavian pulse trace data were combined with echocardiographic recordings to obtain non-invasive estimates of left ventricular volumes, aortic root pressure and flow data. For complementary vascular parameters and control purposes whole-body impedance cardiography was applied. In nine (seven males) supine, resting healthy volunteers, aged 23-48 years, data was collected after 15 min of air breathing and at increasing transcutaneous oxygen tensions (20, 40 and 60 kPa), accomplished by a two group, random order and blinded hyperoxemic protocol.
Results:
Left ventricular stroke volume [86 +/- 13 to 75 +/- 9 mL (mean +/- SD)] and end-diastolic area (19.3 +/- 4.4 to 16.8 +/- 4.3 cm(2)) declined (P < 0.05), and showed a linear, negative dose-response relationship to increasing arterial oxygen levels in a regression model. Peripheral resistance and characteristic impedance increased in a similar manner. Heart rate, left ventricular fractional area change, end-systolic area, mean arterial pressure, arterial compliance or carbon dioxide levels did not change.
Conclusion:
There is a linear dose-response relationship between arterial oxygen and cardiovascular parameters when the systemic oxygen tension increases above normal. A direct effect of supplemental oxygen on the vessels may therefore not be excluded. Proximal aortic and peripheral resistance increases from hyperoxaemia, but a decrease of venous return implies extra cardiac blood-pooling and compensatory relaxation of the capacitance vessels.
Related Concept Videos
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue, improving...
 01:23
Hypoxia
Types of Hypoxia
There are four primary types of hypoxia, each resulting from a different cause:
1. Anemic hypoxia: This type occurs due to insufficient oxygen delivery caused by a lack of red blood cells (RBCs) or RBCs with abnormal or...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:27
Oxygen Transport in the Blood
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:24
Factors Affecting Respiration