Related Experiment Video
Updated: Jul 14, 2026


Technical Considerations and Approach to Redo Foregut Surgery
Published on: September 22, 2023
Band erosion following gastric banding: how to treat it
Ezio Lattuada1, Marco Antonio Zappa, Enrico Mozzi
1Fondazione Ospedale Maggiore Policlinico, Mangiagalli e Regina Elena, Milano, Italy. e.lattuada@policlinico.mi.it

Background:
Intragastric band migration is an unusual but major long-term complication of gastric banding: its frequency ranges from 0.5-3.8% and always requires removal of the band. Different laparoscopic, laparotomic or endoscopic methods are currently used for band removal.
Methods:
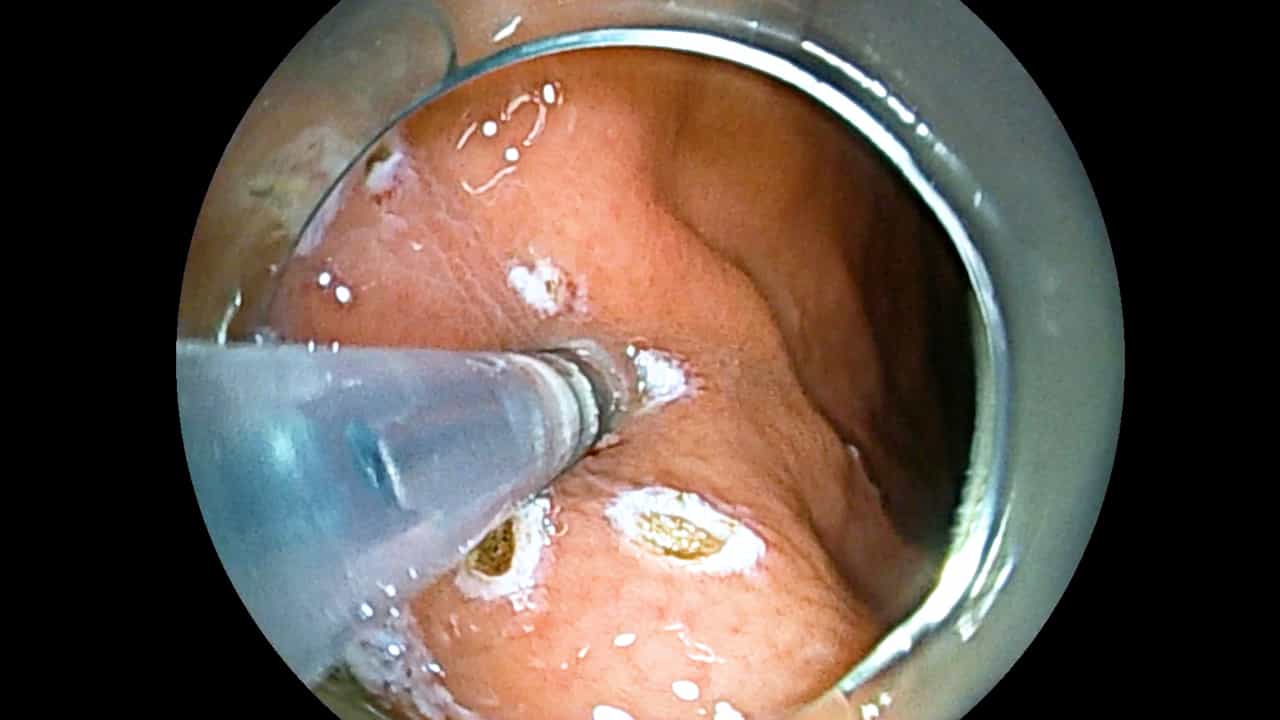
571 morbidly obese patients underwent adjustable gastric banding from February 1998 to July 2006. Band erosion occurred in 3 patients (0.52%). In addition, 6 such patients were referred to our Department from other hospitals. To remove the migrated band, in most patients we used an endoscopic approach with a device designed to cut the band: the Gastric Band Cutter (AMI, Agency for Medical Innovation).
Results:
In 7 of the 9 patients, we used the gastric band cutter to remove the band endoscopically. It was able to cut the band successfully in all cases except one, where twisting of the cutting wire required conversion from endoscopy to laparoscopy. In another case, the band, after being cut, was locked in the gastric wall and required laparotomic removal. In 2 patients, we had to remove the band surgically - in one case for port-site infection with subphrenic abscess, and in the other case for complete band migration into the jejunum associated with acute pancreatitis, cholelithiasis and choledocholithiasis.
Conclusion:
The Gastric Band Cutter, when used, was successful in dividing the band in all cases except one, although we could not always complete the procedure endoscopically. Endoscopic removal seems to be the procedure of choice for band erosion, because it allows earlier patient discharge and avoids a surgical operation. It is advisable to perform the endoscopic removal in the operating theater, because of possible complications of the procedure.

Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...